Related Experiment Video
Updated: Aug 11, 2026
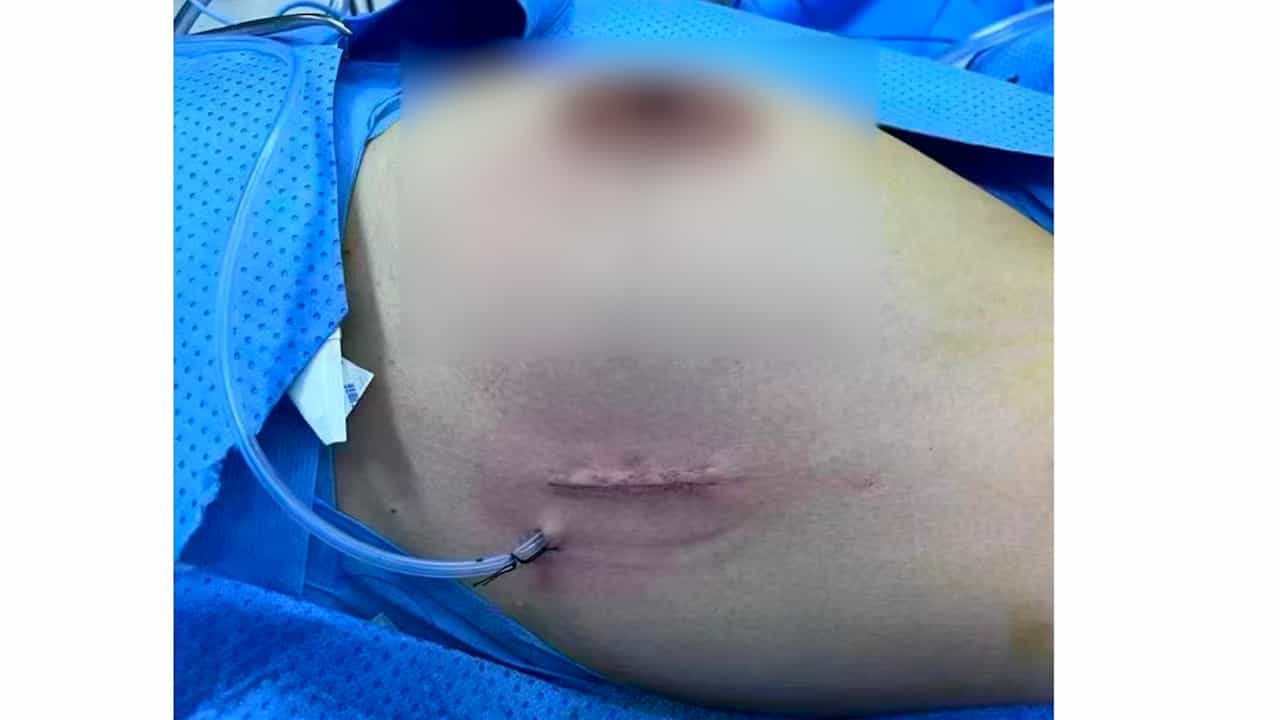

Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Clinical implications of axillary sentinel lymph node 'micrometastases' in breast cancer
J-S Krauth1, H Charitansky, S Isaac
1Surgical Gynecology and Oncology Unit, Centre Hospitalier Lyon Sud, 69370 Pierre-Benite, France. jeankrauth@hotmail.com

Aims:
The aim of this study was to determine, from a series of cases, the frequency and prognostic factors of invasion of non-sentinel lymph nodes when the axillary sentinel lymph node contains a metastasis < or =2 mm, and thereby select a population in which completion axillary dissection could be omitted.
Methods:
Between July 1996 and July 2003, 62 patients, which axillary sentinel lymph node contained a metastasis < or =2 mm had an evaluation of the axillary non-sentinel lymph nodes. Eleven patients had also an evaluation of internal mammary lymph nodes.
Results:
Eleven patients had axillary non-sentinel lymph node invasion: six by metastases < or =2 mm and five by macrometastases. When internal mammary lymph nodes were also concerned, nodal invasion apart from the axillary sentinel lymph node was seen in 14 patients. Vascular lymphatic invasion was the only factor, statistically significant, linked to non-sentinel lymph node invasion (p = 0.02).
Conclusion:
Whatever the size or method of histological detection (pN1mi or pN0(i+)), the presence of a metastasis < or =2 mm in the axillary sentinel lymph node leads us to carry out completion axillary dissection to optimize staging and loco-regional control of the disease.
