Related Experiment Video
Updated: Aug 11, 2026
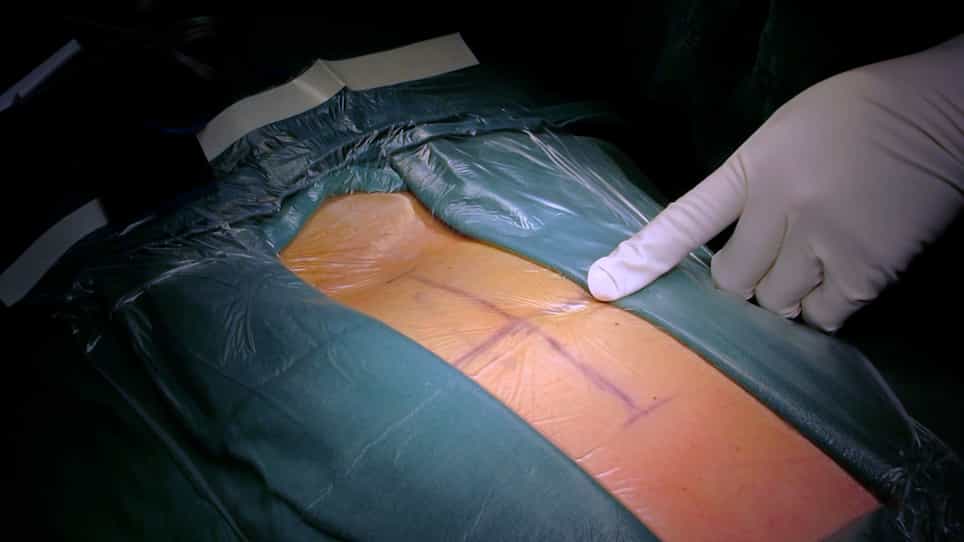

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Occipitocervical fusion after resection of craniovertebral junction tumors
Hyunchul Shin1, Ignacio J Barrenechea, Jonathan Lesser
1Department of Neurosurgery, St. Luke's-Roosevelt Hospital Center, New York, New York 10019, USA.

Object:
Surgical access to tumors at the craniovertebral junction (CVJ) requires extensive bone removal. Guidelines for the use of occipitocervical fusion (OCF) after resection of CVJ tumors have been based on anecdotal evidence. The authors performed a retrospective study of factors associated with the use of OCF in 46 patients with CVJ tumors. The findings were used to develop recommendations for use of OCF in such patients.
Methods:
The authors retrospectively reviewed the cases of 51 patients with CVJ tumors treated by their group between March 1991 and February 2004. Forty-six patients were available for follow up. Charts were reviewed to obtain data on demographic characteristics, presenting symptoms, and perioperative complications. Preoperative computerized tomography scans and magnetic resonance imaging studies were obtained in all patients. Occipitocervical fusion was performed in patients who had undergone a unilateral condyle resection in which 70% or more of the condyle was removed, a bilateral condyle resection with 50% removal, or C1-2 vertebral body destruction. Of the 46 patients, 16 had foramen magnum meningiomas, 17 had chordomas, one had a chondrosarcoma, two had Schwann cell tumors, two had glomus tumors, and eight had other types of tumors. Twenty-three (50%) of the 46 patients underwent OCF, including 15 of the 17 patients with chordomas (88%). None of the patients with meningiomas required fusion. Seventeen (71%) of the 24 patients presenting with neck pain preoperatively underwent OCF.
Conclusions:
Patients presenting with neck pain had a 71% chance of undergoing OCF. Patients with chordomas and metastatic tumors were most likely to require OCF. One patient with a 50% unilateral condylar resection returned with OC instability for which OCF was required. Based on their clinical experience and published biomechanical studies, the authors recommend that OCF be performed when 50% or more of one condyle is resected.
Related Concept Videos
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:28
Articulations of the Vertebral Column