Related Experiment Video
Updated: Aug 11, 2026


Procedure for Human Saphenous Veins Ex Vivo Perfusion and External Reinforcement
Published on: October 1, 2014
Development of reflux in the perforator veins in limbs with primary venous disease
Nicos Labropoulos1, Apostolis K Tassiopoulos, Ahmad F Bhatti
1Department of Surgery, Loyola University Medical Center, Newark, NJ, USA. nlabrop@yahoo.com

Objective:
To determine the patterns by which perforator vein (PV) reflux develops in patients with primary chronic venous disease (CVD).
Methods:
Patients with CVD who had at least two examinations with duplex ultrasonography before any treatment were included in this study. These were patients who were offered an operation at their first visit, but for various reasons treatment was postponed. All affected limbs were classified by the CEAP classification system. A detailed map of normal and refluxing sites was drawn on an anatomic chart by using several landmarks of the skin, muscle, and bone. Reflux was induced by distal limb compression followed by sudden release by using rapid-inflation pneumatic cuffs and dorsiplantar flexion. All new reflux sites were documented. The PV reflux was divided into ascending type, descending type (re-entry flow), and those that developed in new locations, which did not have reflux in any system at that level.
Results:
The total number of patients studied was 127 (158 limbs). There were 29 limbs (18%) in 26 patients with reflux development in the PV. In total, 38 new incompetent PVs were identified. The median time for the examination was 25 months (range, 9-52 months). Reflux in a previously normal PV at a re-entry site was detected in 15, in an ascending manner from an extension of superficial vein reflux in 18, and in a new, previously intact location in 5. At the new sites, reflux in the superficial veins connected to the incompetent PVs was always present. PVs connected to the great saphenous vein system were most common (n = 27), followed by those connected to short saphenous (n = 8) and nonsaphenous (n = 3) veins. Worsening in the clinical class was observed in 11 limbs: 5 from class 2 to 3, 2 from class 2 to 4, 2 from class 3 to 4, and 2 from class 4 to 6. The worsening could not be attributed to the PV reflux alone, because other veins became incompetent as well.
Conclusions:
Reflux in PVs develops in ascending fashion through the superficial veins, at re-entry points, and at new sites. Worsening of CVD is observed with new PV reflux, but many other factors play a major role, and therefore a causative association is difficult to prove.
More Related Videos
 08:05
Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
 07:02
A Rabbit Venous Interposition Model Mimicking Revascularization Surgery using Vein Grafts to Assess Intimal Hyperplasia under Arterial Blood Pressure
Published on: May 15, 2020
Related Concept Videos
 01:26
Varicose Veins I: Introduction
 01:15
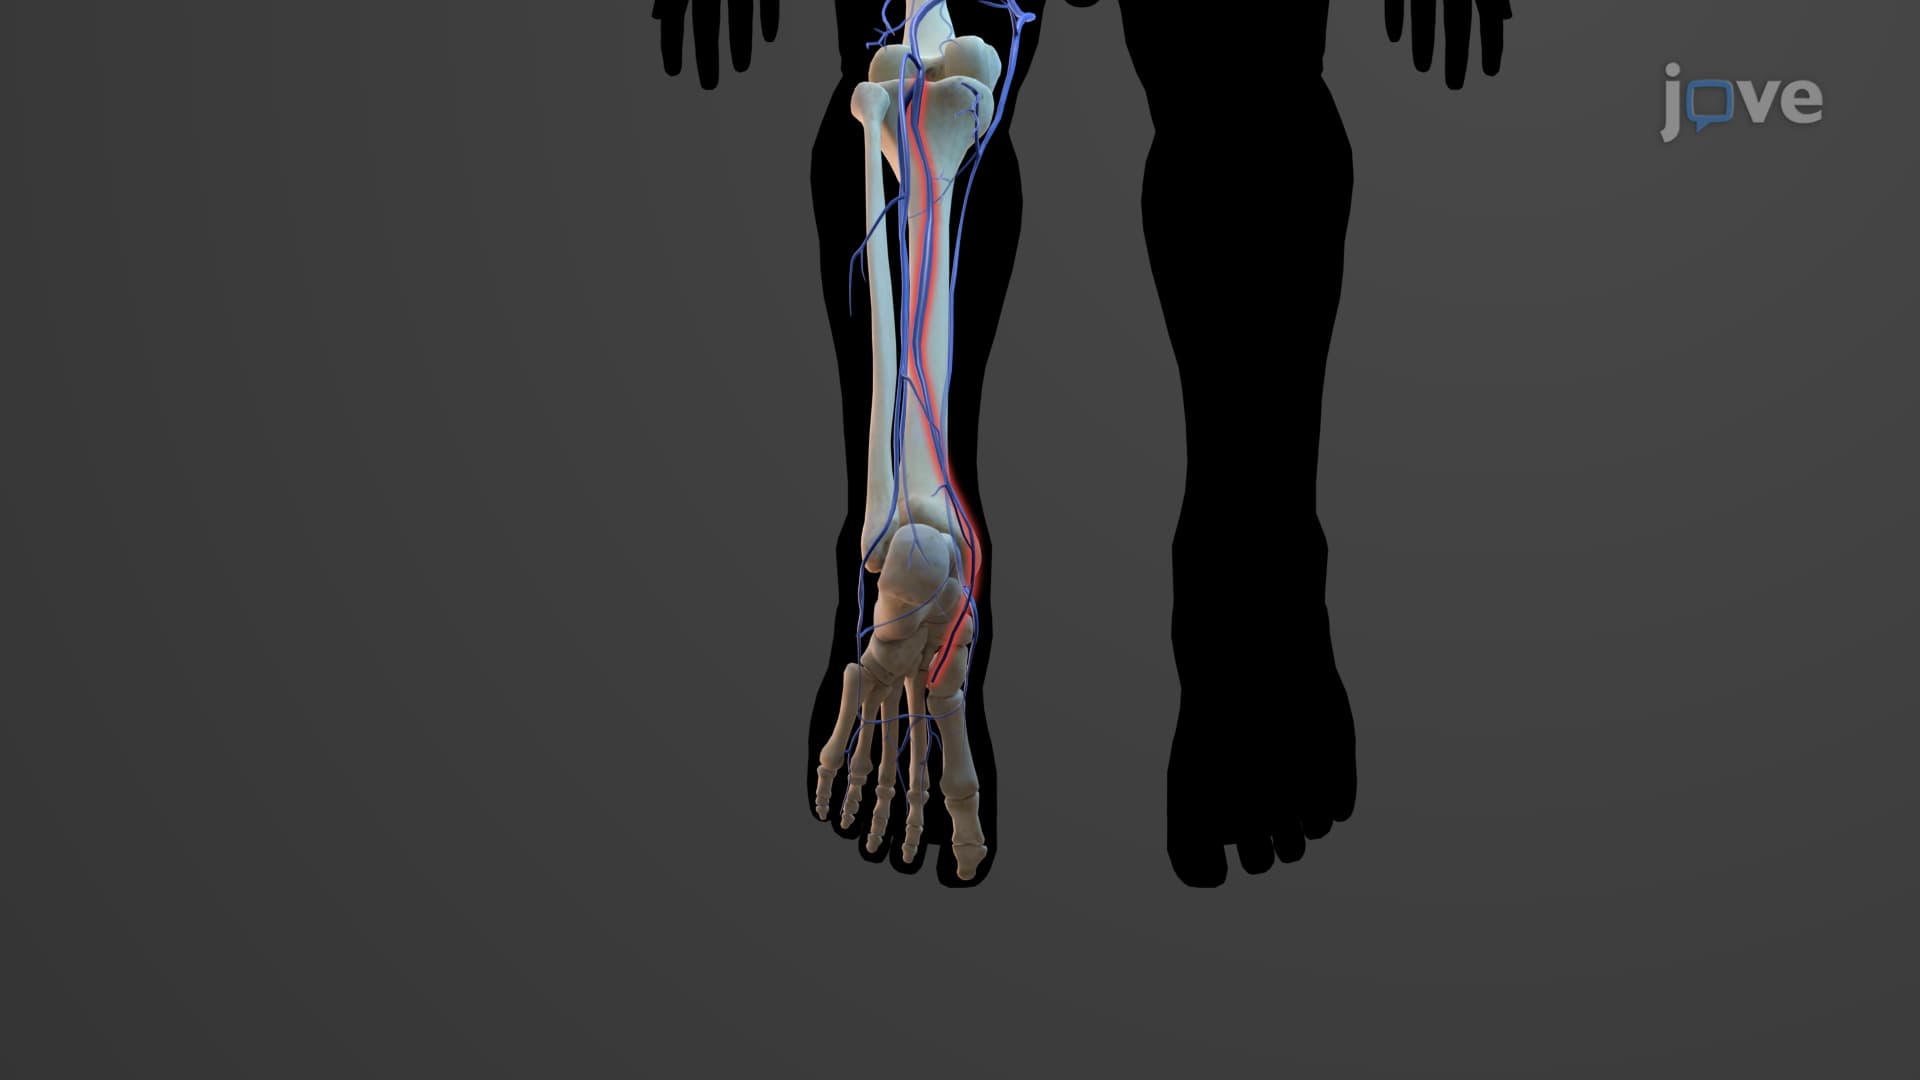
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:24
Esophageal Varices-I: Introduction
 01:17
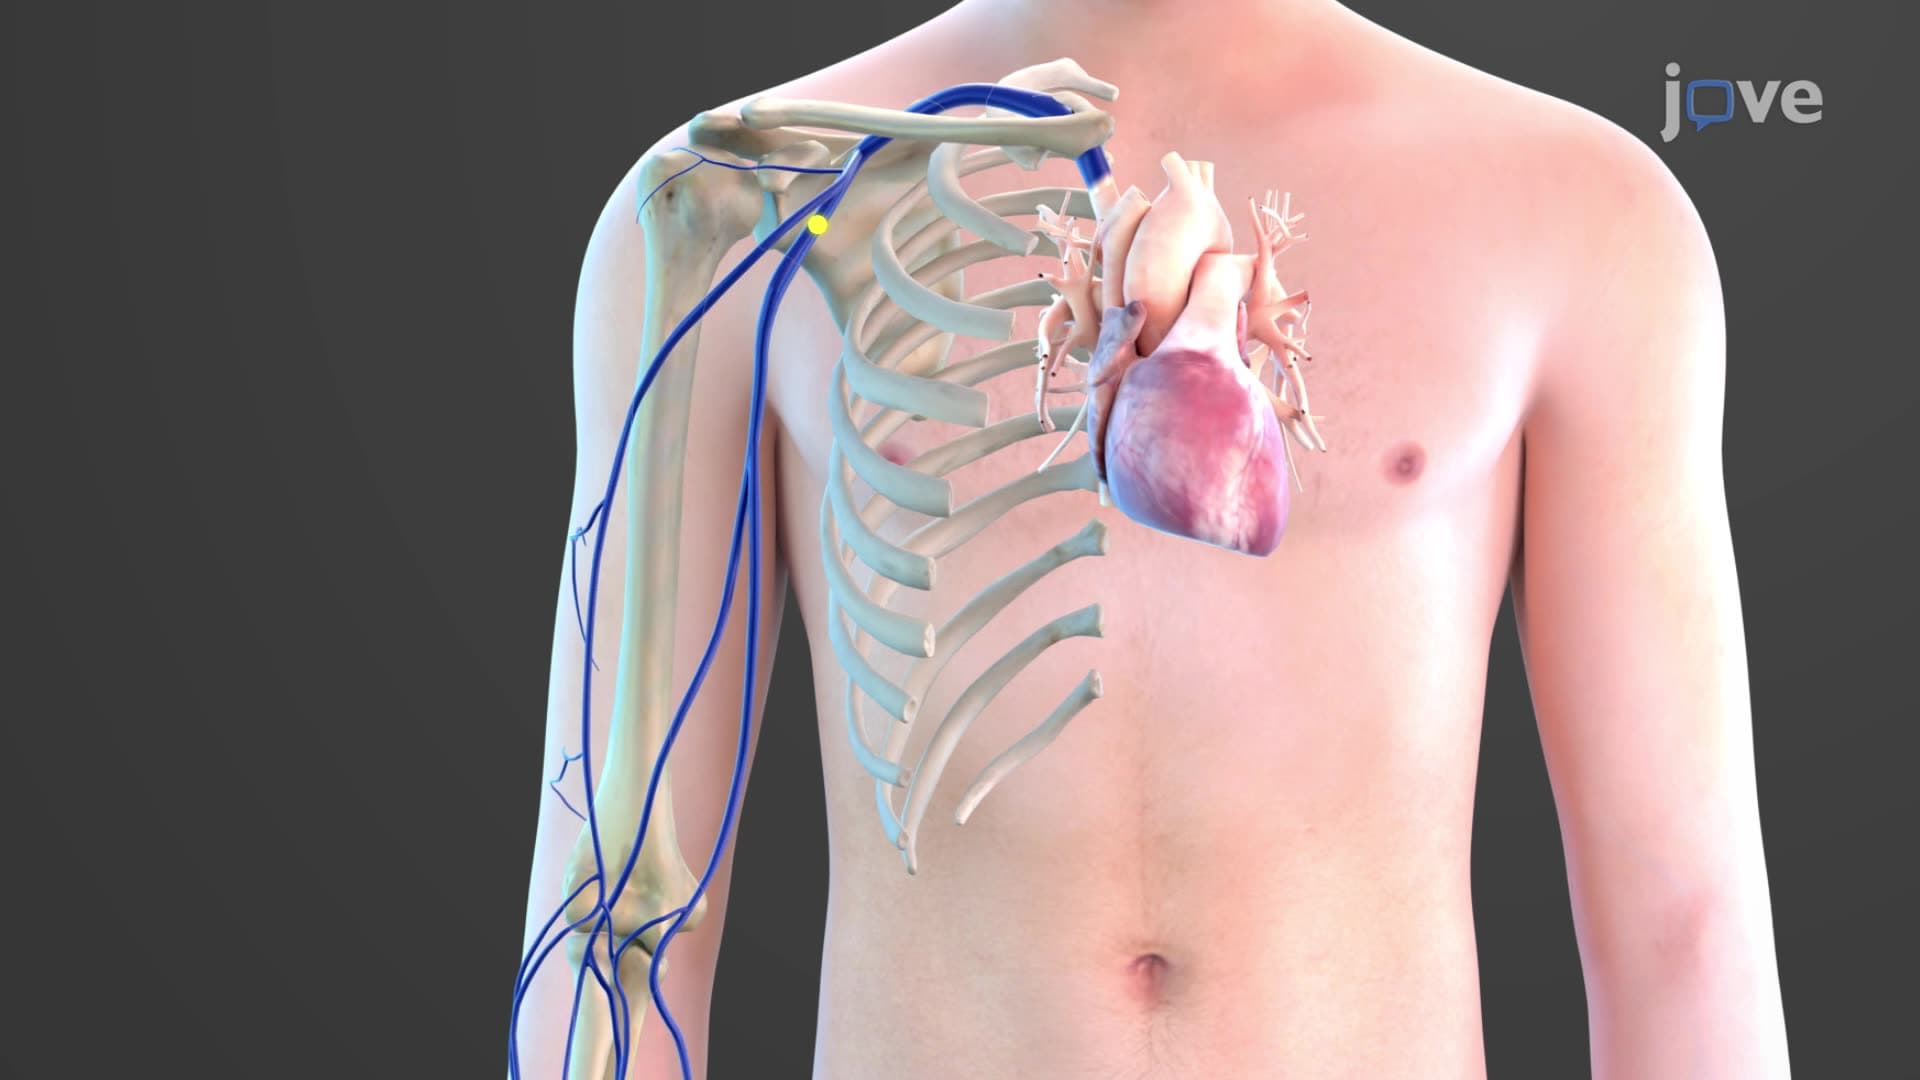
Veins of Upper Limbs
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...