Related Experiment Video
Updated: Aug 11, 2026
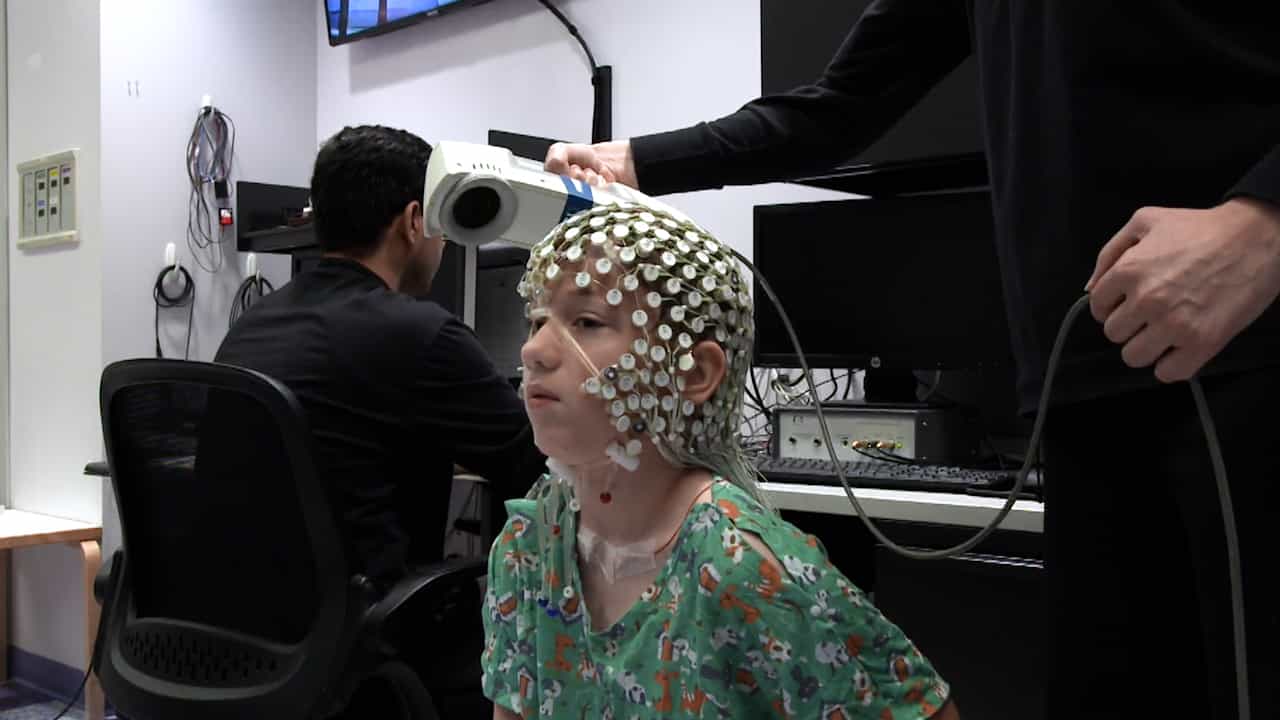

Electromagnetic Source Imaging in Presurgical Evaluation of Children with Drug-Resistant Epilepsy
Published on: September 20, 2024
Juvenile myoclonic epilepsy subsyndromes: family studies and long-term follow-up
Iris E Martínez-Juárez1, María Elisa Alonso, Marco T Medina
1David Geffen School of Medicine at UCLA and VA GLAHS Epilepsy Center of Excellence, Epilepsy Genetics/Genomics Laboratories, Comprehensive Epilepsy Program, Los Angeles, CA 90073, USA.

Insights
Juvenile myoclonic epilepsy (JME) is a distinct disease entity, not solely an idiopathic generalized epilepsy. Long-term follow-up of 257 patients confirms JME and its subtypes are chronic conditions with variable family phenotypes.
Area of Science:
- Neurology
- Genetics
- Epilepsy Research
Background:
- The 2001 International League Against Epilepsy (ILAE) classification proposed grouping Juvenile Myoclonic Epilepsy (JME) with other idiopathic generalized epilepsies (IGE), questioning its distinct disease status.
- This classification implied JME might not be a sole phenotype within families and should not be classified independently.
- Despite JME being a common, presumed lifelong epilepsy, long-term follow-up data has been lacking.
Purpose of the Study:
- To investigate the distinctness of JME as a disease entity.
- To perform a long-term follow-up of JME patients to assess clinical course and family phenotypes.
- To address the ILAE's 2001 classification proposal regarding JME.
Main Methods:
- Prospective study of 257 JME patients, categorized into four groups: classic JME, childhood absence epilepsy (CAE) evolving to JME, JME with adolescent absence, and JME with astatic seizures.
- Examination of clinical and EEG phenotypes in family members.
- Long-term clinical course assessment over a mean of 11 ± 6 years (up to 52 years).
Main Results:
- Forty percent of JME families presented JME as the sole clinical phenotype.
- Classic JME families showed JME (40%) and generalized tonic-clonic seizures (GTCS) only (35%) in relatives, while CAE evolving to JME families (66%) exhibited diverse IGE phenotypes.
- Absence seizures were more frequent in relatives of CAE evolving to JME families. CAE evolving to JME showed female preponderance, maternal transmission, poor treatment response, and lower seizure-free rates (7%) compared to classic JME (58%).
Conclusions:
- All studied JME subsyndromes are chronic and potentially lifelong conditions, supporting JME as a distinct group of diseases.
- The findings challenge the 2001 ILAE classification by demonstrating JME as a sole phenotype in many families and highlighting its distinct clinical course.
- Genetic evidence, including seven chromosome loci and associated mutations/SNPs, further supports JME's classification as a separate entity.
Abstract:
The 2001 classification subcommittee of the International League Against Epilepsy (ILAE) proposed to 'group JME, juvenile absence epilepsy, and epilepsy with tonic clonic seizures only under the sole heading of idiopathic generalized epilepsies (IGE) with variable phenotype'. The implication is that juvenile myoclonic epilepsy (JME) does not exist as the sole phenotype of family members and that it should no longer be classified by itself or considered a distinct disease entity. Although recognized as a common form of epilepsy and presumed to be a lifelong trait, a long-term follow-up of JME has not been performed. To address these two issues, we studied 257 prospectively ascertained JME patients and encountered four groups: (i) classic JME (72%), (ii) CAE (childhood absence epilepsy) evolving to JME (18%), (iii) JME with adolescent absence (7%), and (iv) JME with astatic seizures (3%). We examined clinical and EEG phenotypes of family members and assessed clinical course over a mean of 11 +/- 6 years and as long as 52 years. Forty per cent of JME families had JME as their sole clinical phenotype. Amongst relatives of classic JME families, JME was most common (40%) followed by grand mal (GM) only (35%). In contrast, 66% of families with CAE evolving to JME expressed the various phenotypes of IGE in family members. Absence seizures were more common in family members of CAE evolving to JME than in those of classic JME families (P < 0.001). Female preponderance, maternal transmission and poor response to treatment further characterized CAE evolving to JME. Only 7% of those with CAE evolving to JME were seizure-free compared with 58% of those with classic JME (P < 0.001), 56% with JME plus adolescent pyknoleptic absence and 62% with JME plus astatic seizures. Long-term follow-up (1-40 years for classic JME; 5-52 years for CAE evolving to JME, 5-26 years for JME with adolescent absence and 3-18 years for JME with astatic seizures) indicates that all subsyndromes are chronic and perhaps lifelong. Seven chromosome loci, three epilepsy-causing mutations and two genes with single nucleotide polymorphisms (SNPs) associating with JME reported in literature provide further evidence for JME as a distinct group of diseases.
More Related Videos
 08:43
Long-term Continuous EEG Monitoring in Small Rodent Models of Human Disease Using the Epoch Wireless Transmitter System
Published on: July 21, 2015
 10:22
Interictal High Frequency Oscillations Detected with Simultaneous Magnetoencephalography and Electroencephalography as Biomarker of Pediatric Epilepsy
Published on: December 6, 2016
Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:22
Epilepsy ll: Types
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types:
 01:19
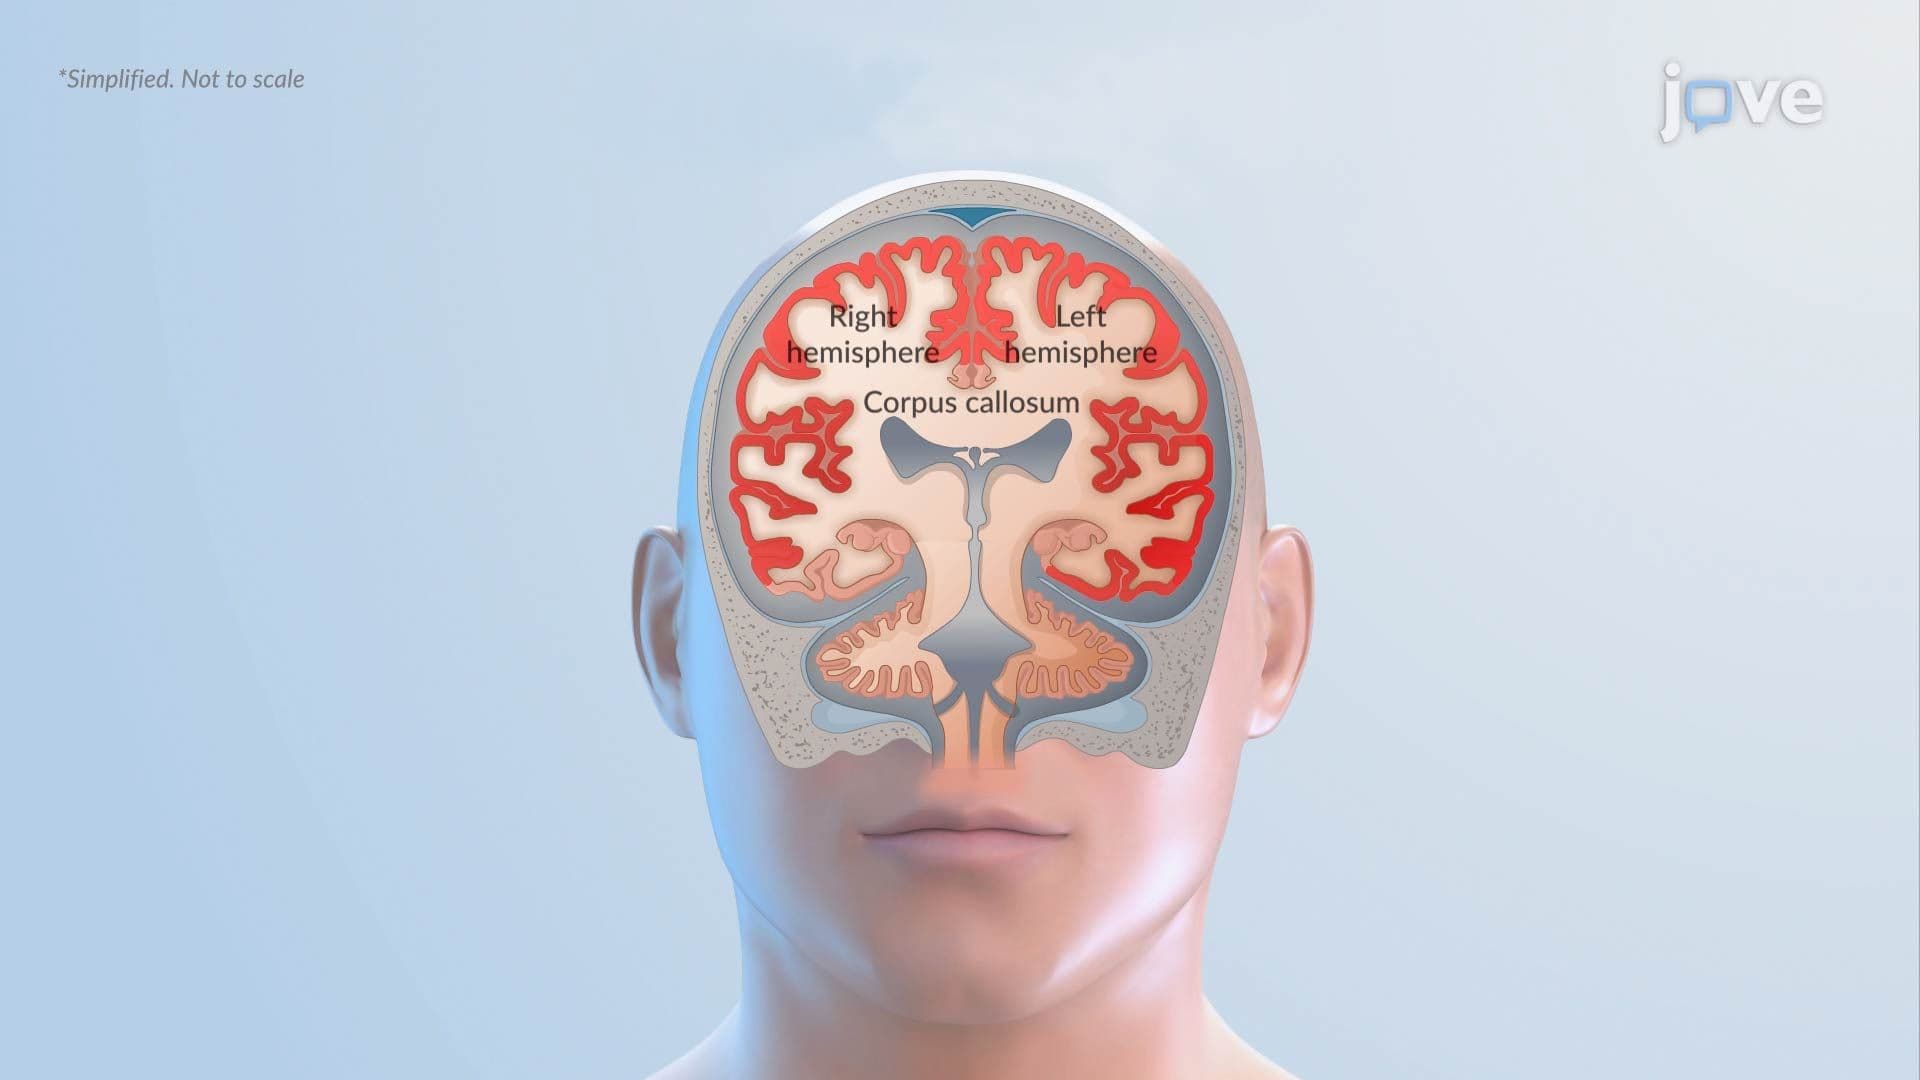
Seizures ll: Types
 01:20
Seizures l: Introduction
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies