Related Experiment Video
Updated: Aug 10, 2026

Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
Theoretical considerations on the pathophysiology of normal pressure hydrocephalus (NPH) and NPH-related dementia
Abderrahmane Hamlat1, Mahmoudreza Adn, Seddik Sid-ahmed
1Department of Neurosurgery, Service de neurochirurgie, CHRU Pontchaillou, Rue Henri Le Guilloux, 35000 Rennes Cedex 2, France. hamlat.abd@wanadoo.fr

Abstract:
Normal pressure hydrocephalus (NPH) is considered to be an example of reversible dementia although clinical improvement after shunting varies from subject to subject, and recent studies have pointed to a possible link with other dementia. The authors consider that the craniospinal compartment is a partially closed sphere with control device systems represented by the spinal axis and the sagittal sinus-arachnoid villi complex which interact with each other in the clinical patient setting. We hypothesise that changing spinal compliance by altering the flow process and CSF dynamics lead to hydrocephalus. Therefore four NPH types have been distinguished according to the alterations in spinal compliance, decrease in CSF absorption at the sagittal sinus or both occurrences. The authors consider that NPH and NPH-related diseases (NPH-RD) are initiated by the same common final pathway and demonstrate that NPH could represent an initial stage of NPH-RD. Progression of clinical signs can be explained as damage to the cerebral tissue by both intermittent increased intracranial pressure and pulse pressure waves leading to periventricular ischaemia. In addition, they believe that both volume equilibrium and spinal compliance are restored in patients who improve after CSF shunt, whereas in patients whose condition does not improve, only volume equilibrium is restored and not spinal compliance, which was the underlying cause of hydrocephalus in such cases. They therefore wonder whether cervical decompression should not be indicated in patients who show no improvement. Although attractive, this analysis warrants confirmation from clinical, radiological, and hydrodynamic studies.

Related Concept Videos
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:22
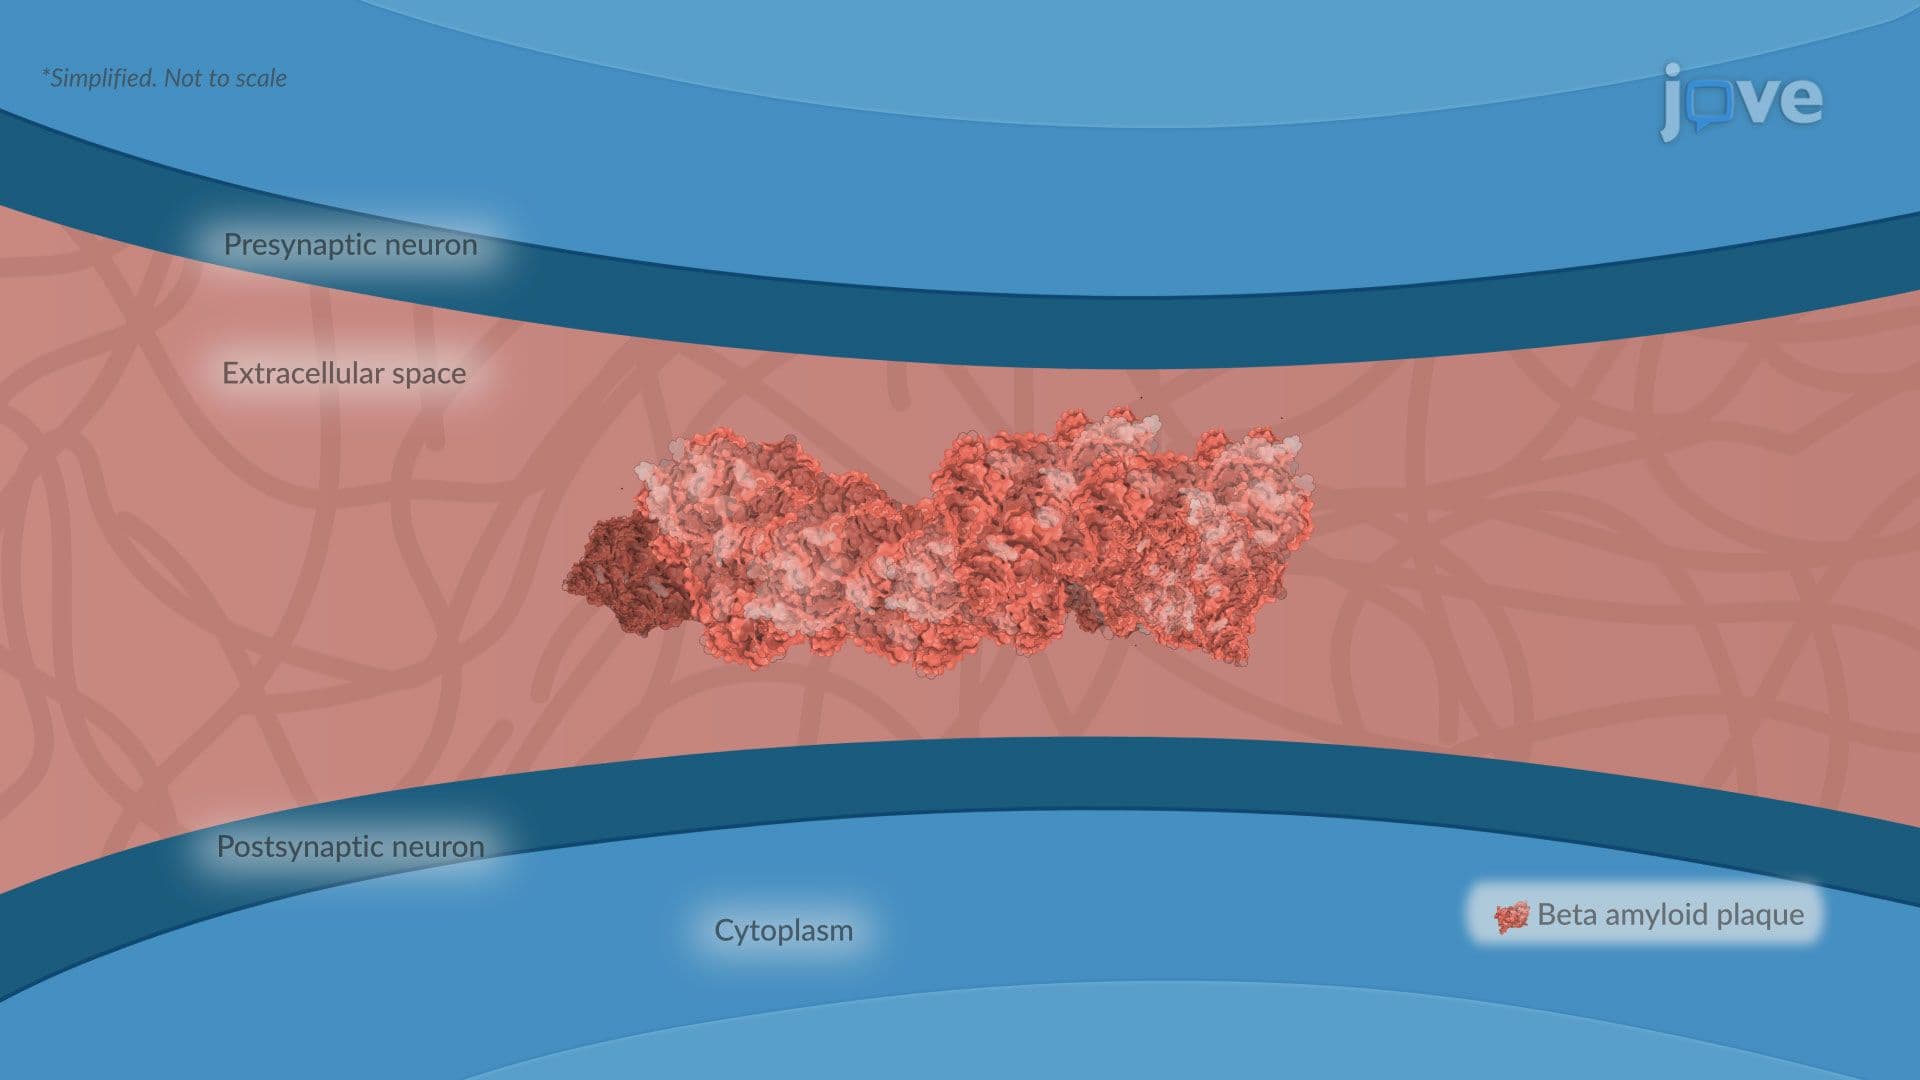
Dementia l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:23
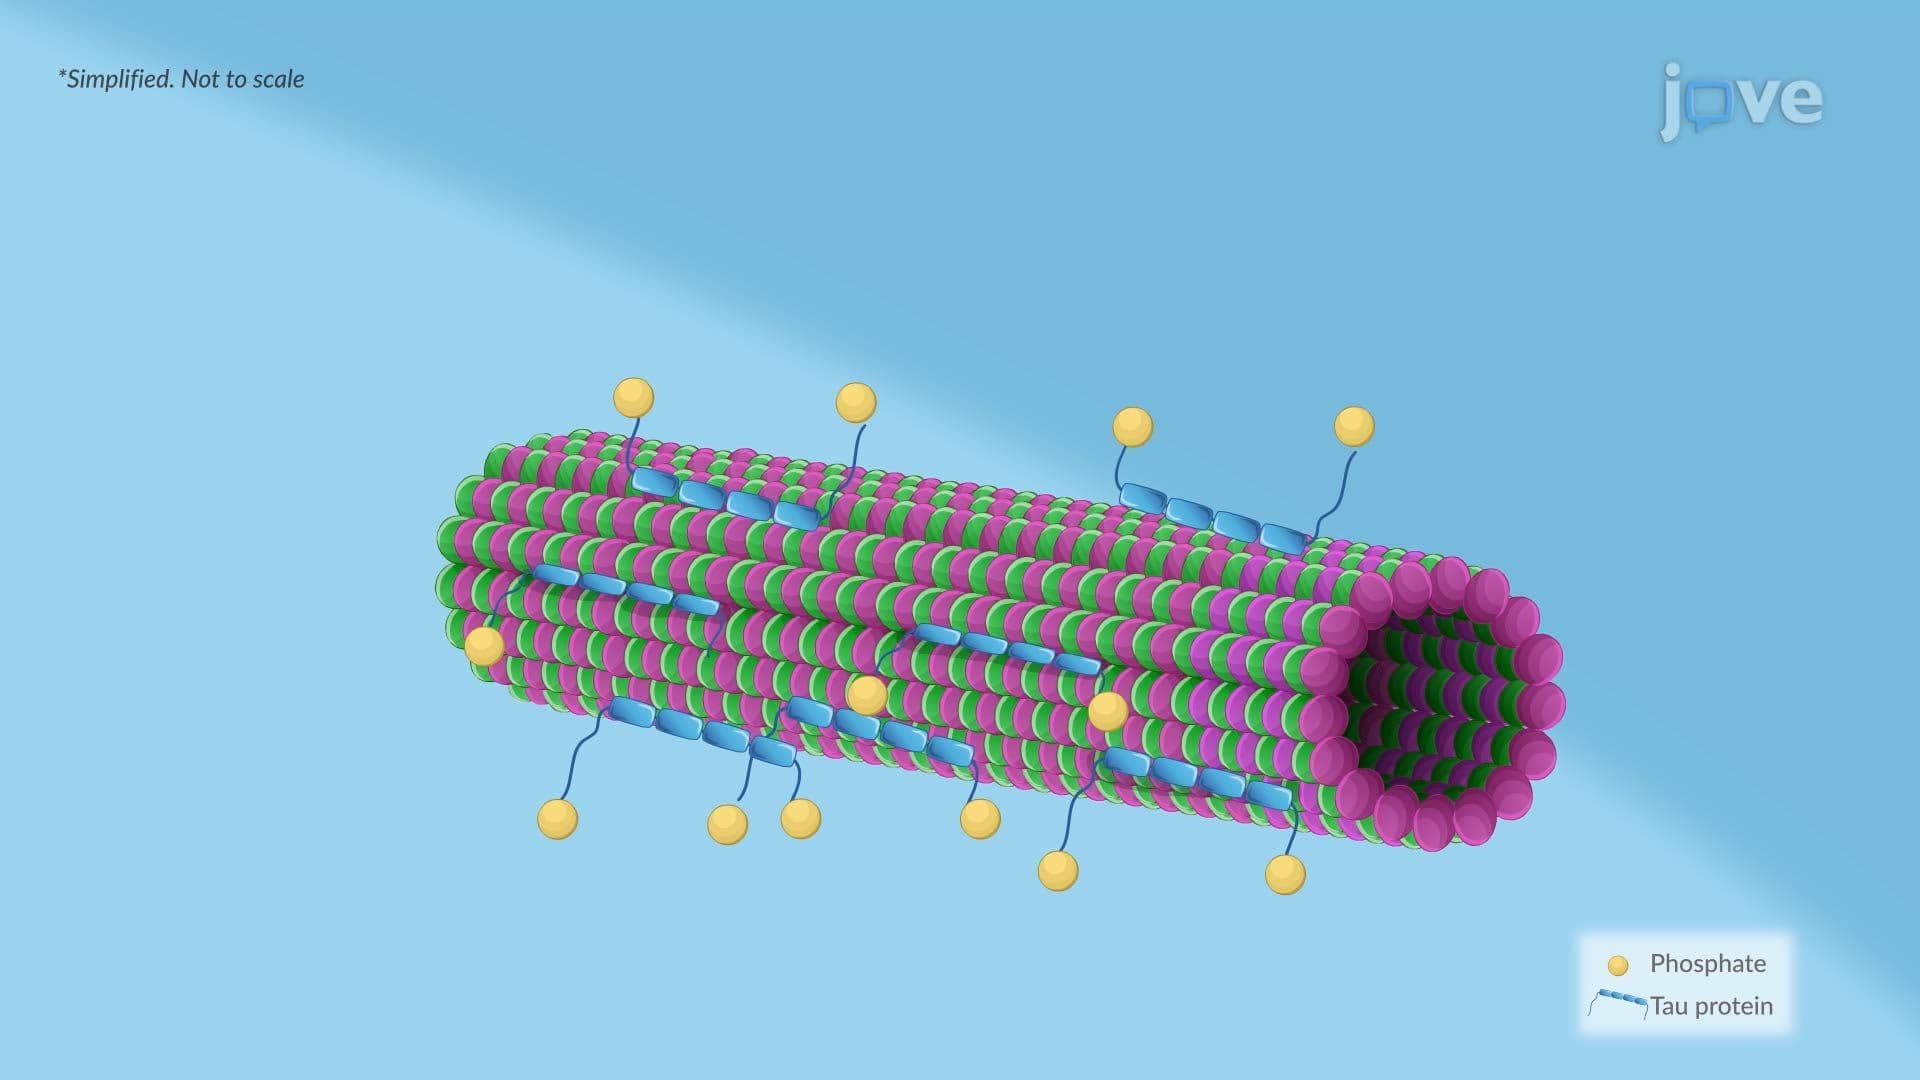
Alzheimer Disease ll: Pathophysiology
 01:24
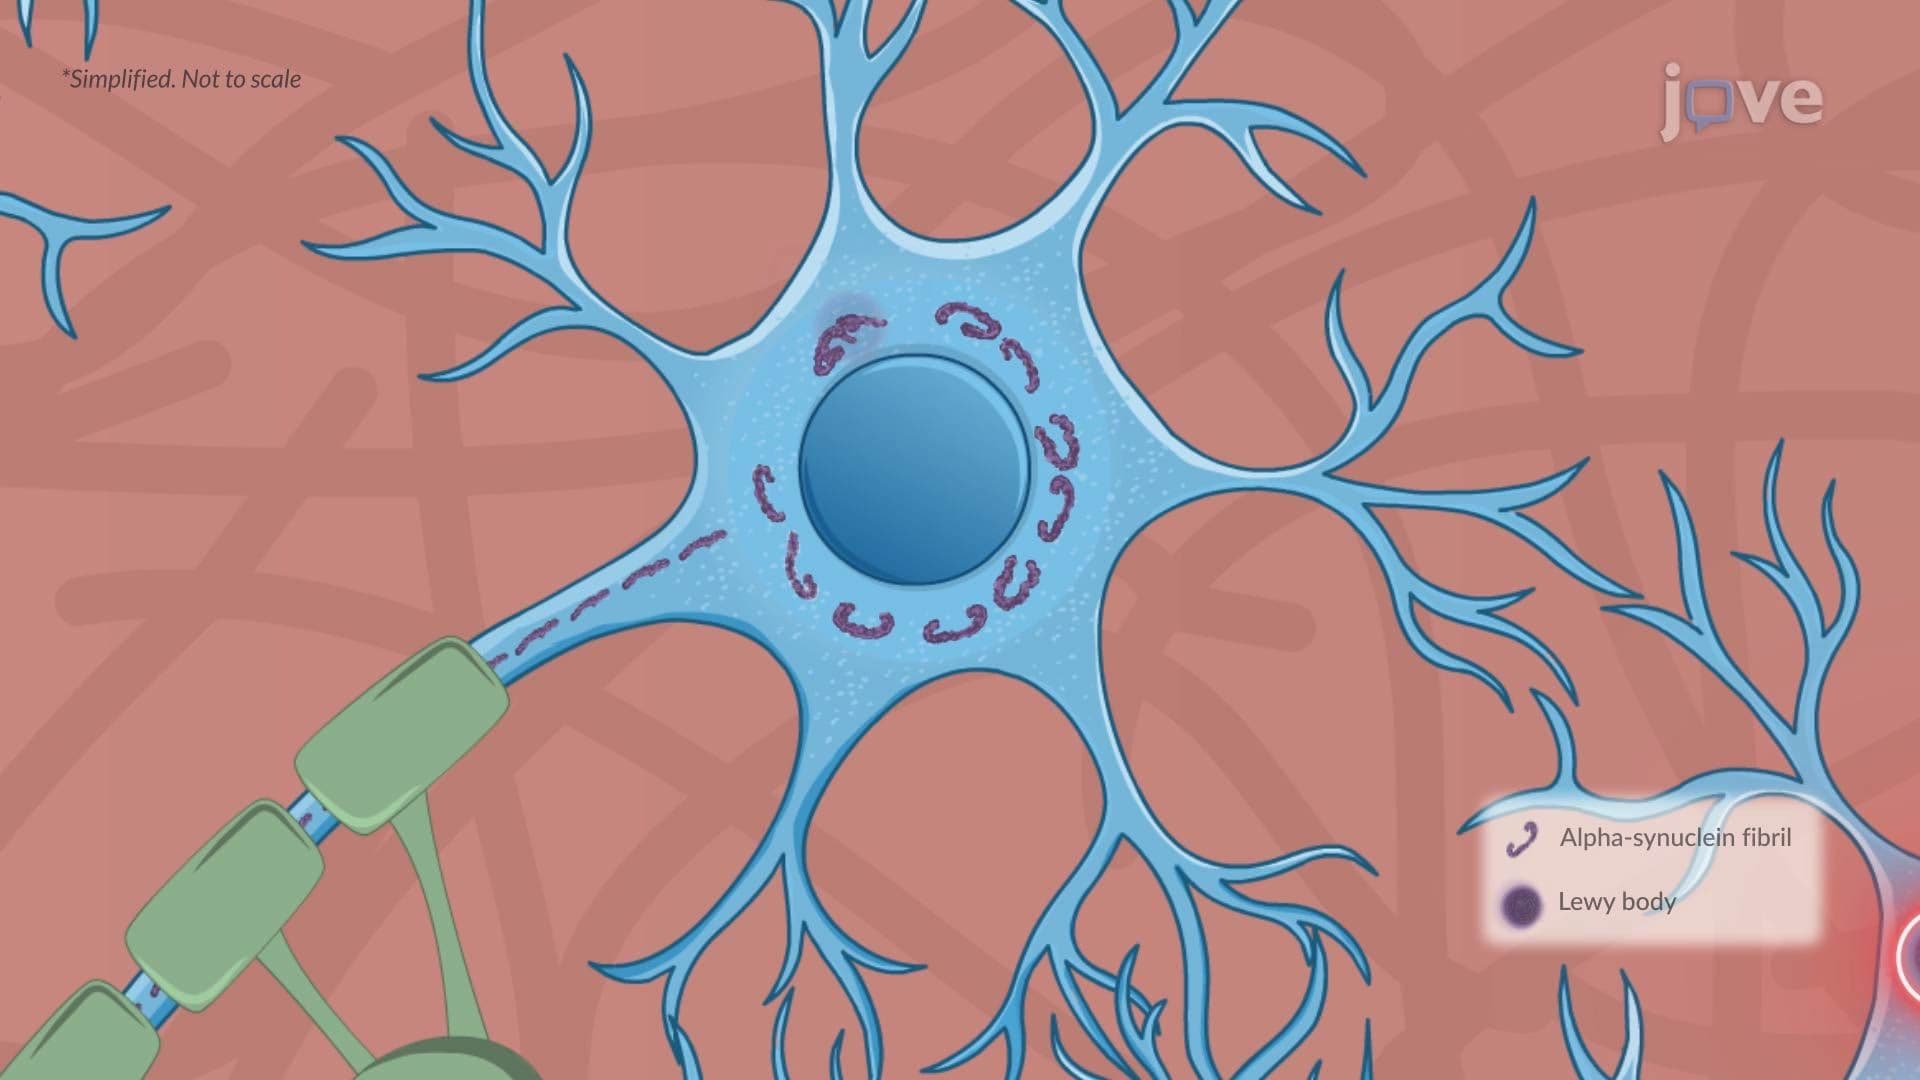
Parkinson Disease ll: Pathophysiology