Related Experiment Video
Updated: Aug 10, 2026


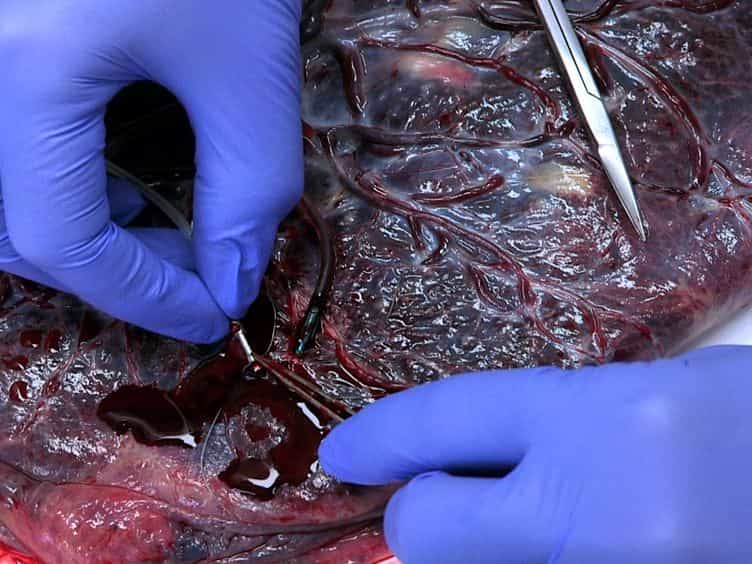
The 4-vessel Sampling Approach to Integrative Studies of Human Placental Physiology In Vivo
Published on: August 2, 2017
Placental transport and metabolism in fetal overgrowth -- a workshop report
T Jansson1, I Cetin, T L Powell
1Department of Obstetrics and Gynecology, College of Medicine, University of Cincinnati, OH 45267, USA. thomas.jansson@uc.edu

Abstract:
Fetal overgrowth in pregnancies complicated by diabetes is the result of an increased substrate availability which stimulates fetal insulin secretion and fetal growth. However, despite strict glycemic control in modern clinical management of the pregnant woman with diabetes, fetal overgrowth remains an important clinical problem. Recent studies in vivo provide evidence for increased delivery of amino acids to the fetus in gestational diabetes (GDM) even when metabolic control is strict. This could be due to that truly normal maternal substrate levels cannot be achieved in diabetic pregnancies and/or caused by altered placental nutrient transport and metabolism. Studies in vitro demonstrate an up-regulation of placental transport systems for certain amino acids in GDM associated with fetal overgrowth. GDM is also characterized by changes in placental gene expression, including up-regulation of inflammatory mediators and Leptin. In type-I diabetes with fetal overgrowth the in vitro activity of placental transporters for both glucose and certain amino acids as well as placental lipoprotein lipase is increased. Furthermore, both clinical observations in type-I diabetic pregnancies and preliminary animal experimental studies suggest that even brief periods of metabolic perturbation early in pregnancy may affect placental growth and transport function for the remainder of pregnancy, thereby contributing to fetal overgrowth. Ultrasound measurements of fetal fat deposits and abdominal circumference as well as 3D ultrasound assessment of placental volume represent non-invasive techniques for in utero diagnosis of fetal and placental overgrowth. It is proposed that these methods represent valuable additions to the clinical management of the diabetic pregnancy. In conclusion, altered placental function may be a mechanism contributing to fetal overgrowth in diabetic pregnancies with apparent optimal metabolic control. It is proposed that detailed information on placental metabolism and transport functions obtained in vitro and in vivo represent a placental phenotype that provides important information and may facilitate diagnosis and improve clinical management of fetal overgrowth.

Related Concept Videos
 01:07
Teratogenicity
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism