Related Experiment Video
Updated: Aug 9, 2026
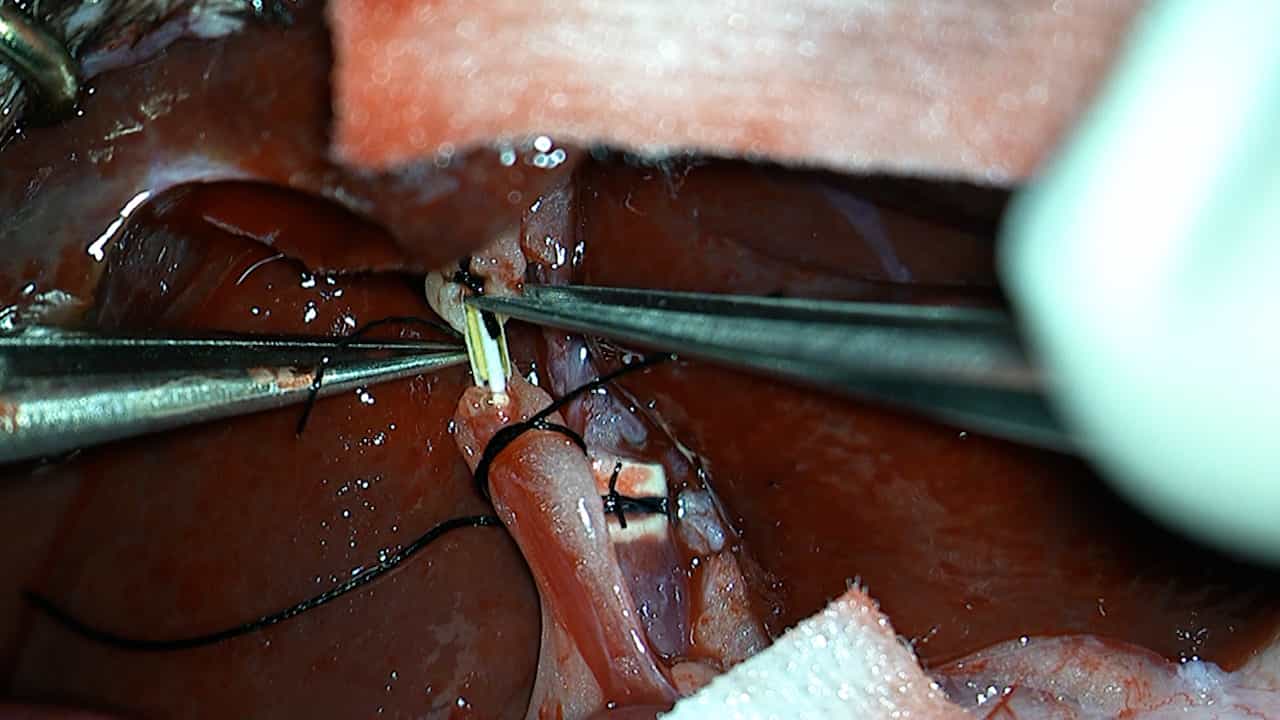

Liver Cold Storage and Transplantation in the Cold-Adaptive Daurian Ground Squirrels
Published on: July 3, 2025
Liver transplant in Hawaii: the survival of a small centre
Linda L Wong1, Whitney Limm, Alan Cheung
1Department of Surgery, Transplant Institute, St Francis Medical Center, Honolulu, Hawaii, USA. hepatoma@aol.com

Although many report the importance of case volume in complex cases, liver transplantation (LT) can be carried out successfully in a small centre. During a 11.5-yr period, 88 patients underwent LT in a single transplant centre in Hawaii. Indications for LT were primarily hepatitis C (n = 49) and hepatitis B (n = 13) and 22 patients (25%) had hepatocellular cancer (HCC) on explanted liver. There was no primary graft nonfunction, one retransplant for recurrent hepatitis C and two late hepatic artery thromboses, which did not require a retransplant. One patient developed partial portal vein thrombosis related to a hypercoagulable state and was rescued with anticoagulation. Of the 22 patients with HCC, 18 are alive, two died from recurrent disease (253 and 1428 d post-LT, respectively), one died because of a ruptured hepatic artery aneurysm (151 d) and one from complications caused by noncompliance (723 d). One-, 3- and 5-yr survival rates were 89%, 82% and 71%, respectively. Mean survival was 3034.9 d. During this time period, 142 liver resections, 77 pancreatic resections and 43 splenorenal shunts were performed by this group of surgeons. Because of the recent explosion of information on case volumes and centres of excellence, LT can be performed successfully at a small centre. Other major hepatobiliary/transplant procedures can help the surgeons maintain their operative skills. A smaller LT program may require a longer period of evolution, but it can provide a service for a geographically isolated population that would otherwise have limited opportunity for LT.
Although many report the importance of case volume in complex cases, liver transplantation (LT) can be carried out successfully in a small centre. During a 11.5-yr period, 88 patients underwent LT in a single transplant centre in Hawaii. Indications for LT were primarily hepatitis C (n = 49) and hepatitis B (n = 13) and 22 patients (25%) had hepatocellular cancer (HCC) on explanted liver. There was no primary graft nonfunction, one retransplant for recurrent hepatitis C and two late hepatic artery thromboses, which did not require a retransplant. One patient developed partial portal vein thrombosis related to a hypercoagulable state and was rescued with anticoagulation. Of the 22 patients with HCC, 18 are alive, two died from recurrent disease (253 and 1428 d post-LT, respectively), one died because of a ruptured hepatic artery aneurysm (151 d) and one from complications caused by noncompliance (723 d). One-, 3- and 5-yr survival rates were 89%, 82% and 71%, respectively. Mean survival was 3034.9 d. During this time period, 142 liver resections, 77 pancreatic resections and 43 splenorenal shunts were performed by this group of surgeons. Because of the recent explosion of information on case volumes and centres of excellence, LT can be performed successfully at a small centre. Other major hepatobiliary/transplant procedures can help the surgeons maintain their operative skills. A smaller LT program may require a longer period of evolution, but it can provide a service for a geographically isolated population that would otherwise have limited opportunity for LT.


Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...