Related Experiment Video
Updated: Aug 9, 2026
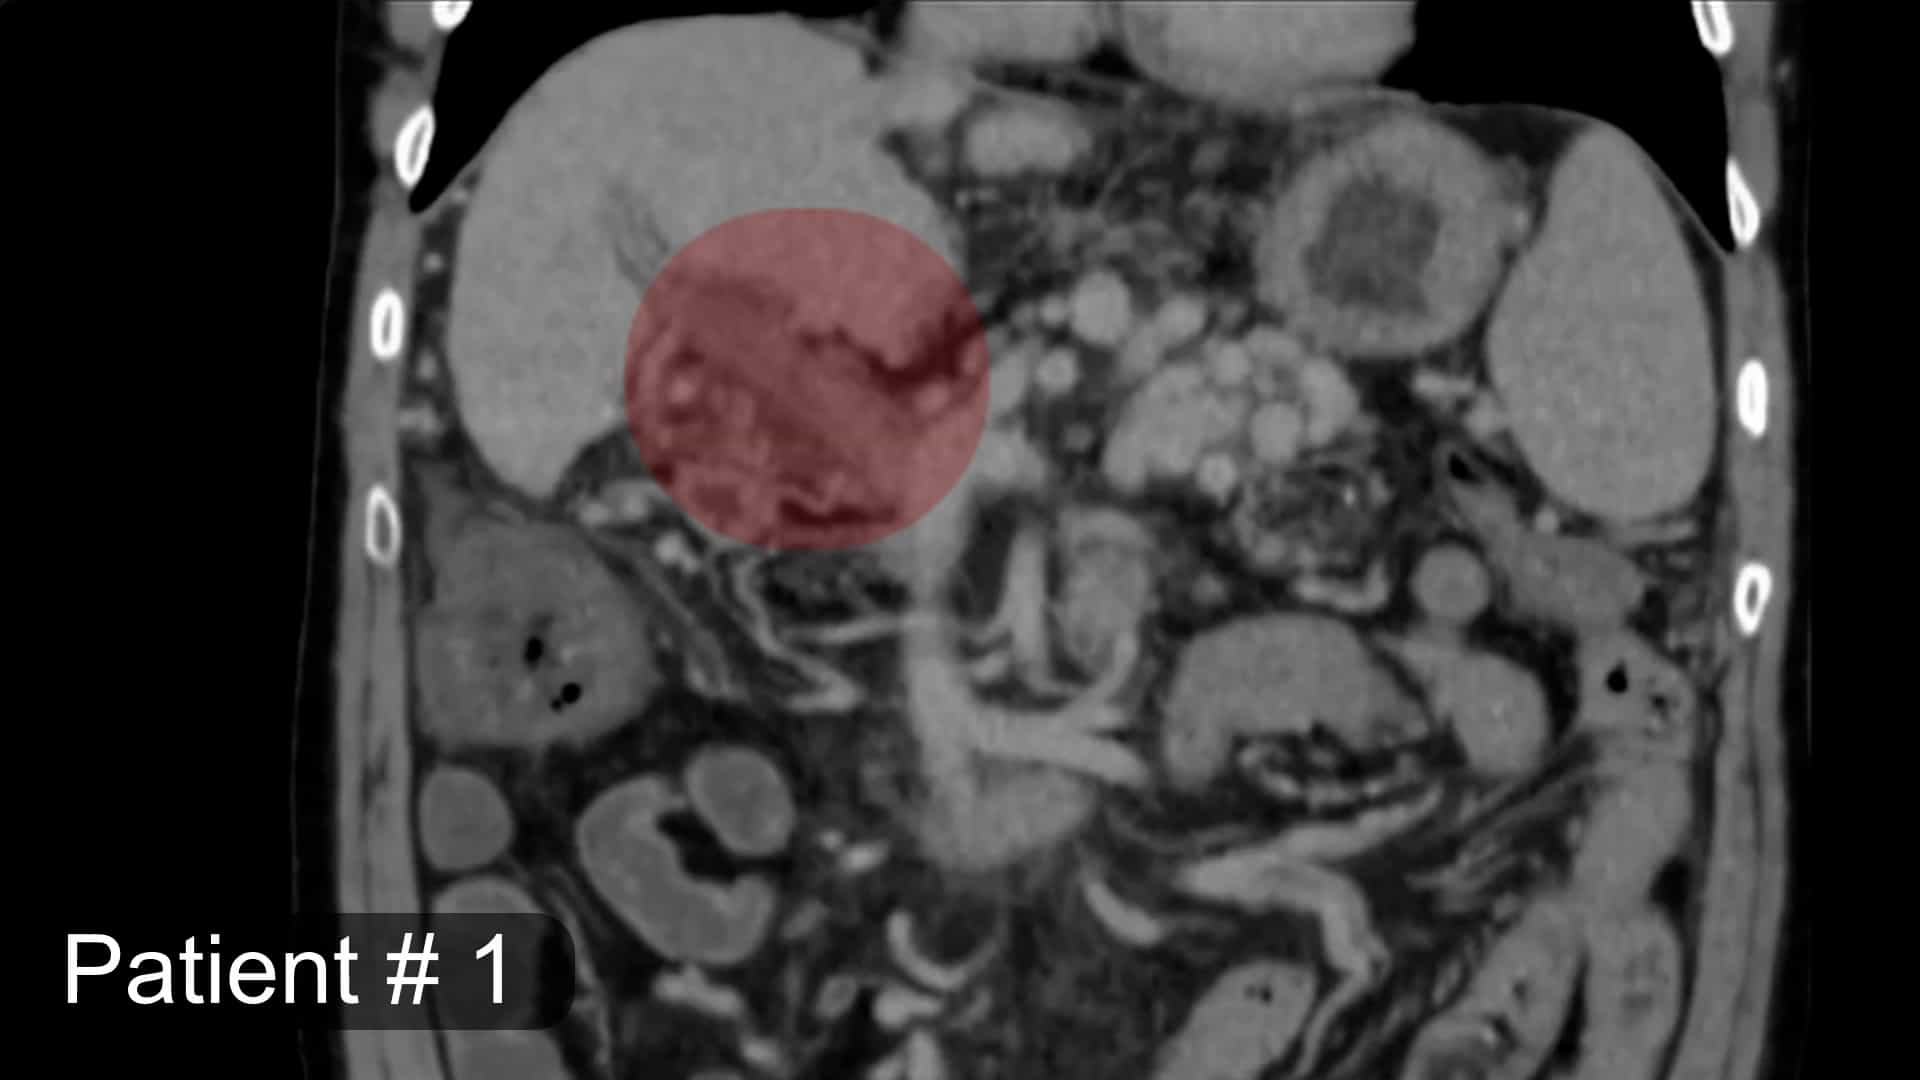
New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
Noncirrhotic portal vein thrombosis exhibits neuropsychological and MR changes consistent with minimal hepatic
Beatriz Mínguez1, Juan Carlos García-Pagán, Jaume Bosch
1Servei de Medicina Interna-Hepatologia, Hospital Universitari Vall d'Hebron, Universitat Autònoma de Barcelona, Barcelona, Spain.

Abstract:
Hepatic encephalopathy can arise from portal-systemic shunting in the absence of intrinsic liver disease. However, there are few descriptions of this form of encephalopathy. Portal vein thrombosis is an infrequent disease that causes portal-systemic shunting. Episodic hepatic encephalopathy has been described in patients with portal vein thrombosis, but it is not known if these patients develop minimal hepatic encephalopathy. We designed a study to investigate the neurological consequences of portal vein thrombosis in patients without cirrhosis and no clinical signs of encephalopathy. For this purpose, 10 patients underwent neuropsychological tests, an oral glutamine challenge test, and brain magnetic resonance (MR) imaging. The results were compared with those obtained in 10 healthy controls. Patients with portal vein thrombosis exhibited abnormalities in the results of neuropsychological tests, oral glutamine challenge test, and MR similar to those described in hepatic encephalopathy associated with cirrhosis. MR spectroscopy revealed a decrease in myo-inositol and an increase in glutamine. The increase in glutamine correlated with an increase in ammonia following the oral glutamine challenge test, signs of increased brain water (decrease in magnetization transfer ratio), and impairment of attention tests. In conclusion, patients with noncirrhotic portal vein thrombosis develop subclinical neurological abnormalities compatible with minimal hepatic encephalopathy. These disturbances, which include signs of increase in brain water and a compensatory osmotic response (decrease in brain myo-inositol), appear to be secondary to brain exposure to ammonia induced by portal-systemic shunting.
Insights
Patients with portal vein thrombosis without cirrhosis show subclinical neurological issues similar to minimal hepatic encephalopathy. These brain changes are linked to ammonia from shunting, impacting cognitive function.
Area of Science:
- Neurology
- Gastroenterology
- Hepatology
Background:
- Hepatic encephalopathy can occur with portal-systemic shunting, even without intrinsic liver disease.
- Portal vein thrombosis (PVT) causes shunting; its effect on minimal hepatic encephalopathy (MHE) is unclear.
- Few studies describe encephalopathy in PVT without cirrhosis.
Purpose of the Study:
- To investigate neurological consequences of PVT in patients without cirrhosis or overt encephalopathy.
- To determine if PVT patients exhibit subclinical MHE.
- To correlate neurological findings with PVT-induced shunting.
Main Methods:
- Neuropsychological tests were performed on 10 PVT patients and 10 controls.
- An oral glutamine challenge test assessed ammonia metabolism.
- Brain magnetic resonance (MR) imaging, including MR spectroscopy, was used.
Main Results:
- PVT patients showed neuropsychological, oral glutamine challenge, and MR abnormalities similar to cirrhotic MHE.
- MR spectroscopy revealed decreased myo-inositol and increased glutamine in PVT patients.
- Increased glutamine correlated with higher ammonia, brain water (decreased MTR), and attention deficits.
Conclusions:
- Noncirrhotic PVT patients develop subclinical neurological abnormalities consistent with MHE.
- Brain changes include increased water and altered osmolytes (myo-inositol decrease).
- These disturbances are likely due to ammonia exposure from shunting.
More Related Videos

Related Concept Videos
 01:29
Hepatic Encephalopathy
 01:22
Portal Hypertension
 01:23
Cirrhosis I: Introduction
 01:24
Cirrhosis II: Pathophysiology
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction