Related Experiment Video
Updated: Aug 7, 2026
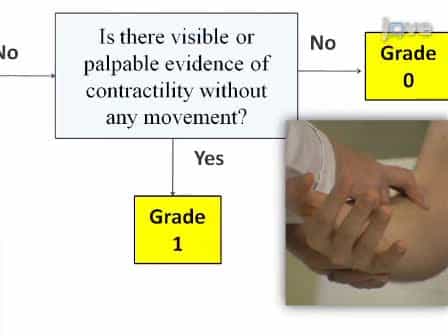

Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
Neurologic complications of critical illness: part II. Polyneuropathies and myopathies
1Department of Critical Care Medicine, Flinders Medical Centre, Adelaide, South Australia.

Objective:
To review the metabolic encephalopathies and neuromuscular abnormalities commonly found in the critically ill patient in a two-part presentation.
Data Sources:
A review of articles reported from 1980 to 2002 and identified through a MEDLINE search on metabolic encephalopathy, polyneuropathy and myopathy in critical illness.
Summary Of Review:
Severe weaknes in the critically ill patient may have many causes, although Guillain-Barré syndrome, critical illness polyneuropathy and critical illness myopathy are the motor disorders commonly found in the critically ill patient. Guillain-Barré syndrome is characterised by an acute ascending weakness 1-3 weeks after a gastrointestinal or upper respiratory tract infection. Intravenous immune globulin (or plasmapheresis) should be initiated as soon as possible to shorten the duration of ventilation, time to walk unaided and halt the progression of the disease. Critical illness polyneuropathy and critical illness myopathy often coexist in the critically ill patient and are probably caused by a small number of activated leucocytes that infiltrate skeletal muscle and produce pro and anti-inflammatory cytokines. Axonal degeneration of both motor and sensory fibres with preservation of the myelin sheath cause the neuropathy, and muscle fibre necrosis and atrophy causes the myopathy. Apart from treatment of the underlying cause (e.g sepsis), there is no specific treatment, although a 44% reduction in the incidence of critical illness polyneuropathy has been described in mechanically ventilated critically ill patients who received intensive insulin therapy to maintain the blood glucose level between 4.4-6.1 mmol/L. Recovery usually occurs over weeks to months depending on the severity of the disease.
Conclusions:
An acute motor weaknesses in the critically ill patient may be caused by Guillain-Barré syndrome, critical illness polyneuropathy or critical illness myopathy. Patients with severe Guillain-Barré syndrome should be managed in an intensive care unit and given intravenous immune globulin. Treatment of critical illness polyneuropathy or myopathy requires largely management of the underlying disorder.

Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:22
Diabetic Neuropathy
 01:22
Myasthenia Gravis ll: Pathophysiology
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology