Related Experiment Video
Updated: Aug 9, 2026
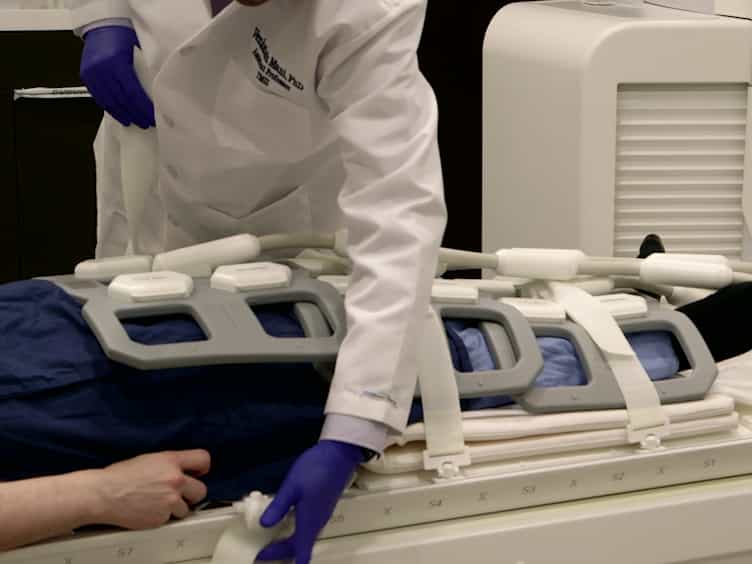
A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
Risk of recurrent venous thromboembolism in patients with common thrombophilia: a systematic review
Wai Khoon Ho1, Graeme J Hankey, Daniel J Quinlan
1Department of Haematology, Royal Perth Hospital and Centre for Clinical Research Excellence, University of Western Australia, Perth.

The 2 most common genetic polymorphisms that predispose to a first episode of venous thromboembolism (VTE) are factor V Leiden (FVL) and prothrombin G20210A. However, the effect of these polymorphisms on the risk of recurrent VTE is unclear. We performed a meta-analysis to obtain best estimates of the relative risk of recurrent VTE associated with these genetic polymorphisms. Electronic and manual searches were used to identify cohort studies of patients with a first episode of VTE that reported the incidence of objectively confirmed recurrence following discontinuation of anticoagulation among those with or without heterozygous FVL or prothrombin G20210A polymorphism. Thirteen reports fulfilled our criteria for inclusion. Pooled results from 10 studies involving 3104 patients with first-ever VTE revealed that FVL was present in 21.4% of patients (95% confidence interval [CI], 20%-23%) and associated with an increased odds of recurrent VTE of 1.41 (95% CI, 1.14-1.75; P = .08 for heterogeneity). Pooled results from 9 studies involving 2903 patients with first-ever VTE revealed that prothrombin G20210A was present in 9.7% of patients (95% CI, 9%-11%) and associated with an increased odds of recurrent VTE of 1.72 (95% CI, 1.27-2.31; P = .19). The estimated population-attributable risk of recurrence for FVL was 9.0% (95% CI, 4.5%-13.2%) and for prothrombin G20210A was 6.7% (95% CI, 3.4%-9.9%). Heterozygous FVL and prothrombin G20210A are each associated with a significantly increased risk of recurrent VTE after a first event, but the magnitude of the increase in risk is modest and by itself is unlikely to merit extended-duration anticoagulation. These data call into question the cost-effectiveness of routine testing for these common inherited thrombophilic polymorphisms among patients with a first episode of VTE.
The 2 most common genetic polymorphisms that predispose to a first episode of venous thromboembolism (VTE) are factor V Leiden (FVL) and prothrombin G20210A. However, the effect of these polymorphisms on the risk of recurrent VTE is unclear. We performed a meta-analysis to obtain best estimates of the relative risk of recurrent VTE associated with these genetic polymorphisms. Electronic and manual searches were used to identify cohort studies of patients with a first episode of VTE that reported the incidence of objectively confirmed recurrence following discontinuation of anticoagulation among those with or without heterozygous FVL or prothrombin G20210A polymorphism. Thirteen reports fulfilled our criteria for inclusion. Pooled results from 10 studies involving 3104 patients with first-ever VTE revealed that FVL was present in 21.4% of patients (95% confidence interval [CI], 20%-23%) and associated with an increased odds of recurrent VTE of 1.41 (95% CI, 1.14-1.75; P = .08 for heterogeneity). Pooled results from 9 studies involving 2903 patients with first-ever VTE revealed that prothrombin G20210A was present in 9.7% of patients (95% CI, 9%-11%) and associated with an increased odds of recurrent VTE of 1.72 (95% CI, 1.27-2.31; P = .19). The estimated population-attributable risk of recurrence for FVL was 9.0% (95% CI, 4.5%-13.2%) and for prothrombin G20210A was 6.7% (95% CI, 3.4%-9.9%). Heterozygous FVL and prothrombin G20210A are each associated with a significantly increased risk of recurrent VTE after a first event, but the magnitude of the increase in risk is modest and by itself is unlikely to merit extended-duration anticoagulation. These data call into question the cost-effectiveness of routine testing for these common inherited thrombophilic polymorphisms among patients with a first episode of VTE.
Related Concept Videos
 01:30
Venous Thrombosis I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:30
Venous Thrombosis IV: Nursing Management
 01:19
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism I: Introduction