[Homeostatic conditions affect the protective effect of edaravone on ischemic injury in neurons]

Xin Hu1, Qiu-fu Ge, Lei Zhang

  • 1Department of Pharmacology, College of Medicine, Zhejiang University, Hangzhou 310031, China.

Abstract

Related Concept Videos

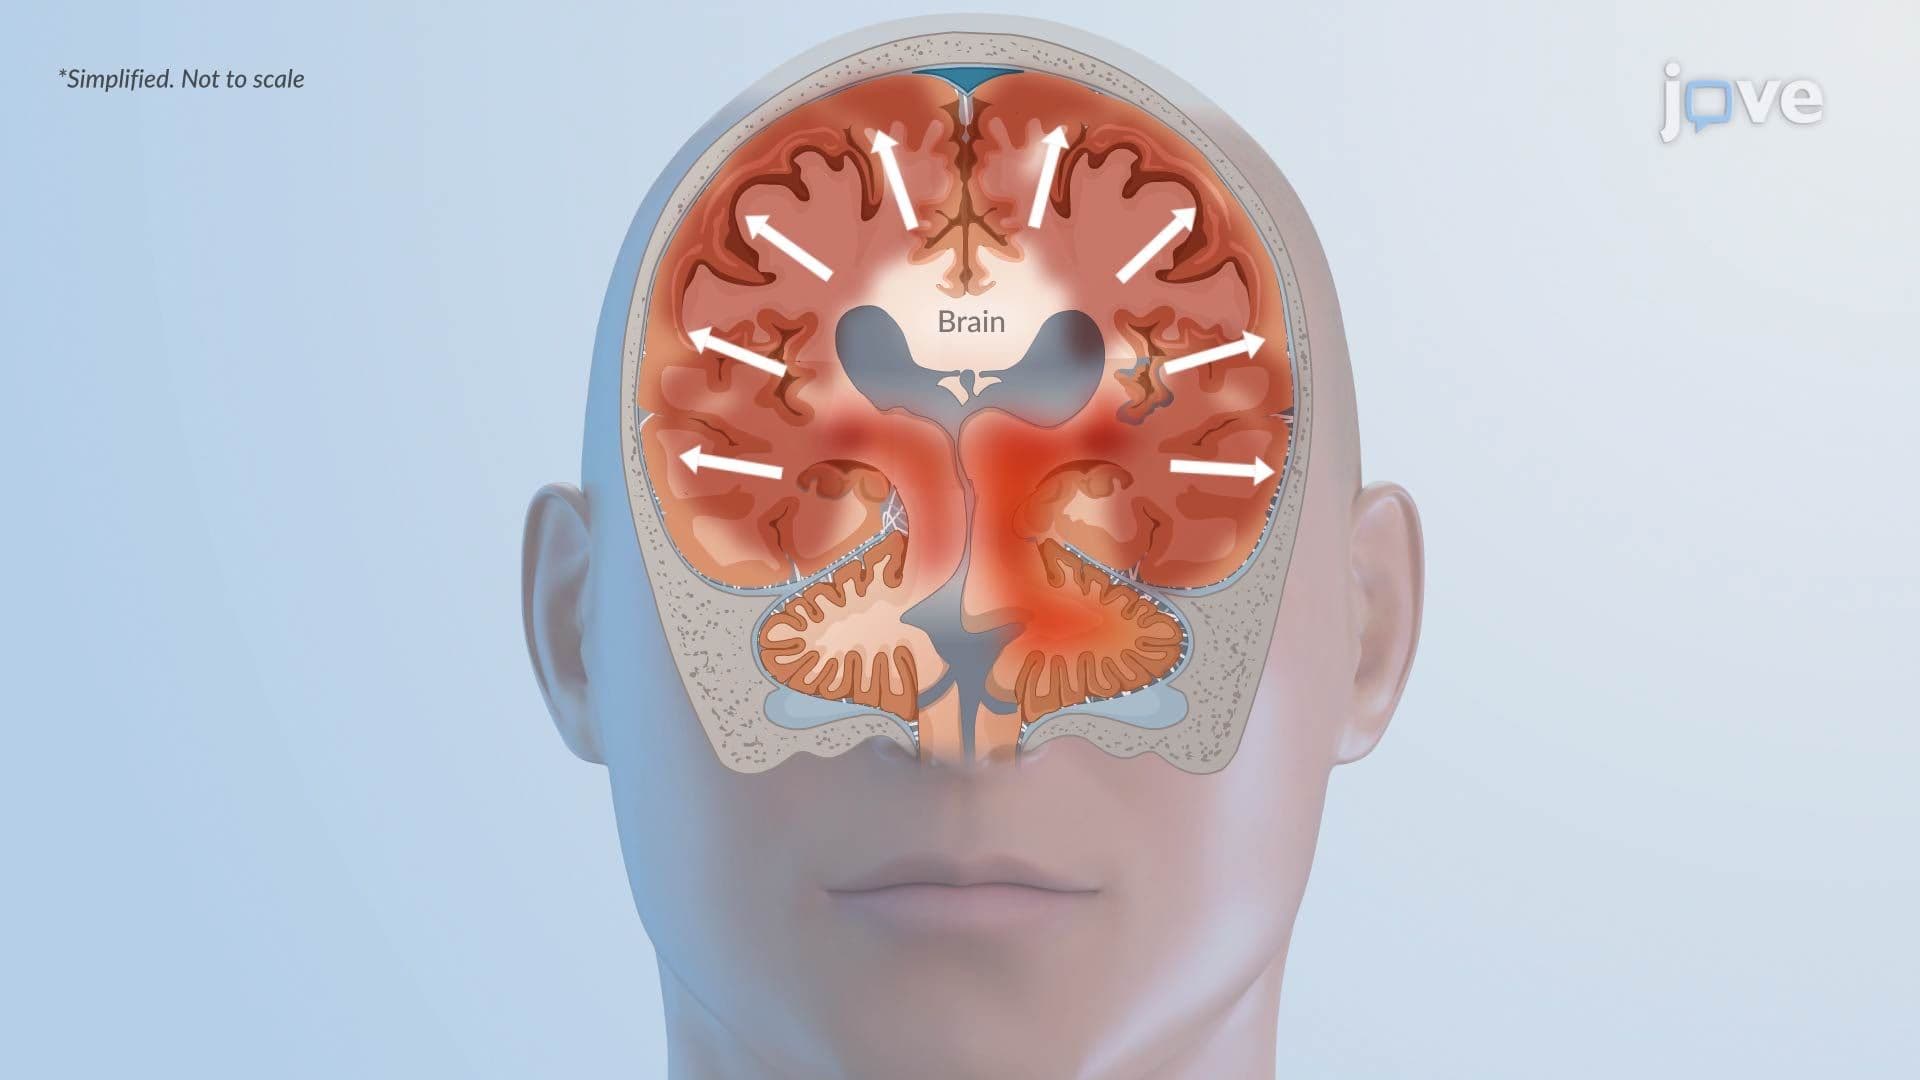
Cytotoxic Edema: Pathophysiology01:21

Cytotoxic Edema: Pathophysiology

Cytotoxic edema is a form of cerebral edema characterized by intracellular swelling of neurons, astrocytes, and other glial cells. It develops when the mechanisms responsible for maintaining ionic gradients across the cell membrane become impaired. Under normal physiological conditions, the sodium–potassium ATPase actively transports sodium ions out of the cell and potassium ions into the cell, preserving osmotic balance and enabling electrical signaling. This pump requires a continuous supply...
Ischemic Stroke ll: Pathophysiology01:15

Ischemic Stroke ll: Pathophysiology

An ischemic stroke occurs when a cerebral blood vessel becomes obstructed, most often by a thrombus or embolus, interrupting the delivery of oxygen and glucose to brain tissue. Because neurons rely on continuous aerobic metabolism, energy failure begins within minutes of reduced perfusion. The region receiving the least blood flow becomes the infarct core, an area of irreversible cellular death. Surrounding this core lies the penumbra, a zone of hypoperfused but still viable tissue that is...
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System01:26

Heart Failure Drugs: Inhibitors of Renin-Angiotensin System

The activation of the sympathetic nervous system and the renin-angiotensin-aldosterone system (RAAS) contributes to cardiac remodeling, and inhibiting the RAAS is a pharmacological target in heart failure management. As a result, neurohumoral modulation is a crucial treatment principle for managing heart failure. This approach involves using medications like ACE inhibitors (ACEIs), angiotensin receptor blockers (ARBs), β-blockers, mineralocorticoid receptor antagonists (MRAs), and neutral...
Secondary Spinal Cord Injury llI: Pathophysiology01:25

Secondary Spinal Cord Injury llI: Pathophysiology

Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...
Cerebral Edema ll: Pathophysiology01:22

Cerebral Edema ll: Pathophysiology

Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment01:08

Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment

Hepatic impairment, characterized by decreased liver function, does not uniformly mandate adjustments in drug dosage. Whether dosage modifications are necessary depends on various factors related to the drug's metabolism and elimination pathways. If a drug is primarily excreted via the kidneys and bypasses significant hepatic processing, if it undergoes minimal metabolic transformation in the liver, or if it is volatile and primarily expelled through the lungs, dose adjustments may not be...