Related Experiment Video
Updated: Aug 9, 2026

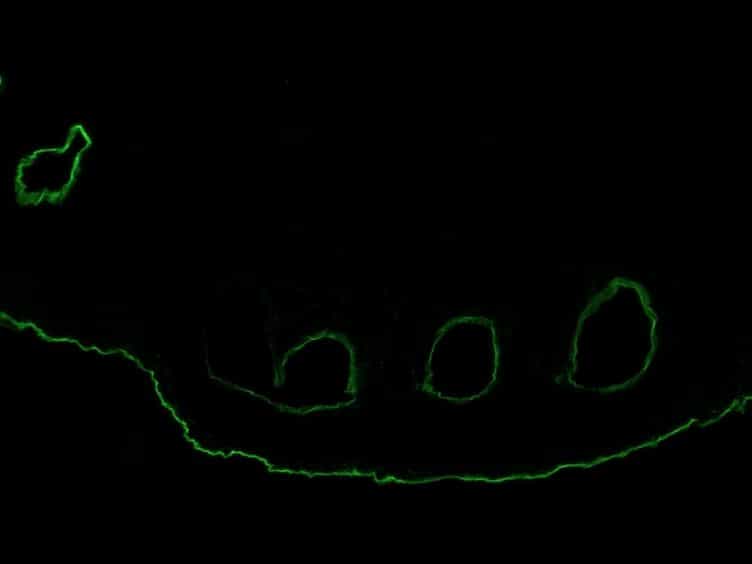
Recognition of Epidermal Transglutaminase by IgA and Tissue Transglutaminase 2 Antibodies in a Rare Case of Rhesus Dermatitis
Published on: December 15, 2011
Skin immunoglobulin deposition following intravenous immunoglobulin therapy in toxic epidermal necrolysis
1Department of Dermatopathology, University Hospital of Liège, Liège, Belgium. p.paquet@chu.ulg.ac.be

Human intravenous immunoglobulins (IVIg) which contain anti-CD95 antibodies have been proposed to treat toxic epidermal necrolysis (TEN). Presently, there is no evidence that IVIg reach the keratinocytes in TEN patients. The aim of this study was to assess the Ig distribution in the serum, blister fluid and skin of six consecutive TEN patients treated with IVIg (1 g/kg/day) for 3 days. They were compared with five TEN patients who only received supportive therapy. In all patients, IgA, IgM and IgG concentrations were measured in the serum and blister fluid using an immuno-nephelometric method. Immunohistochemistry was performed on skin biopsies taken from both TEN clinically involved and uninvolved skin to search for IgG deposits. On admission, the IgG concentrations were significantly higher in both TEN serum and TEN blister fluid compared with their respective IgA and IgM contents. The IgG, IgA and IgM concentrations in blister fluid were significantly lower than their respective serum concentrations. The serum and blister fluid IgG concentrations, but not that of IgA and IgM, were markedly increased at the completion of the IVIg treatment. By contrast, they remained unchanged in the TEN patients that were untreated with IVIg. In the IVIg-treated patients, the IgG intraepidermal deposits raised markedly in both TEN-involved and uninvolved skin. This was not the case in patients who did not receive IVIg. These results suggest that IVIg perfusions brought a prominent increase in IgG concentration in the serum, blister fluid and epidermis of both TEN-involved and clinically uninvolved skin. The presence of potentially protective IgG in TEN epidermis following IVIg treatment could help limiting the disease progression.
Human intravenous immunoglobulins (IVIg) which contain anti-CD95 antibodies have been proposed to treat toxic epidermal necrolysis (TEN). Presently, there is no evidence that IVIg reach the keratinocytes in TEN patients. The aim of this study was to assess the Ig distribution in the serum, blister fluid and skin of six consecutive TEN patients treated with IVIg (1 g/kg/day) for 3 days. They were compared with five TEN patients who only received supportive therapy. In all patients, IgA, IgM and IgG concentrations were measured in the serum and blister fluid using an immuno-nephelometric method. Immunohistochemistry was performed on skin biopsies taken from both TEN clinically involved and uninvolved skin to search for IgG deposits. On admission, the IgG concentrations were significantly higher in both TEN serum and TEN blister fluid compared with their respective IgA and IgM contents. The IgG, IgA and IgM concentrations in blister fluid were significantly lower than their respective serum concentrations. The serum and blister fluid IgG concentrations, but not that of IgA and IgM, were markedly increased at the completion of the IVIg treatment. By contrast, they remained unchanged in the TEN patients that were untreated with IVIg. In the IVIg-treated patients, the IgG intraepidermal deposits raised markedly in both TEN-involved and uninvolved skin. This was not the case in patients who did not receive IVIg. These results suggest that IVIg perfusions brought a prominent increase in IgG concentration in the serum, blister fluid and epidermis of both TEN-involved and clinically uninvolved skin. The presence of potentially protective IgG in TEN epidermis following IVIg treatment could help limiting the disease progression.
Related Concept Videos
 01:19
Hypersensitivity Reactions: Immune-Complex Reactions
 01:29
Hypersensitivity Reactions: Delayed Hypersensitivity Reactions
 01:19
Clinical Applications of Epidermal Stem Cells
 01:01
Hypersensitivity Reactions: Cytolytic Reactions
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency disorders...
 01:23
Skin Diseases and Disorders
Gram-positive Staphylococcus spp. and Streptococcus spp. are responsible for many of the most common skin infections. However, many...