Related Experiment Video
Updated: Aug 9, 2026

Transforaminal Full-Endoscopic Lumbar Foraminotomy Under Local Anesthesia for L5/S1 Adjacent Segment Foraminal Stenosis
Published on: October 17, 2025
[Influence factors of adjacent segment degeneration after instrumented lumbar fusion]
Chun-de Li1, Zheng-rong Yu, Xian-yi Liu
1Department of Orthopedics, Beijing University First Hospital, Beijing 100034, China.

Objective:
To investigate the influence factors of adjacent segment degeneration (ASD) after instrumented lumbar fusion.
Methods:
Thirty-three patients who had undergone an instrumented lumbar fusion from March 1998 to May 2002 were reviewed. The incidence, age, position, radiographic characteristics and clinical manifestations of ASD were studied. Then the relations between "floating fusion" and ASD were compared, the range of fusion and ASD and investigated the incidences of different adjacent segments.
Results:
The mean follow-up period for the patients was 4 years and 7 months (24 - 82 months). Adjacent segment degeneration mainly occurred in patients older than 60. Ten patients (10%) were found to have radiographic characteristics of ASD. Nine of the ten patients had ASD at cranial segments. Using "floating fusion" or not did not show difference in the risk of ASD. There was a trend of more ASDs after long-segment fusion than short-segment fusion. As an adjacent segment, L(2)/L(3) had a high risk of ASD, while L(5)/S(1) had a much lower risk.
Conclusions:
The cranial segment has a higher degeneration risk than the caudal segment. If L(2)/L(3) has degenerative appearance and has chance to be the adjacent segment, we'd better fuse it. If there is no evidence of obvious degeneration, L(5)/S(1) should not be fused. During instrumented lumbar fusion, long-segment fusion should be avoided if possible.
Related Concept Videos
 01:23
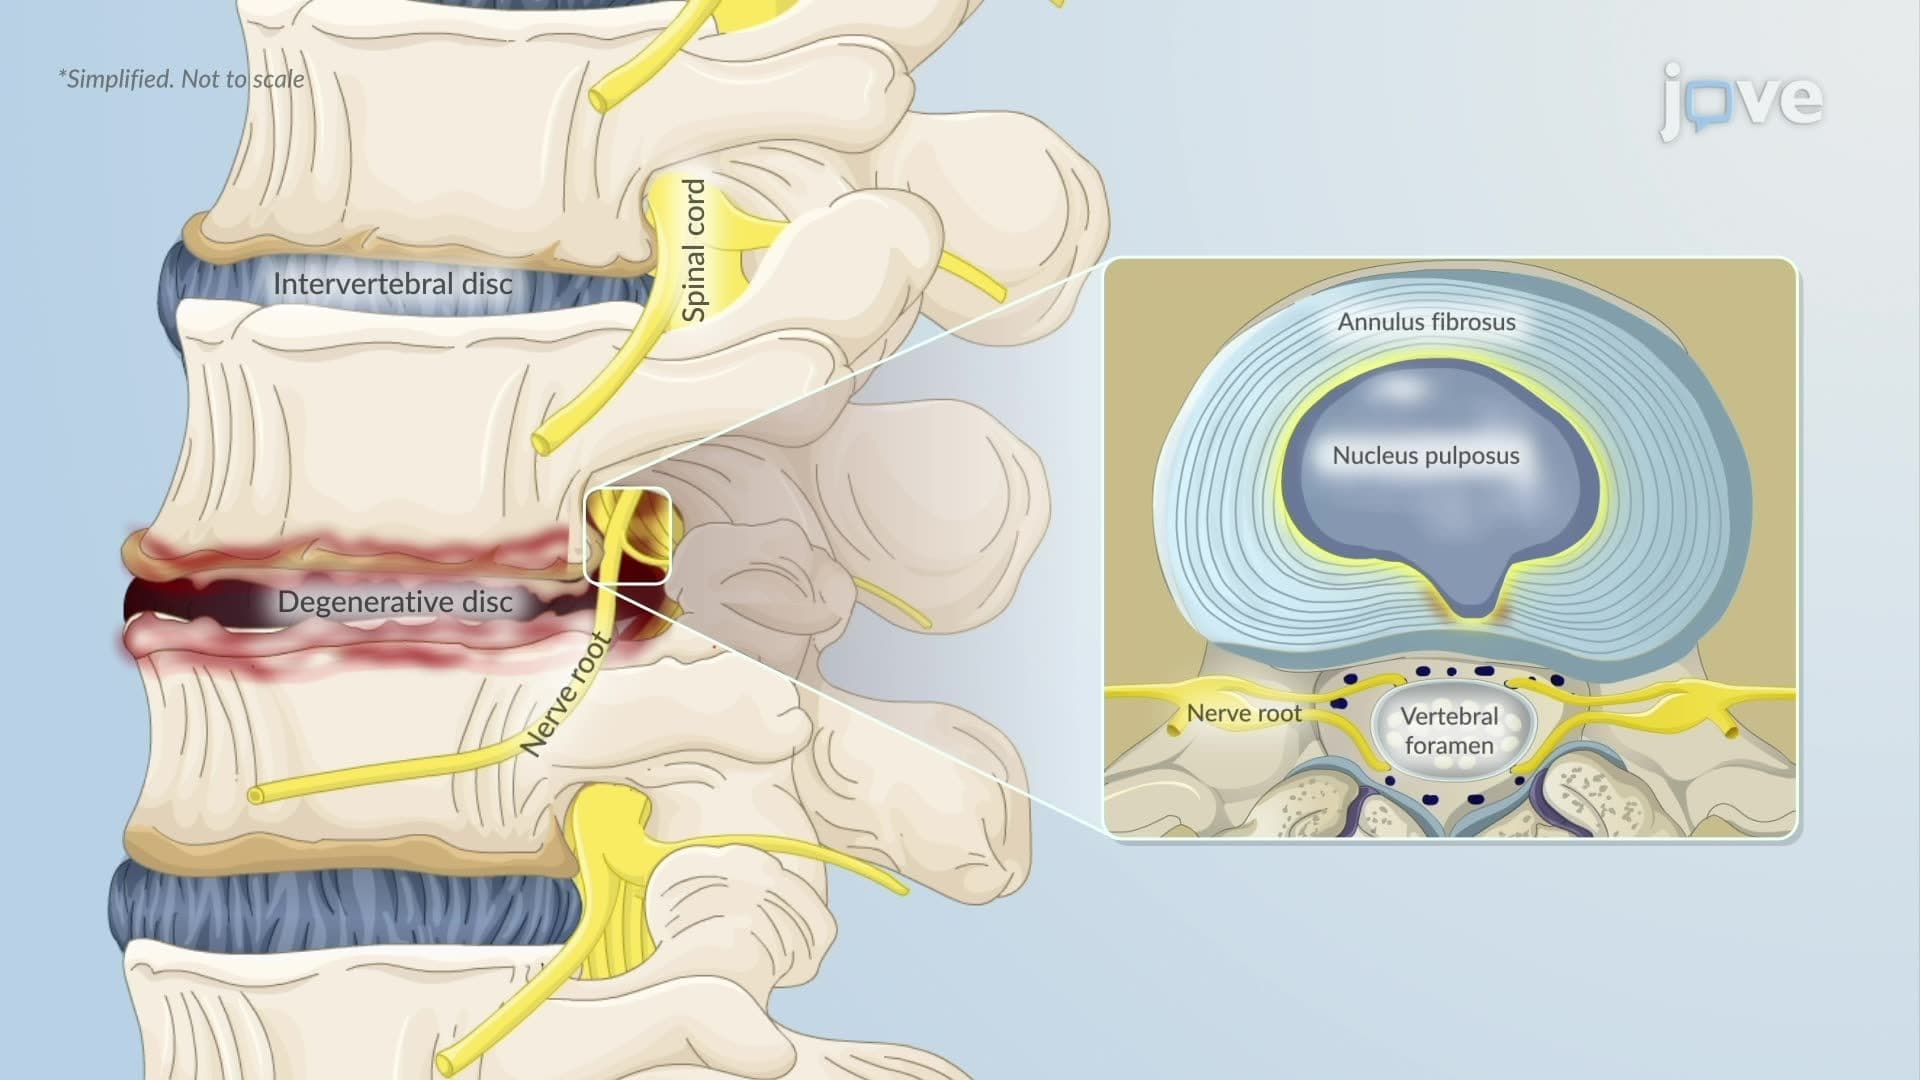
Degenerative Disc Disease ll: Pathophysiology
 01:27
Degenerative Disc Disease I: Introduction