Related Experiment Video
Updated: Aug 8, 2026
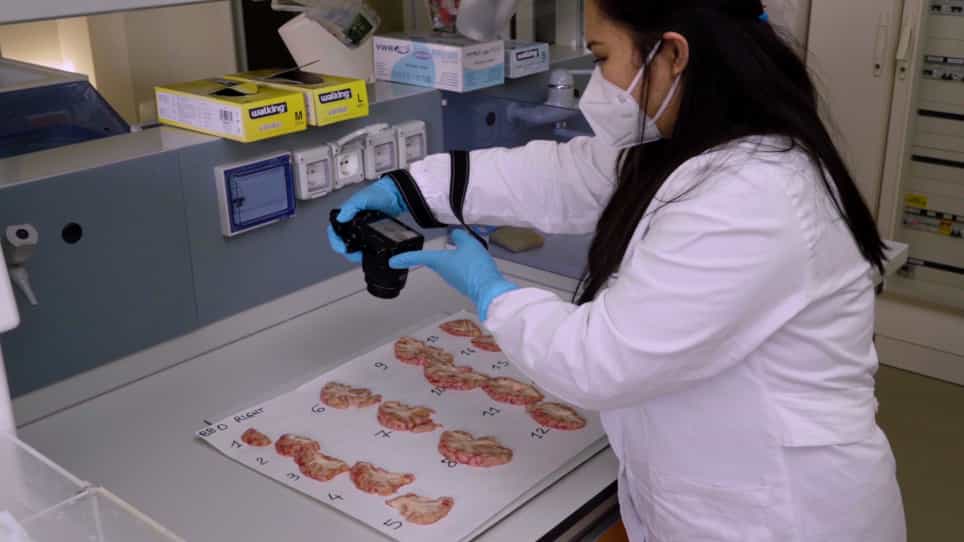
Abbiategrasso Brain Bank Protocol for Collecting, Processing and Characterizing Aging Brains
Published on: June 3, 2020
Idiopathic atrophie blanche
Lauretta Amato1, Caterina Chiarini, Samantha Berti
1Department of Dermatological Sciences, University of Florence, Florence, Italy.

Abstract:
A 41-year-old woman presented with a 3-year history of purpuric lesions followed by superficial, painful ulcers and development of lesions on the lower legs and on the dorsa of the feet, particularly in the summer. The patient was asymptomatic during the winter months. On physical examination she had irregular, scleroatrophic, white-ivory, coalescent lesions on a livedoid basis, with purpuric and, in some lesions, pigmented borders with numerous telangiectatic capillaries. These lesions were localized on the medial sides of the lower legs and on the dorsa of the feet (Figure 1). Laboratory investigations were normal or negative, including complete blood cell count, platelets, coagulation indexes, erythrocyte sedimentation rate, serum immunoglobulins, antinuclear antibodies, anti-double-stranded DNA, anticardiolipin, antiphospholipids, antineutrophilic cytoplasmic antibodies, circulating immunocomplexes, complement fractions (C3, C4), cryoglobulins, rheumatoid factor, and Rose-Waaler reaction. The only laboratory abnormality was an elevated fibrinogen level (472 mg/dL). Doppler velocimetry excluded a chronic venous insufficiency. Thoracic x-ray and abdominal ultrasound were normal. A digital photoplethysmograph revealed functional Raynaud's phenomenon. A biopsy specimen taken from a purpuric lesion showed an atrophic epidermis with parakeratosis and focal spongiosis. An increased number of small-sized vessels were observed within a sclerotic dermis. Most of the vessels in the upper dermis were dilated and showed endothelial swelling; some were occluded due to amorphous hyaline microthrombi (Figure 2). There were fibrinoid deposits around the vessels with thickening of the vessel walls. Extravasated erythrocytes were found throughout the upper and mid-dermis. There was a sparse perivascular lymphocytic infiltrate but no vasculitis. Direct immunofluorescence showed a perivascular microgranular deposit of IgM (+), C3 (++), and fibrinogen/fibrin (+++). On the basis of clinical, serologic, histopathologic, and immunopathologic findings, a diagnosis of idiopathic atrophie blanche was made. The patient was treated with dapsone (50 mg p.o. q.d.) and pentoxifylline (400 mg p.o. t.i.d.) with pain relief and complete resolution of the ulcerations after 6 weeks of therapy.
Related Concept Videos
 01:23
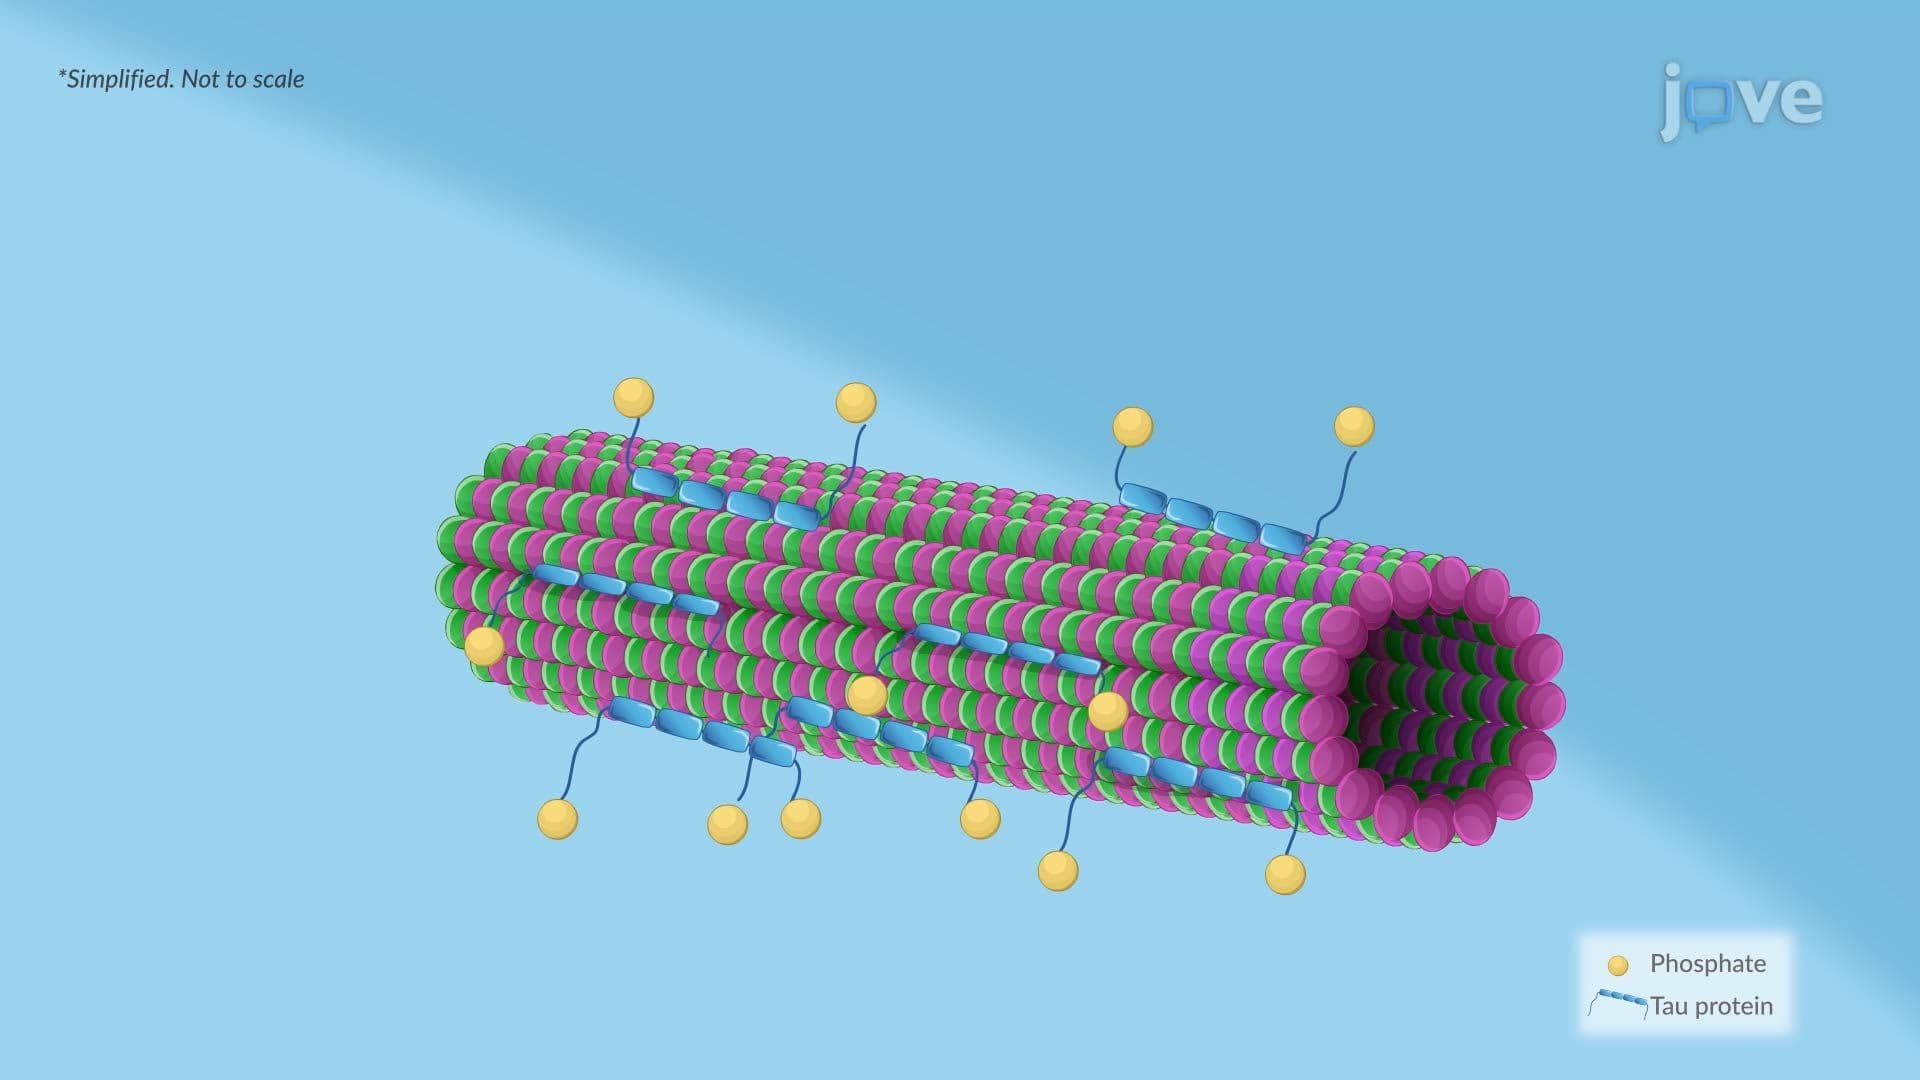
Alzheimer Disease ll: Pathophysiology
 01:23
Cellular Adaptation I: Introduction and Atrophy
 01:22
Myasthenia Gravis ll: Pathophysiology
 01:29
Alzheimer Disease l: Introduction
 01:22
Photoreceptors and Visual Pathways
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which leads...