Related Experiment Video
Updated: Jun 22, 2026

Analysis of Nephron Composition and Function in the Adult Zebrafish Kidney
Published on: August 9, 2014
Renal bicarbonate reabsorption and hydrogen ion excretion in normal infants
C M Edelmann1, J R Soriano, H Boichis
1Department of Pediatrics, Albert Einstein College of Medicine-Bronx Municipal Hospital Center, Bronx, N. Y.

Insights
Infants can acidify urine similarly to older children, but have a lower bicarbonate threshold. This is likely due to differences in nephron function, not limited hydrogen excretion capacity.
Area of Science:
- Pediatric Nephrology
- Renal Physiology
Background:
- Infants exhibit "physiologic acidosis," a state whose causes are not fully understood.
- Previous research suggests potential renal limitations in hydrogen ion excretion or bicarbonate reabsorption.
Purpose of the Study:
- To investigate the renal capacity for urine acidification and bicarbonate reabsorption in infants.
- To determine the underlying mechanisms of "physiologic acidosis" in early life.
Main Methods:
- Acute ammonium chloride administration to infants (1-16 months).
- Urine acidification assessment, including titratable acid and ammonium excretion.
- Bicarbonate titration studies to evaluate reabsorption thresholds and rates.
- Analysis of glomerular filtration rate (GFR) to tubular reabsorptive capacity (TRC) ratios.
Main Results:
- Infants demonstrated similar urine acidification capacity to older children, with comparable total hydrogen ion excretion.
- Infants showed higher titratable acid and lower ammonium excretion rates.
- Bicarbonate titration revealed a low renal plasma bicarbonate threshold (21.5-22.5 mmol/L) and significant titration splay.
- Nephron heterogeneity, with a rightward skew in GFR/TRC ratios, indicated nephrons with reduced transport capacity.
Conclusions:
- The "physiologic acidosis" of infancy is not due to limited renal hydrogen excretion or reduced bicarbonate reabsorption capacity.
- A low renal plasma bicarbonate threshold, influenced by nephron functional and morphologic heterogeneity, is the primary cause.
- This low threshold impacts bicarbonate reabsorption kinetics during infancy.
Abstract:
After acute administration of ammonium chloride, infants 1 to 16 months of age were similar to older children in their capacity to acidify their urine. The infants had a higher rate of excretion of titratable acid and a lower rate of excretion of ammonium but were similar in their rate of excretion of total hydrogen ion.Bicarbonate titrations performed in infants during the first year of life demonstrated a threshold ranging from 21.5 to 22.5 mmoles per L, maximal rate of reabsorption from 2.6 to 2.9 mmoles per 100 ml glomerular filtrate, and marked titration splay. A nephronic frequency distribution curve of the ratio of glomerular filtration rate to tubular reabsorptive capacity demonstrated both heterogeneity and skewing to the right, suggesting the presence of significant numbers of nephrons with low tubular transport capacity relative to filtration rate.It is suggested that the "physiologic acidosis" of the infant is due neither to a limited renal capacity to excrete hydrogen ion nor to a reduced capacity for reabsorption of bicarbonate, but rather to a low renal plasma bicarbonate threshold. Although the level of the threshold may relate to the kinetics of bicarbonate reabsorption during this period, it appears to be due at least in part to functional and morphologic heterogeneity of nephrons.
More Related Videos
Related Concept Videos
 01:22
Drug Elimination by Renal Route: Tubular Reabsorption
 01:28
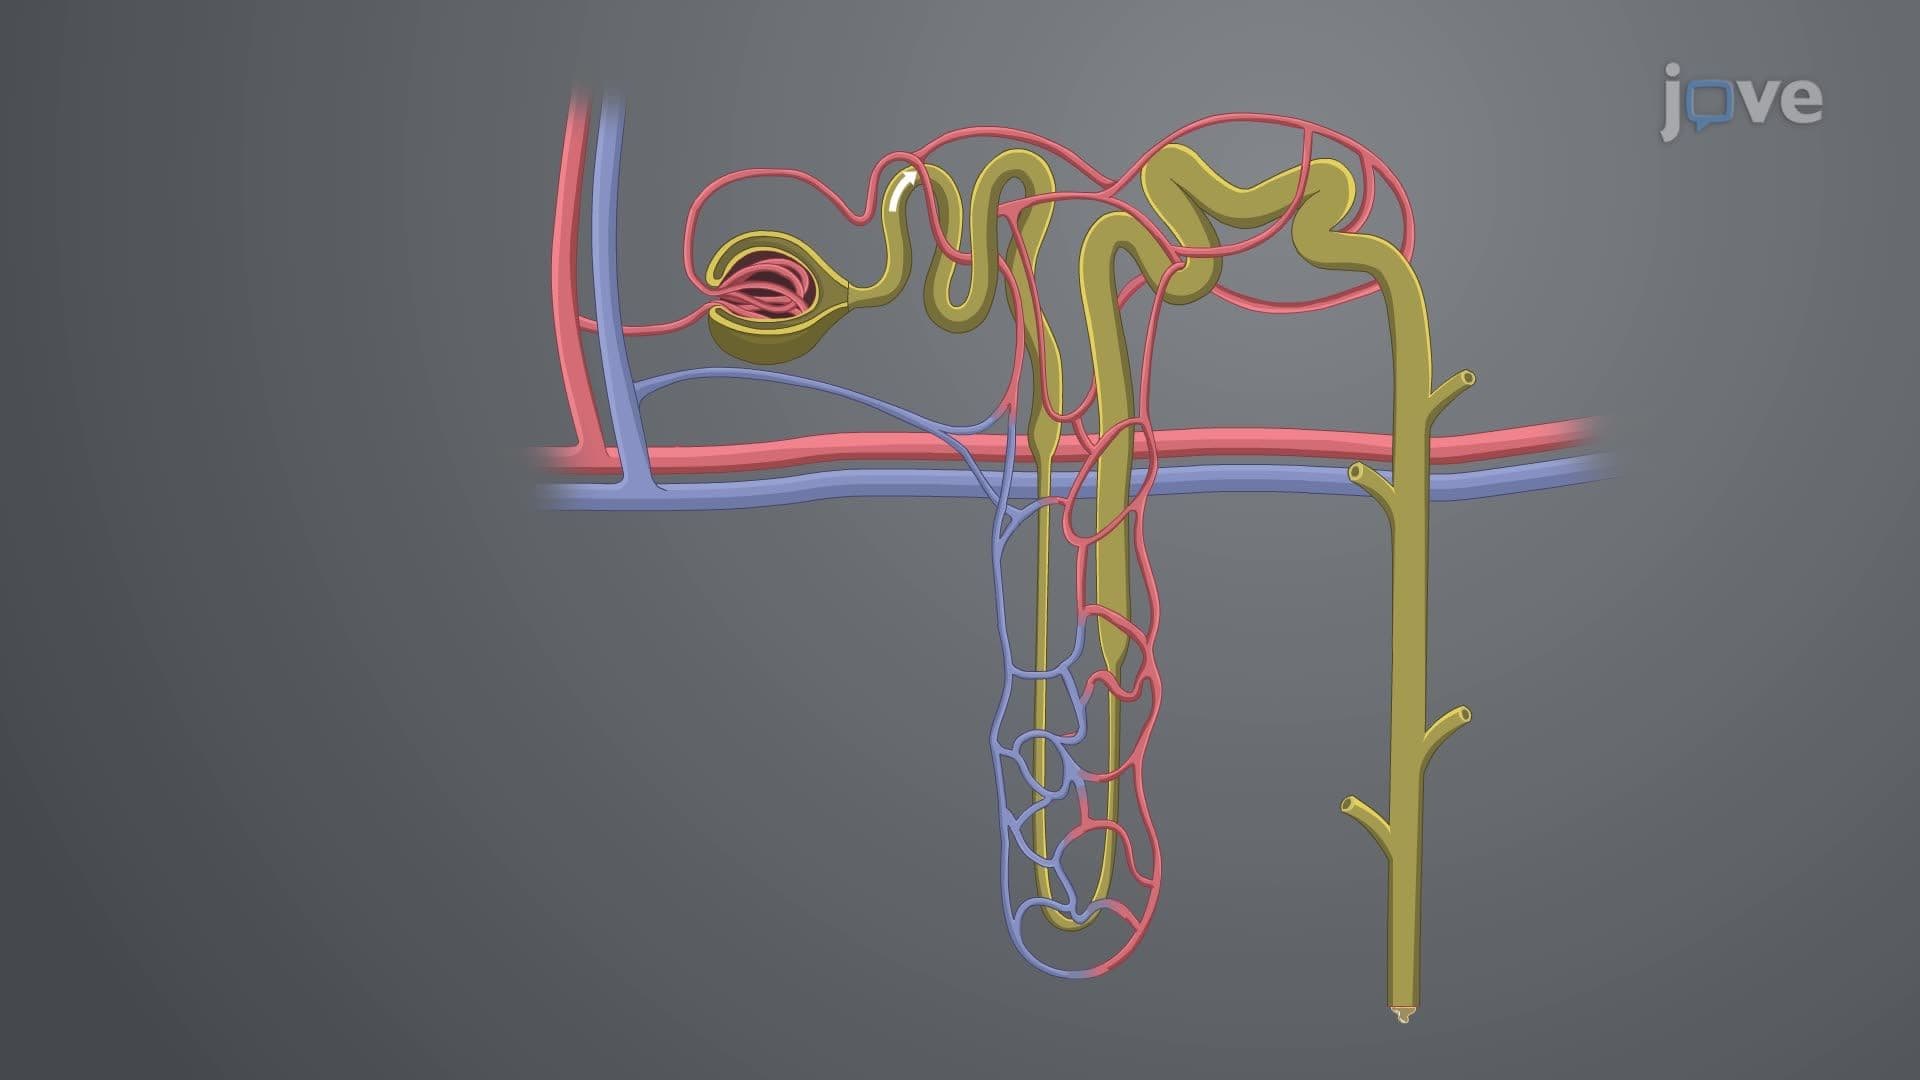
Tubular Reabsorption and Secretion
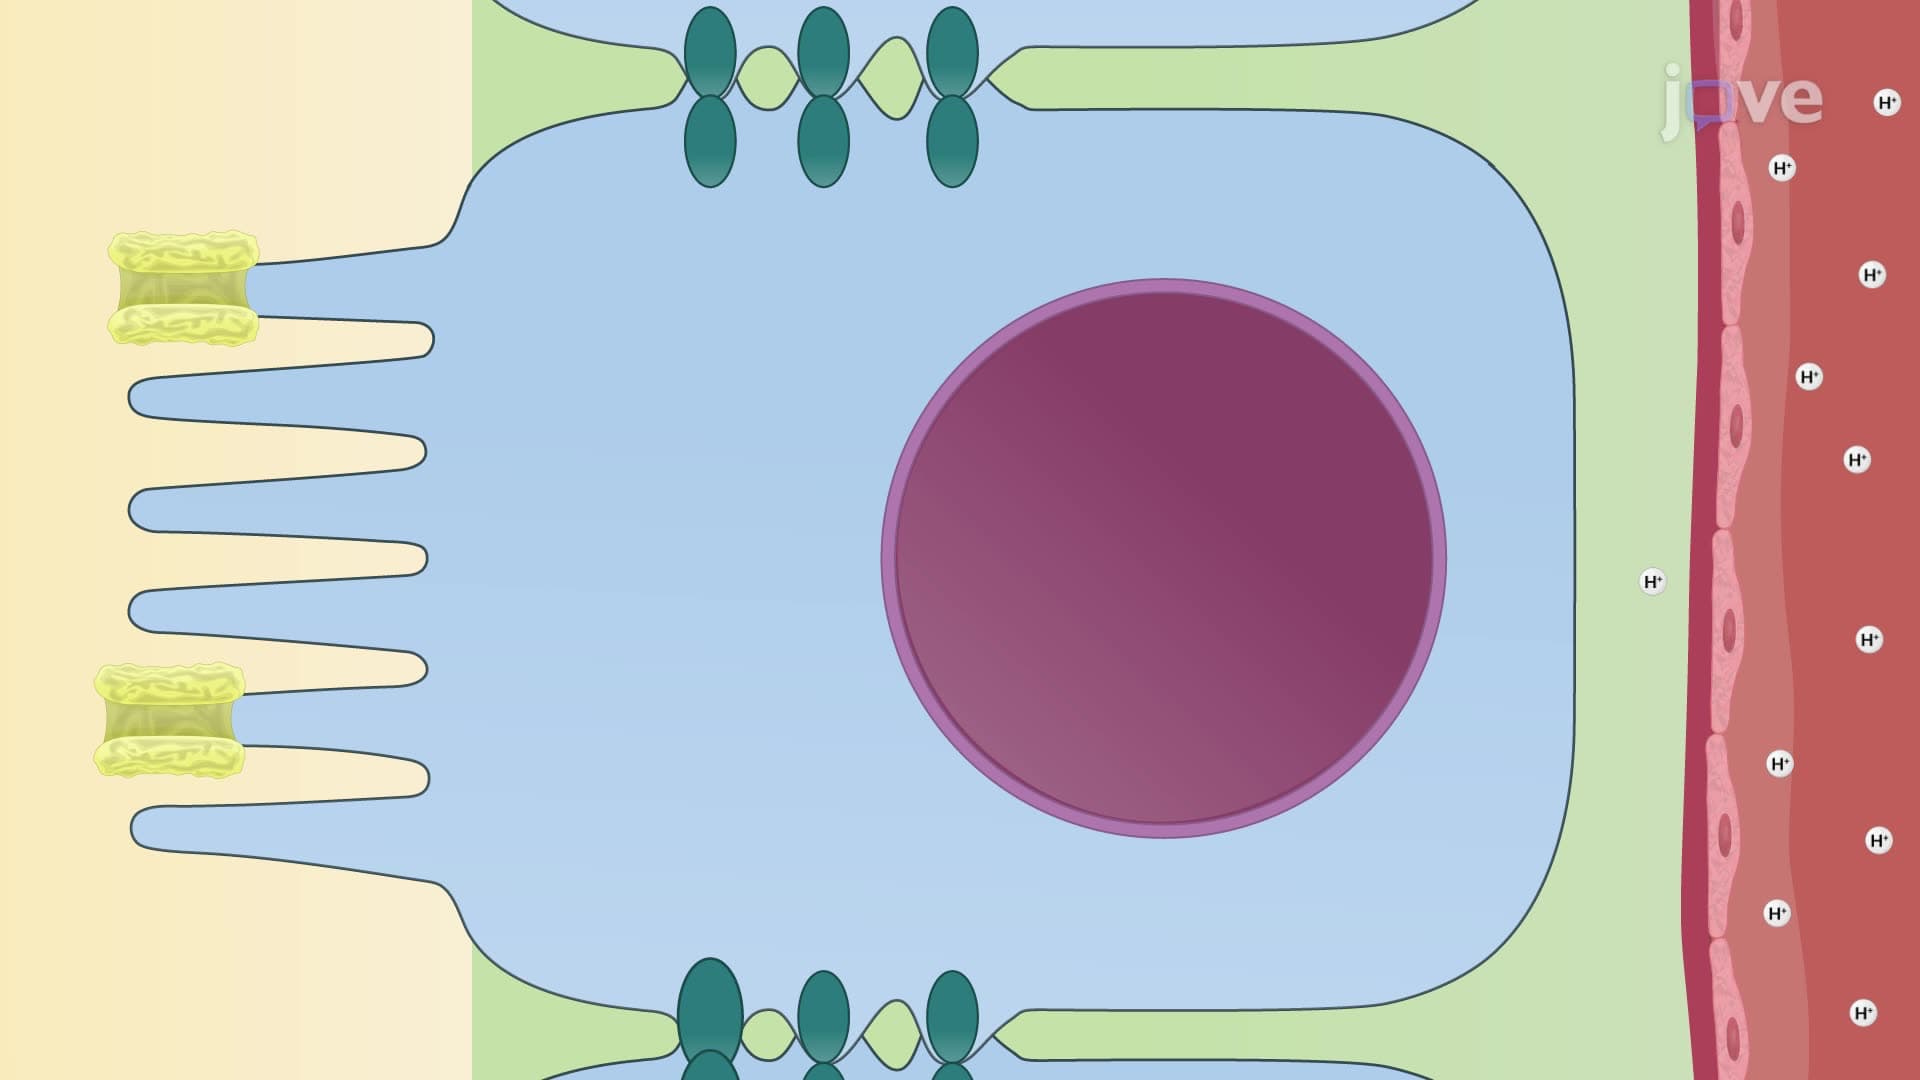
Tubular reabsorption is a selective process that starts when the filtrate enters the proximal tubules. It involves substances traveling through the transcellular route (through the tubule cell and peritubular...
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting, or...
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:29
Renal Regulation of Acid-Base Balance
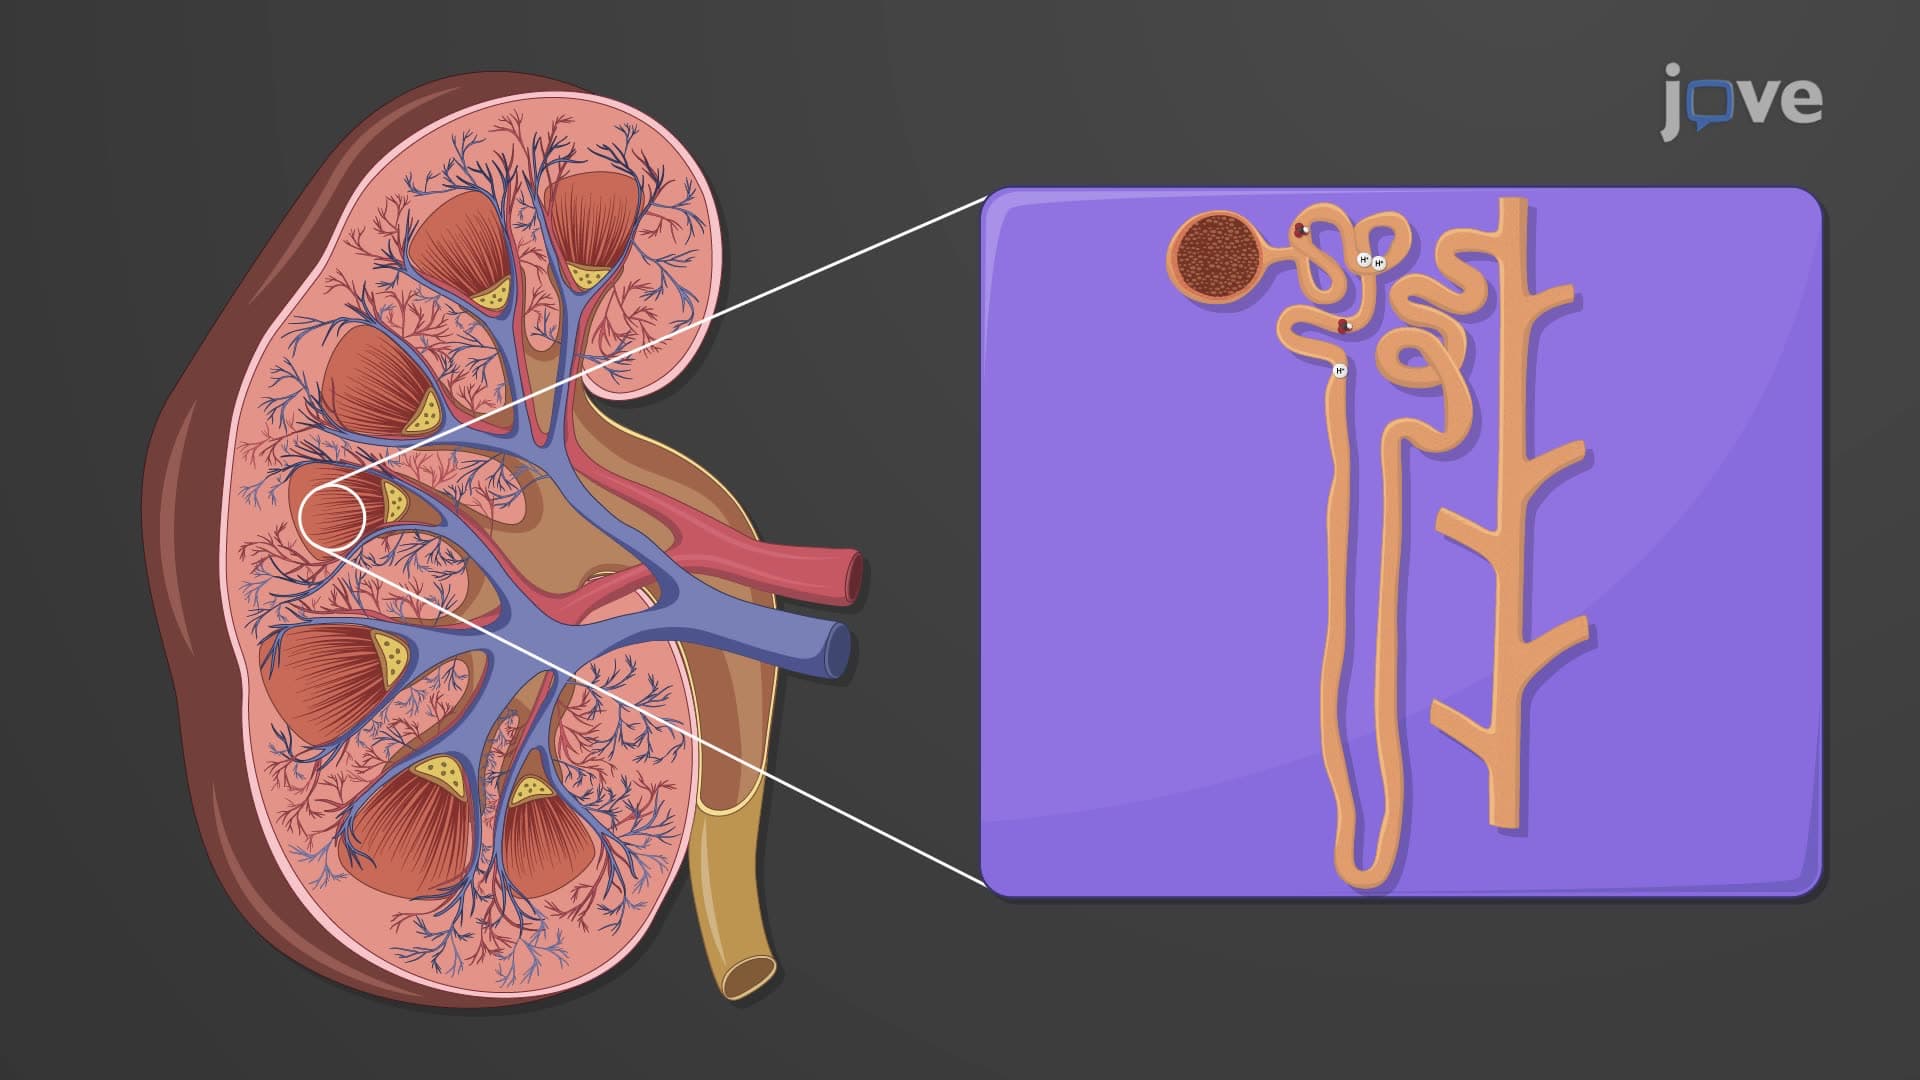
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:22
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion