Related Experiment Video
Updated: Jun 26, 2026

Real-time Pressure-volume Analysis of Acute Myocardial Infarction in Mice
Published on: July 2, 2018
Studies in clinical shock and hypotension: VI. Relationship between left and right ventricular function
J N Cohn1, F E Tristani, I M Khatri
1Hypertension and Clinical Hemodynamics Section, Veterans Administration Hospital, Washington, D. C. 20422.

Abstract:
Left ventricular end diastolic (LVEDP) and mean right atrial (RAP) pressures were recorded simultaneously in 30 patients with shock (14 acute myocardial infarction, 10 acute pulmonary embolism or severe bronchopulmonary disease, and 6 sepsis). Myocardial infarction was characterized by a predominant increase in LVEDP, pulmonary disease by a predominant increase in RAP, and sepsis by a normal relationship between LVEDP and RAP. In all three groups a significant positive correlation was noted between RAP and LVEDP, with the regression line in cor pulmonale deviated significantly toward the RAP axis and the regression line in myocardial infarction exhibiting a zero RAP intercept at an elevated LVEDP.Low cardiac outputs with elevated LVEDP in myocardial infarction indicated severe left ventricular failure. Low outputs with elevated RAP in cor pulmonale were consistent with right ventricular overload. Although cardiac outputs often were normal in sepsis, low outputs with elevated cardiac filling pressures in some patients were consistent with a hemodynamic or humoral-induced generalized depression of cardiac performance.Vasoconstrictor and inotropic drugs often produced a functional disparity between the two ventricles, with the gradient between LVEDP and RAP increasing, apparently because of an increase in left ventricular work or an inadequacy of left ventricular oxygen delivery. Acute plasma volume expansion with dextran in patients with pulmonary vascular disease resulted in a somewhat more rapid rise in RAP than in LVEDP. In septic and myocardial infarction shock, however, LVEDP and RAP usually rose proportionally, with the absolute rise of LVEDP surpassing that of RAP. Although the absolute level of the central venous pressure thus may not be a reliable indicator of left ventricular function in shock, changes in venous pressure during acute plasma volume expansion should serve as a fairly safe guide to changes in LVEDP.

Related Concept Videos
 01:19
Assessing Blood pressure using a doppler ultrasound
Pre-Procedural Guidelines for Doppler Ultrasound Blood Pressure Assessment:
Preparation of Equipment:
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:26
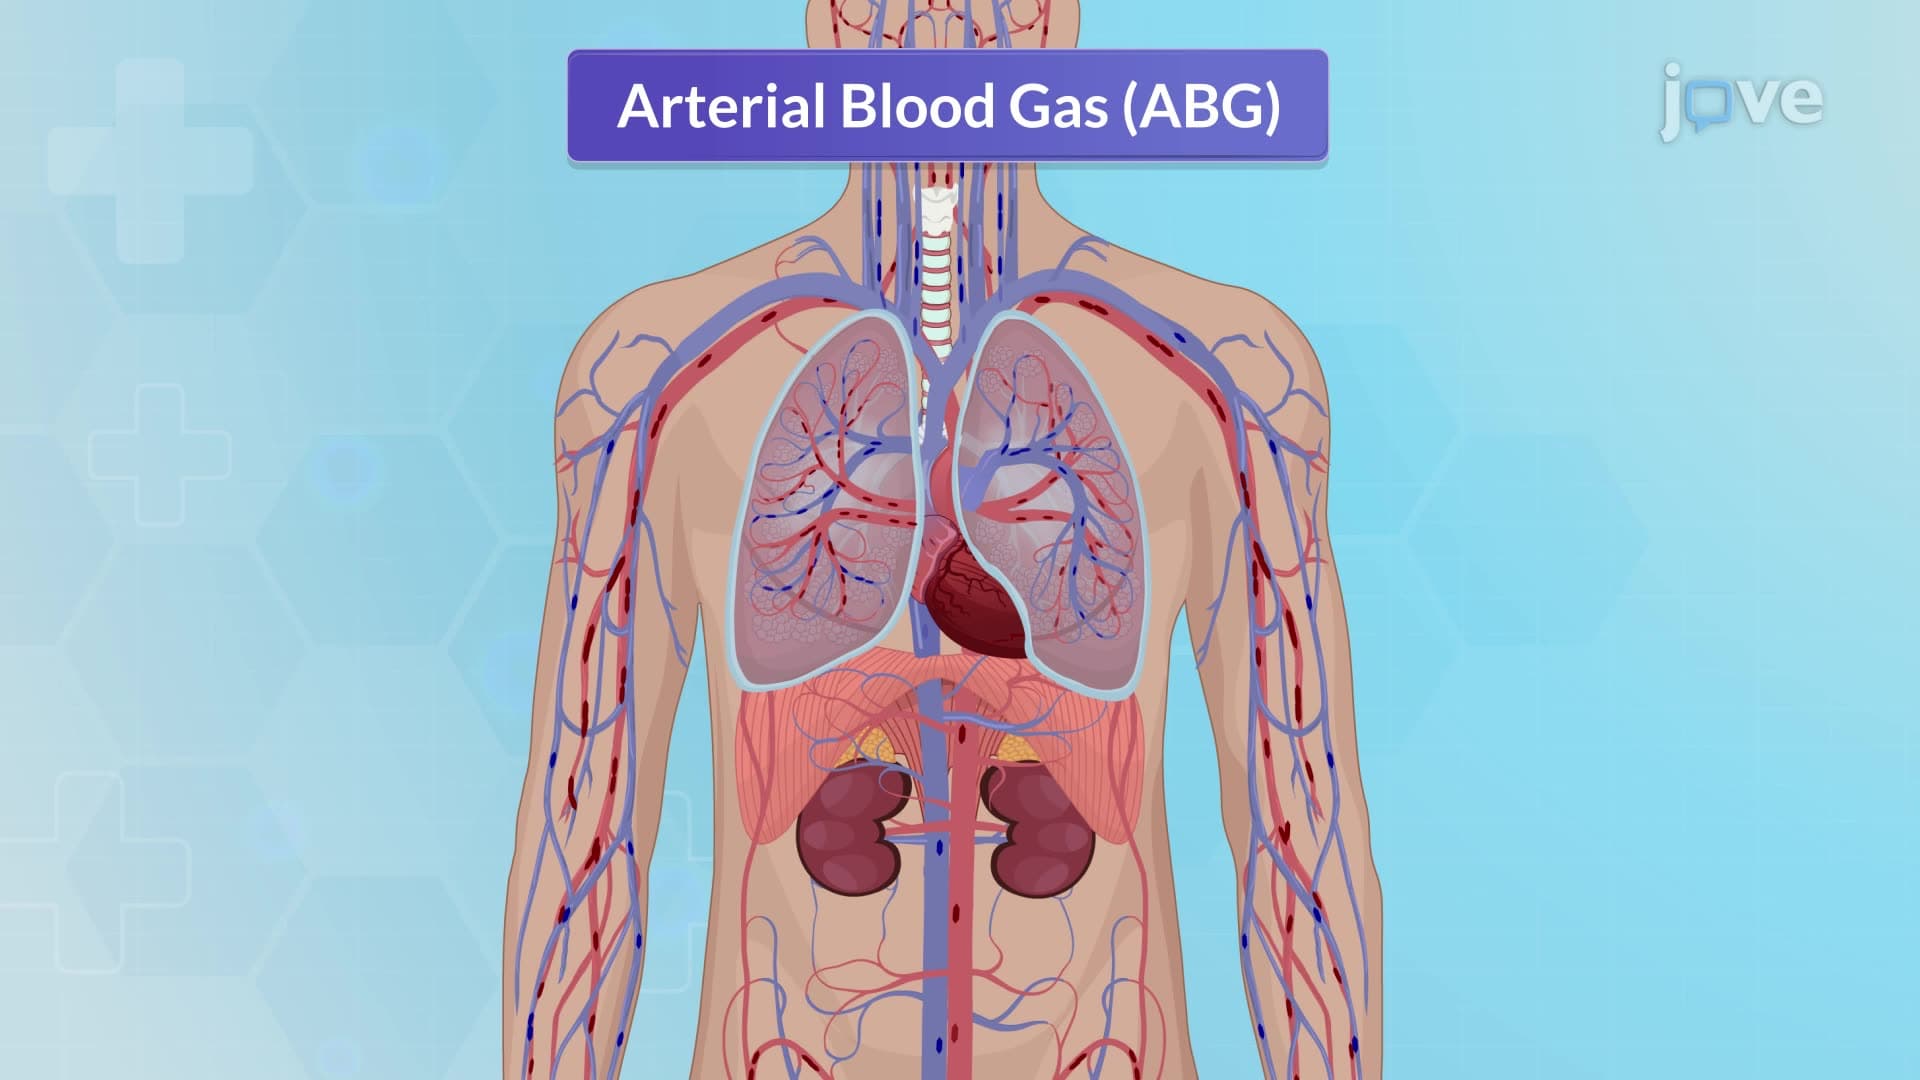
Blood Studies I: ABG and VBG
Arterial Blood Gas (ABG)
Arterial Blood Gas (ABG) studies are crucial for assessing the lungs' ability to supply oxygen and remove carbon dioxide, reflecting the patient's ventilation status. They also help understand the kidneys' capacity to reabsorb or...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies