Related Experiment Video
Updated: Aug 8, 2026
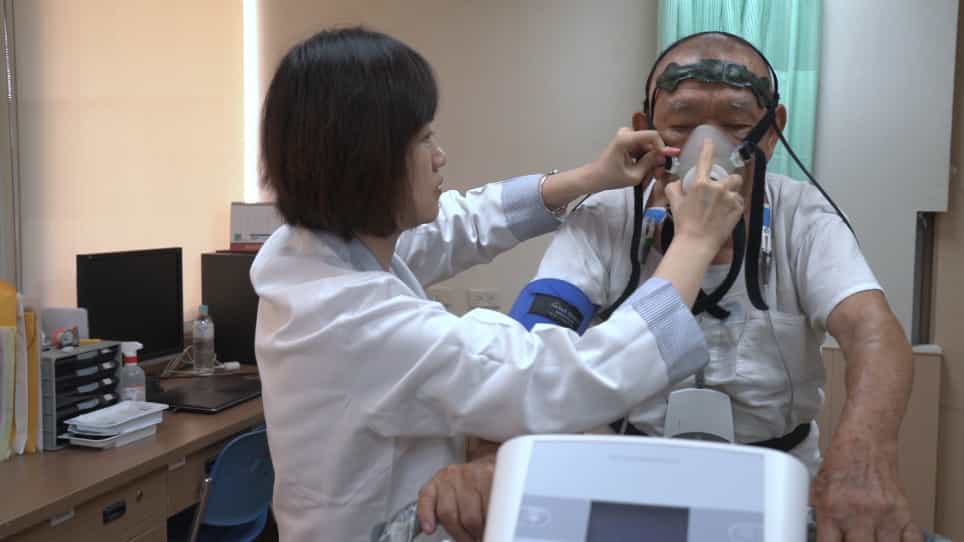
Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Prospective comparison of ventilatory equivalent versus peak oxygen consumption in predicting outcomes of patients
Joshua M Stolker1, Bastiaan Heere, Edward M Geltman
1The Department of Medicine, Division of Cardiology, Washington University School of Medicine, St. Louis, Missouri, USA. jstolker@im.wustl.edu

Abstract:
In patients with heart failure (HF), peak exercise oxygen consumption (VO2) is an important prognostic tool on which critical clinical decisions are made. However, recent retrospective data have suggested that ventilatory equivalent (VE = ventilation [liters per minute]/VO2 [liters per minute]) may be a stronger predictor of outcomes than VO2 in patients with HF on modern medical therapies. We prospectively collected baseline demographics, cardiovascular history, hemodynamics, and exercise ventilatory data from 221 consecutive patients with HF who underwent treadmill exercise VO2 testing. The composite primary end point was death or heart transplantation. Mean follow-up was 508 days, during which 27 events occurred (13 deaths and 14 transplantations). One-year event-free survival was 88% (n = 104 with 1-year follow-up). Mean age was 49 years, 68% were men, 84% were taking beta blockers, 82% were taking angiotensin-converting enzyme inhibitors, and 21% had an implantable cardioverter-defibrillator. Mean VO2 was 16 +/- 5 ml/kg/min. Mean VE was 47.4 +/- 15.2. Univariate predictors of events included lower VO2 (p <0.0001), higher heart rate at rest (p = 0.05), and presence of an implantable cardioverter-defibrillator (p = 0.024). Higher VE (p = 0.10) and lower maximum systolic blood pressure (p = 0.09) were of borderline significance. Age, gender, HF etiology or severity, and other ventilatory parameters were not significant predictors. Multivariate models that incorporated VE, VO2, or their combination confirmed VO2 as an independent predictor of event-free survival (p < or =0.0002); VE did not independently predict outcomes. Other independent predictors were higher heart rate at rest (p < or =0.02) and presence of an implantable cardioverter-defibrillator (p < or =0.04). In conclusion, peak VO2, but not VE, predicts clinical outcomes of patients with HF who are treated with contemporary medical therapies.
More Related Videos
 08:44
Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:22
Respiratory Volumes and Capacities
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:26
Respiratory Volumes and Capacities I
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: