Related Experiment Video
Updated: Aug 8, 2026


Determining Bile Duct Density in the Mouse Liver
Published on: April 30, 2019
Hyperbilirubinemia is not a major contributing factor to altered bone mineral density in patients with chronic liver
Darcey L H Smith1, Norah J Shire, Nelson B Watts
1Division of Digestive Diseases, University of Cincinnati, Cincinnati, OH 45267-0595, USA.

Reduced bone density is commonly encountered in patients with chronic liver disease. Prior studies have shown that unconjugated bilirubin inhibits osteoblast activity and function in vitro and in animal models of bone mineralization. To determine whether hyperbilirubinemia promotes the development of hepatic osteodystrophy, bone mineral density (BMD) was measured by dual energy X-ray absorptiometry in a cohort of 86 consecutive patients with chronic liver disease referred for liver transplant evaluation. The mean age of the study population was 52 years (range, 22-73), in which 52% were female and 90% were white. Average bone density values were significantly lower than expected for age, race, and sex, with Z-scores for the femoral neck and spine of -0.50 (95% confidence interval [CI] -0.63 to -0.37; p=0.0003) and -0.69 (95% CI -0.85 to -0.52; p=0.0001), respectively. Sixty-one subjects (71%) exhibited reduced BMD (T-score of femoral neck or spine
Reduced bone density is commonly encountered in patients with chronic liver disease. Prior studies have shown that unconjugated bilirubin inhibits osteoblast activity and function in vitro and in animal models of bone mineralization. To determine whether hyperbilirubinemia promotes the development of hepatic osteodystrophy, bone mineral density (BMD) was measured by dual energy X-ray absorptiometry in a cohort of 86 consecutive patients with chronic liver disease referred for liver transplant evaluation. The mean age of the study population was 52 years (range, 22-73), in which 52% were female and 90% were white. Average bone density values were significantly lower than expected for age, race, and sex, with Z-scores for the femoral neck and spine of -0.50 (95% confidence interval [CI] -0.63 to -0.37; p=0.0003) and -0.69 (95% CI -0.85 to -0.52; p=0.0001), respectively. Sixty-one subjects (71%) exhibited reduced BMD (T-score of femoral neck or spine


Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:25
Jaundice
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not related to...
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:29
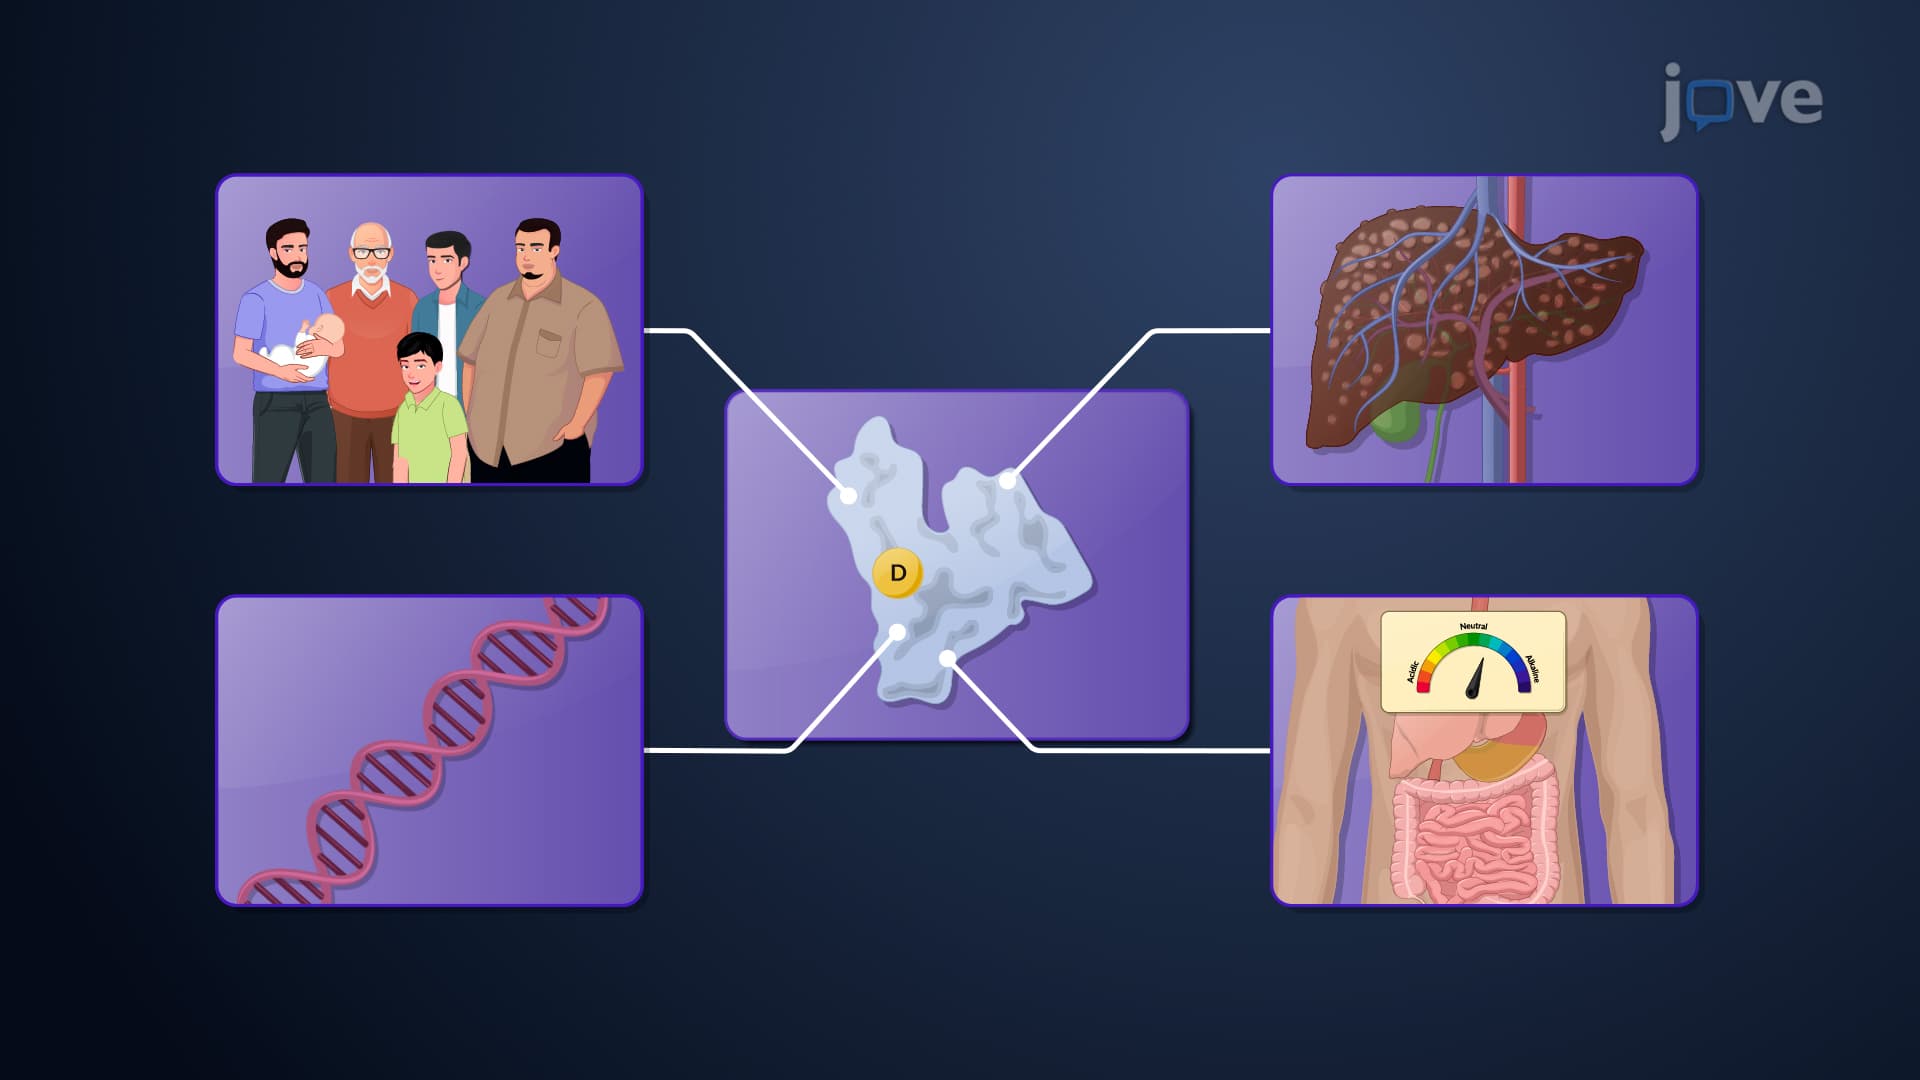
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...