Islet hypertrophy following pancreatic disruption of Smad4 signaling
Related Experiment Video
Updated: Aug 8, 2026

Isolated Pancreatic Islet Treatment and Apoptosis Measurement
Published on: May 2, 2025
Diane M Simeone1, Lizhi Zhang, Mary K Treutelaar
1Department of Surgery, University of Michigan, Ann Arbor, MI 48109, USA.

Abstract:
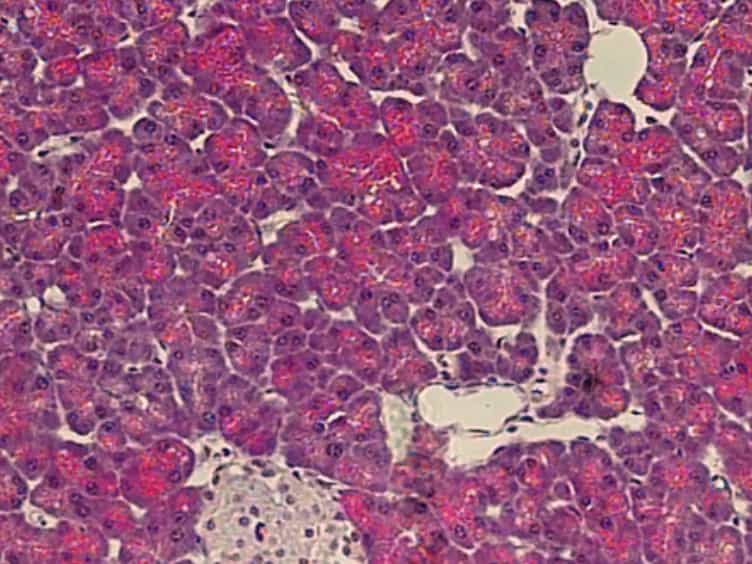
To investigate the role of transforming growth factor (TGF)-beta family signaling in the adult pancreas, a transgenic mouse (E-dnSmad4) was created that expresses a dominant-negative Smad4 protein driven by a fragment of the elastase promoter. Although E-dnSmad4 mice have normal growth, pancreas weight, and pancreatic exocrine and ductal histology, beginning at 4-6 wk of age, E-dnSmad4 mice show an age-dependent increase in the size of islets. In parallel, an expanded population of replicating cells expressing the E-dnSmad4 transgene is found in the stroma between the enlarged islets and pancreatic ducts. Despite the marked enlargement, E-dnSmad4 islets contain normal ratios and spatial organization of endocrine cell subtypes and have normal glucose homeostasis. Replication of cells derived from primary duct cultures of wild-type mice, but not E-dnSmad4 mice, was inhibited by the addition of TGF-beta family proteins, demonstrating a cell-autonomous effect of the transgene. These data show that, in the adult pancreas, TGF-beta family signaling plays a role in islet size by regulating the growth of a pluripotent progenitor cell residing in the periductal stroma of the pancreas.
More Related Videos
 07:44
Surgical Injury to the Mouse Pancreas through Ligation of the Pancreatic Duct as a Model for Endocrine and Exocrine Reprogramming and Proliferation
Published on: August 7, 2015
 06:57
Intramuscular Transplantation of Human Pluripotent Stem Cell-derived Pancreatic Endocrine Cells in Mice
Published on: April 10, 2026
Related Concept Videos
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:21
Acute Pancreatitis II: Pathophysiology