Related Experiment Video
Updated: Aug 8, 2026


Establishment of Rat Models Mimicking Gender-affirming Hormone Therapies
Published on: January 10, 2025
[Influence of ACTH-depot doses on neuroendocrine gestosis treatment]
Marek Klimek1, Beata Tomaszewska
1Klinika Ginekologii i Niepłodności CMUJ, Kraków.

Objective Of The Study:
Two dosing methods of ACTH-depot therapy were compared dependently on gestational age and sequence of applied injections. It has been concluded that better efficacy was observed in single doses method comparing to serial doses in 2nd trimester.
Material And Methods:
Retrospectively, 380 pregnancies were analyzed, in which ACTH-depot therapy was applied using 0,5 mg doses. In 140 subjects (Group I, 1990-1991) 3 injection series every 2nd day with additional antibiotic (i.e. Monural 3g) were administrated. In the rest 240 (Group II, 1997-2002) single doses were applied during the whole period of pregnancy due to recurrent vomiting or decreased CAP1 serum levels under 0,8 micromol/l/min and CAP2 under 1,4 micromol/l/min in 1st trimester and compulsory in ACTH serum levels under 5,0 pg/ml.
Results:
Clinical results can be compared with oxytocinase and ACTH serum levels, what allows to understand enzymatic control of internal maternal state. Role of ACTH not only in lung maturation, but also in onset of labor was proved in the mechanism of influence on immunologic tolerance. In hormonal threatening pregnancies enzymatic component is less helpful in predicting birth date because of common irregular oxitocinase pattern in such patients. On the other hand constant enzymatic increase proves effectiveness of ACTH-depot therapy in neurendocrine-gestoses, or in insulin-requiring pregnant patients.
Conclusions:
Acquired results of neonatal state proved that: 1. in pregnancies after infertility treatment early application of substitutional hormonotherapy wsith single doses of 0,5 mg ACTH-depot in early gestational weeks is more efficient method of ACTH dosing than 3 injections method in 2nd trimester 2. serum prelabour oxitocinase levels were precise factors of clinical results.


Related Concept Videos
 01:19
Cushing Syndrome II: Pathophysiology
 01:26
Cushing Syndrome I: Introduction
 01:30
Indirect-Acting Cholinergic Agonists: Pharmacological Actions
At the neuromuscular junction, these agents work by inhibiting the breakdown of acetylcholine, allowing it to remain bound to the receptor and bind to nearby receptors. This process leads to repetitive firing of the endplate, causing muscle...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:21
Drugs for Treatment of Crohn's Disease in IBD Using Glucocorticoids
 01:29
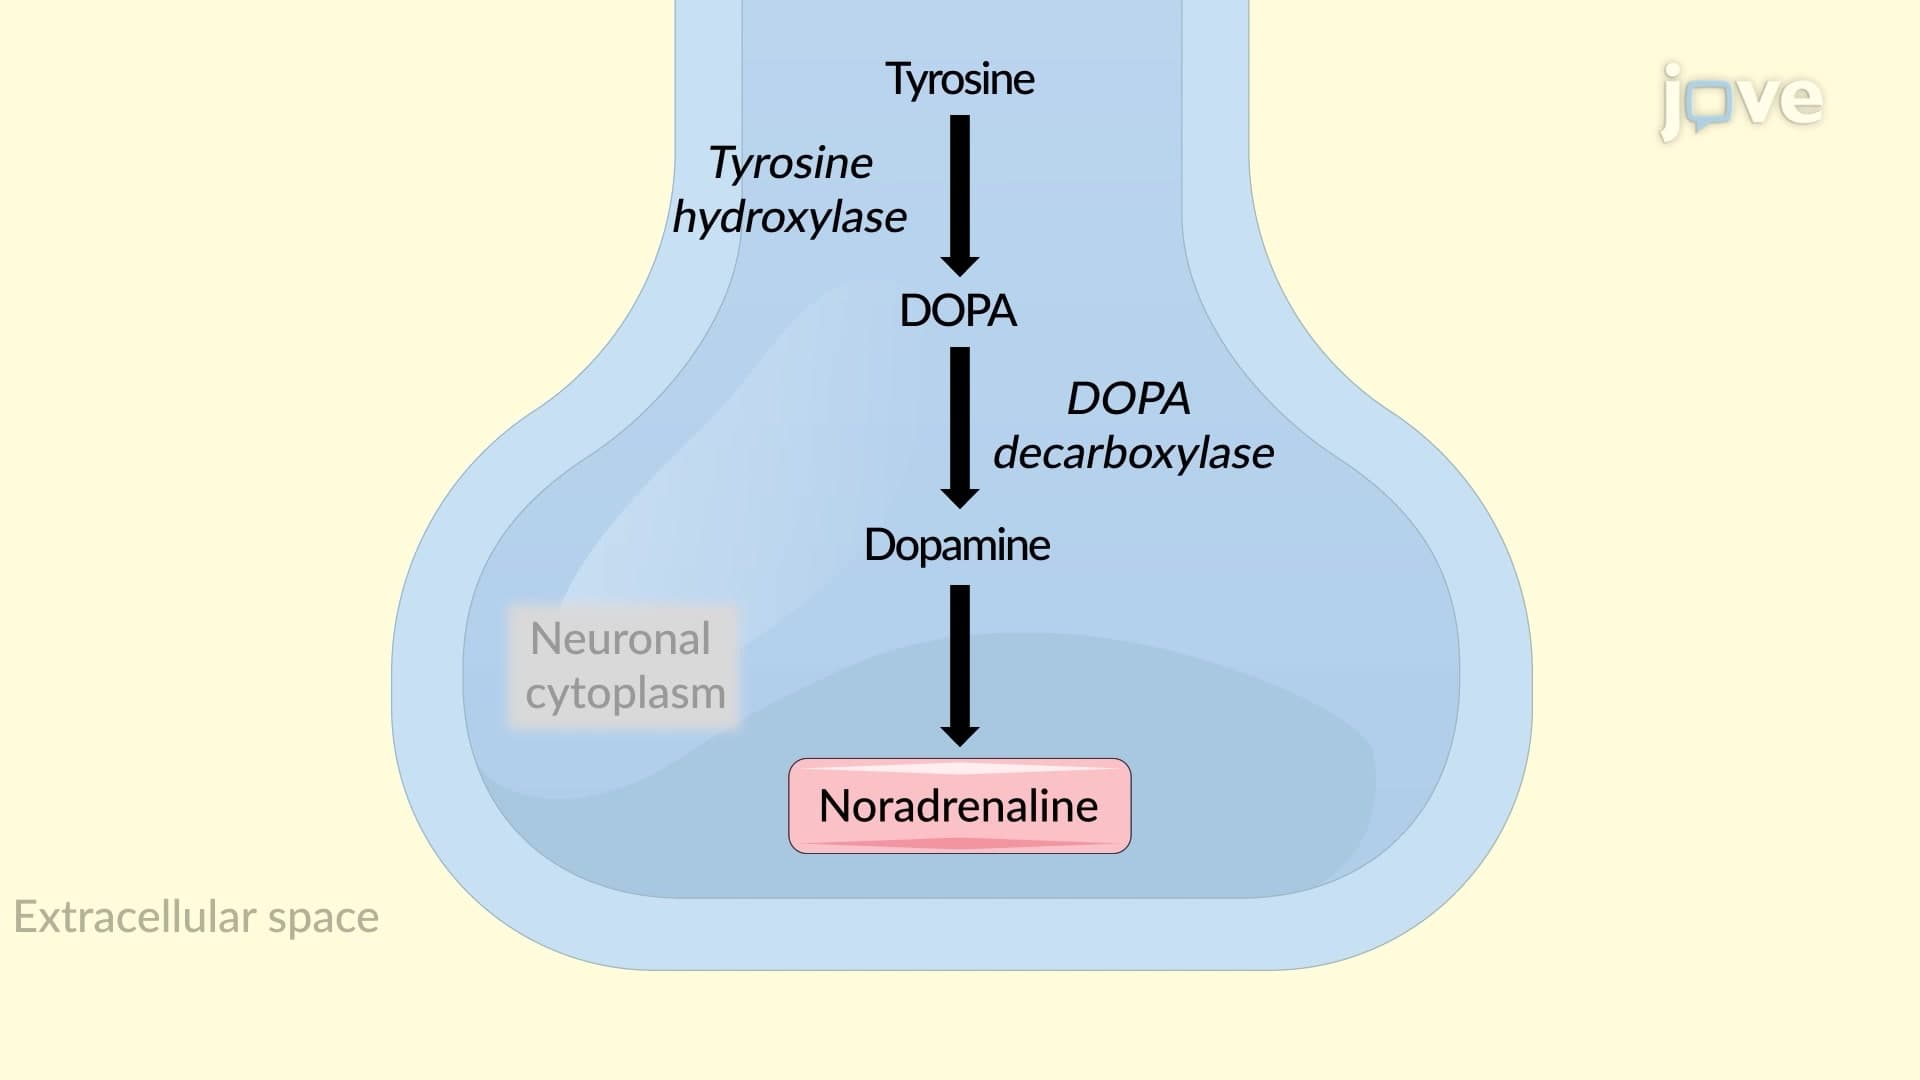
Drugs Affecting Neurotransmitter Synthesis