Related Experiment Video
Updated: Aug 8, 2026
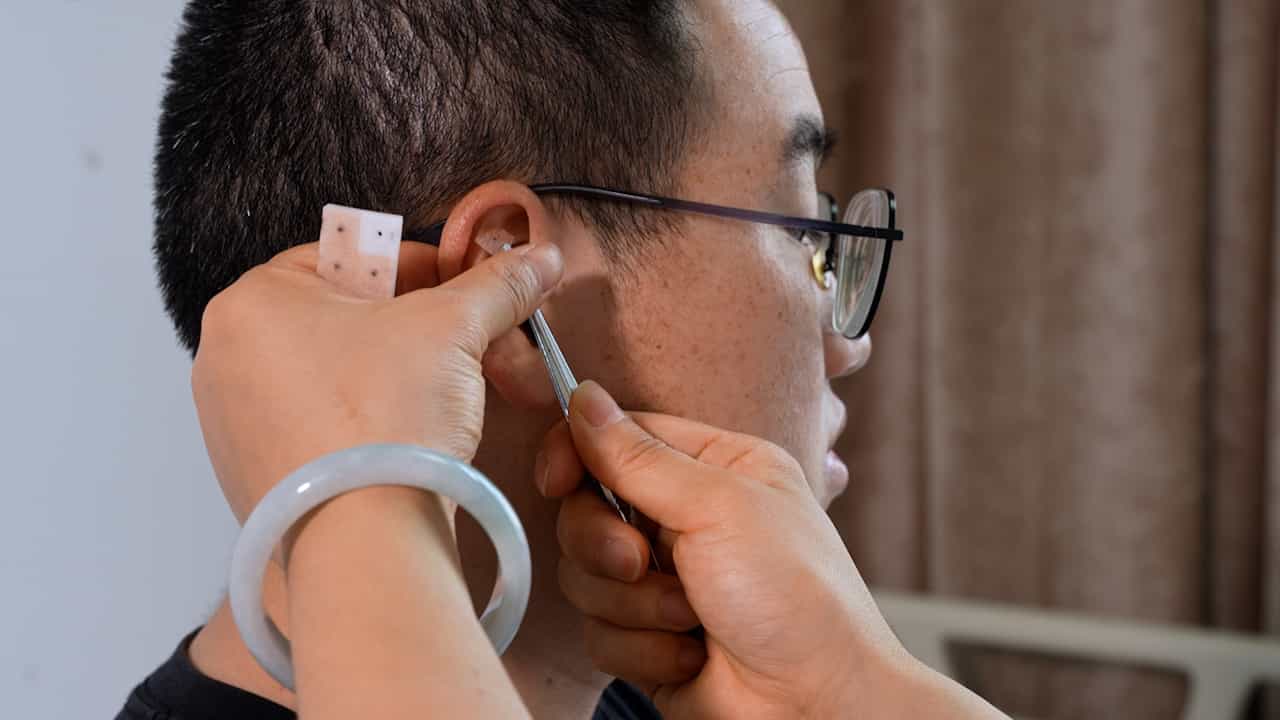
Auricular Acupressure as an Adjuvant Treatment for Wheezing in Stable Chronic Obstructive Pulmonary Disease
Published on: May 10, 2024
Antibiotic treatment of wheezing in children with asthma: what is the practice?
Anita L Kozyrskyj1, Matthew E Dahl, Wendy J Ungar
1Faculty of Pharmacy, University of Manitoba, Winnipeg, Manitoba, Canada. Kozyrsk@cc.umanitoba.ca

Insights
Antibiotic prescriptions for childhood wheezing decreased overall, but broader-spectrum macrolide use surged, raising antibiotic resistance concerns. Physician factors influenced prescribing habits, indicating areas for targeted interventions in asthma care.
Area of Science:
- Pediatric Pulmonology
- Infectious Diseases
- Health Services Research
Background:
- Antibiotics are generally not recommended for treating wheezing in children with asthma.
- Limited data exists on current antibiotic prescribing trends for this patient population.
Purpose of the Study:
- To evaluate trends in antibiotic use for wheezing episodes in children with asthma.
- To identify determinants of antibiotic prescription for childhood wheezing.
Main Methods:
- Descriptive study utilizing population-based health care and prescription databases in Manitoba, Canada (1995-2001).
- Examined time trends in antibiotic prescription rates for wheezing episodes.
- Analyzed child and physician characteristics influencing antibiotic prescription likelihood using general estimating equations and hierarchical linear modeling.
Main Results:
- Antibiotic prescription rates for wheezing decreased by 28% between 1995 and 2001.
- Broader-spectrum macrolide use increased fifteen-fold in preschool children.
- General practitioners and physicians trained outside Canada/US were more likely to prescribe antibiotics.
Conclusions:
- While overall antibiotic use for wheezing declined, increased macrolide use poses risks for antibiotic resistance.
- Physician specialty and training location are linked to prescribing patterns, highlighting potential intervention points.
Objective:
Antibiotics are not recommended for the treatment of wheezing in children with asthma, but little is known about their use. This study was undertaken to evaluate trends and determinants of antibiotic use in children with wheezing during the fiscal years 1995 through 2001.
Methods:
Using the population-based health care and prescription databases in Manitoba, Canada, this descriptive study examined time trends in antibiotic prescription use for wheezing episodes in a population of children with asthma. The likelihood of receiving an antibiotic prescription according to child and physician characteristics also was determined. Annual population-based rates of antibiotic prescriptions for wheezing episodes were modeled by age and antibiotic class, using general estimating equations. The odds ratio for receiving an antibiotic prescription according to child demographics and physician factors was determined from hierarchical linear modeling.
Results:
The antibiotic prescription rate for wheezing decreased by 28% from 708 prescriptions per 1000 children with asthma in 1995 to 511 prescriptions in 2001. Fifteen-fold increases in use were observed for broader spectrum macrolides in preschool children. Twenty-three percent of physician visits for wheezing resulted in an immediate antibiotic prescription, but this percentage increased to 64% for antibiotics that were received within 7 days of the episode. General practitioners prescribed antibiotics more often than did pediatricians. Physicians who were not trained in Canada or the United States were 40% more likely to prescribe antibiotics than their counterparts.
Conclusions:
Antibiotic use for wheezing in children declined in the 1990s, but the increased use of broader spectrum macrolides has implications for antibiotic resistance. A link between antibiotic prescribing and physician specialty and location of training identifies opportunities for intervention.

Related Concept Videos
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:28
Asthma I: Introduction
 01:30
Asthma-IV: Nursing Management
First, in...