Related Experiment Video
Updated: Aug 8, 2026
Management of the Uncinate Process in No-Touch Laparoscopic Pancreaticoduodenectomy
Published on: May 5, 2023
[What are the main errors made by surgeons in the management of pancreatic cancer?]
Juan Angel Fernández1, Pascual Parrilla
1Servicio de Cirugía General y Digestiva I, Hospital Universitario Virgen de la Arrixaca, Murcia, Spain. jumanjico@yahoo.com

Abstract:
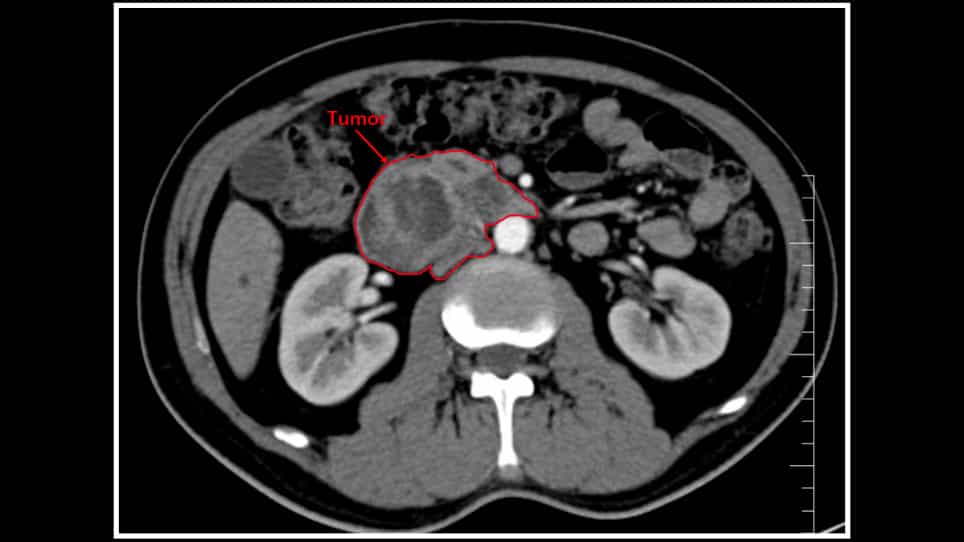
The present review identifies two major conceptual errors. Therapeutic nihilism, which should be discounted in view of the results currently achieved by surgery, and noncentralization, since better results have been demonstrated, both in terms of morbidity and mortality and in survival, in high-volume centers than in low volume centers. The present review also identifies errors in management, the most important of which are: undervaluing the medical record, which is of great utility and continues to be the pillar on which the entire diagnostic process is based; the systematic use of preoperative biliary drainage, which used to be considered mandatory but should be used highly selectively in patients with severe jaundice or biliary tract infections, and viewing preoperative imaging tests as unreliable, when current radiological techniques, particularly helical computed tomography (CT), are highly reliable in establishing tumor resectability and consequently they should be used in all treatment planning. Moreover, because radiological tests are highly reliable, laparoscopic staging has lost diagnostic value; obtaining a preoperative histological diagnosis, which is not mandatory except when neoadjuvant therapy is planned or when tumors requiring nonsurgical treatment are suspected; undervaluing the use of surgical palliation, since this technique provides better long-term results than nonsurgical palliation, and consequently still plays a role in patients with good general health status and prolonged life expectancy; systematically performing gastrojejunostomy with bilio-enteric bypass, as this procedure should only be performed in tumors of the uncus or when there is imminent biliary or gastroduodenal obstruction; the use of supraradical surgical techniques such as regional, total or extensive pancreatectomy, since these techniques do not prolong survival after resection. Furthermore, the use of vascular resections would only be justified if resection with disease-free margins could be performed; undervaluing close postoperative monitoring within specialized units since this is the key to reducing morbidity and mortality rates in this type of surgery; and lastly when an intraoperative pancreatic incidentaloma is present, performing diagnostic maneuvers such as biopsy or pancreatic mobilization, since these procedures hamper subsequent radiological interpretation and possible surgical intervention.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management