Related Experiment Video
Updated: Aug 7, 2026
Receptor Autoradiography Protocol for the Localized Visualization of Angiotensin II Receptors
Published on: June 7, 2016
Centrally administered interleukin-1 beta sensitizes to the central pressor action of angiotensin II
Marcin Ufnal1, Magdalena Dudek, Tymoteusz Zera
1Department of Experimental and Clinical Physiology, Medical University of Warsaw, 00-927 Warsaw, Krakowskie Przedmieście 26/28, Poland. marcinufnal@poczta.onet.pl

The objective of the present study was to find out whether brain vasopressin (AVP) and angiotensin II (Ang II) are involved in pressor response to intracerebroventricular (ICV) infusion of interleukin-1 beta (IL-1beta). The experiments were performed on conscious, 12- to 14-week-old Sprague-Dawley rats. Mean arterial blood pressure (MAP) and heart rate (HR) were recorded continuously under baseline conditions and during ICV infusion periods. In the first part of the study, the rats were ICV-infused with one of the following: 0.9% NaCl saline (5 microl/h-control), IL-1beta (100 ng/h), angiotensin AT1 receptor antagonist (losartan 10 microg/h), IL-1beta together with losartan, V1 receptors antagonist (V1ANT), d(CH2)5[Tyr(Me)2,Ala-NH2(9)]AVP, 400 ng/h) or IL-1beta together with V1ANT. Saline infusion did not influence MAP, while administration of IL-1beta elicited a significant but transient increase in MAP. The pressor response to IL-1beta was abolished by losartan but not by V1ANT. On the other hand, combined administration of IL-1beta and V1ANT resulted in increase in HR, which was absent during infusion of IL-1beta alone. In the second part of the study after ICV pretreatment with IL-1beta or 0.9% NaCl (control), the rats received ICV infusion of one of the following: 0.9% NaCl saline, subpressor dose of Ang II (5 ng/15 s) or subpressor dose of AVP (5 ng/15 s). Subpressor doses of Ang II and AVP did not influence MAP and HR in saline-pretreated rats. The same dose of Ang II but not AVP applied in IL-1beta-pretreated rats resulted in a significant increase in MAP. The study provides evidence that IL-1beta through its action in the brain increases sensitivity to central pressor action of Ang II. Additionally, we found that AVP and in particular V1 receptors do not play important role in the central pressor action of IL-1beta, however, they may influence its effect on HR regulation.
The objective of the present study was to find out whether brain vasopressin (AVP) and angiotensin II (Ang II) are involved in pressor response to intracerebroventricular (ICV) infusion of interleukin-1 beta (IL-1beta). The experiments were performed on conscious, 12- to 14-week-old Sprague-Dawley rats. Mean arterial blood pressure (MAP) and heart rate (HR) were recorded continuously under baseline conditions and during ICV infusion periods. In the first part of the study, the rats were ICV-infused with one of the following: 0.9% NaCl saline (5 microl/h-control), IL-1beta (100 ng/h), angiotensin AT1 receptor antagonist (losartan 10 microg/h), IL-1beta together with losartan, V1 receptors antagonist (V1ANT), d(CH2)5[Tyr(Me)2,Ala-NH2(9)]AVP, 400 ng/h) or IL-1beta together with V1ANT. Saline infusion did not influence MAP, while administration of IL-1beta elicited a significant but transient increase in MAP. The pressor response to IL-1beta was abolished by losartan but not by V1ANT. On the other hand, combined administration of IL-1beta and V1ANT resulted in increase in HR, which was absent during infusion of IL-1beta alone. In the second part of the study after ICV pretreatment with IL-1beta or 0.9% NaCl (control), the rats received ICV infusion of one of the following: 0.9% NaCl saline, subpressor dose of Ang II (5 ng/15 s) or subpressor dose of AVP (5 ng/15 s). Subpressor doses of Ang II and AVP did not influence MAP and HR in saline-pretreated rats. The same dose of Ang II but not AVP applied in IL-1beta-pretreated rats resulted in a significant increase in MAP. The study provides evidence that IL-1beta through its action in the brain increases sensitivity to central pressor action of Ang II. Additionally, we found that AVP and in particular V1 receptors do not play important role in the central pressor action of IL-1beta, however, they may influence its effect on HR regulation.
Related Concept Videos
 01:30
Antihypertensive Drugs: Angiotensin II Receptor Blockers
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:26
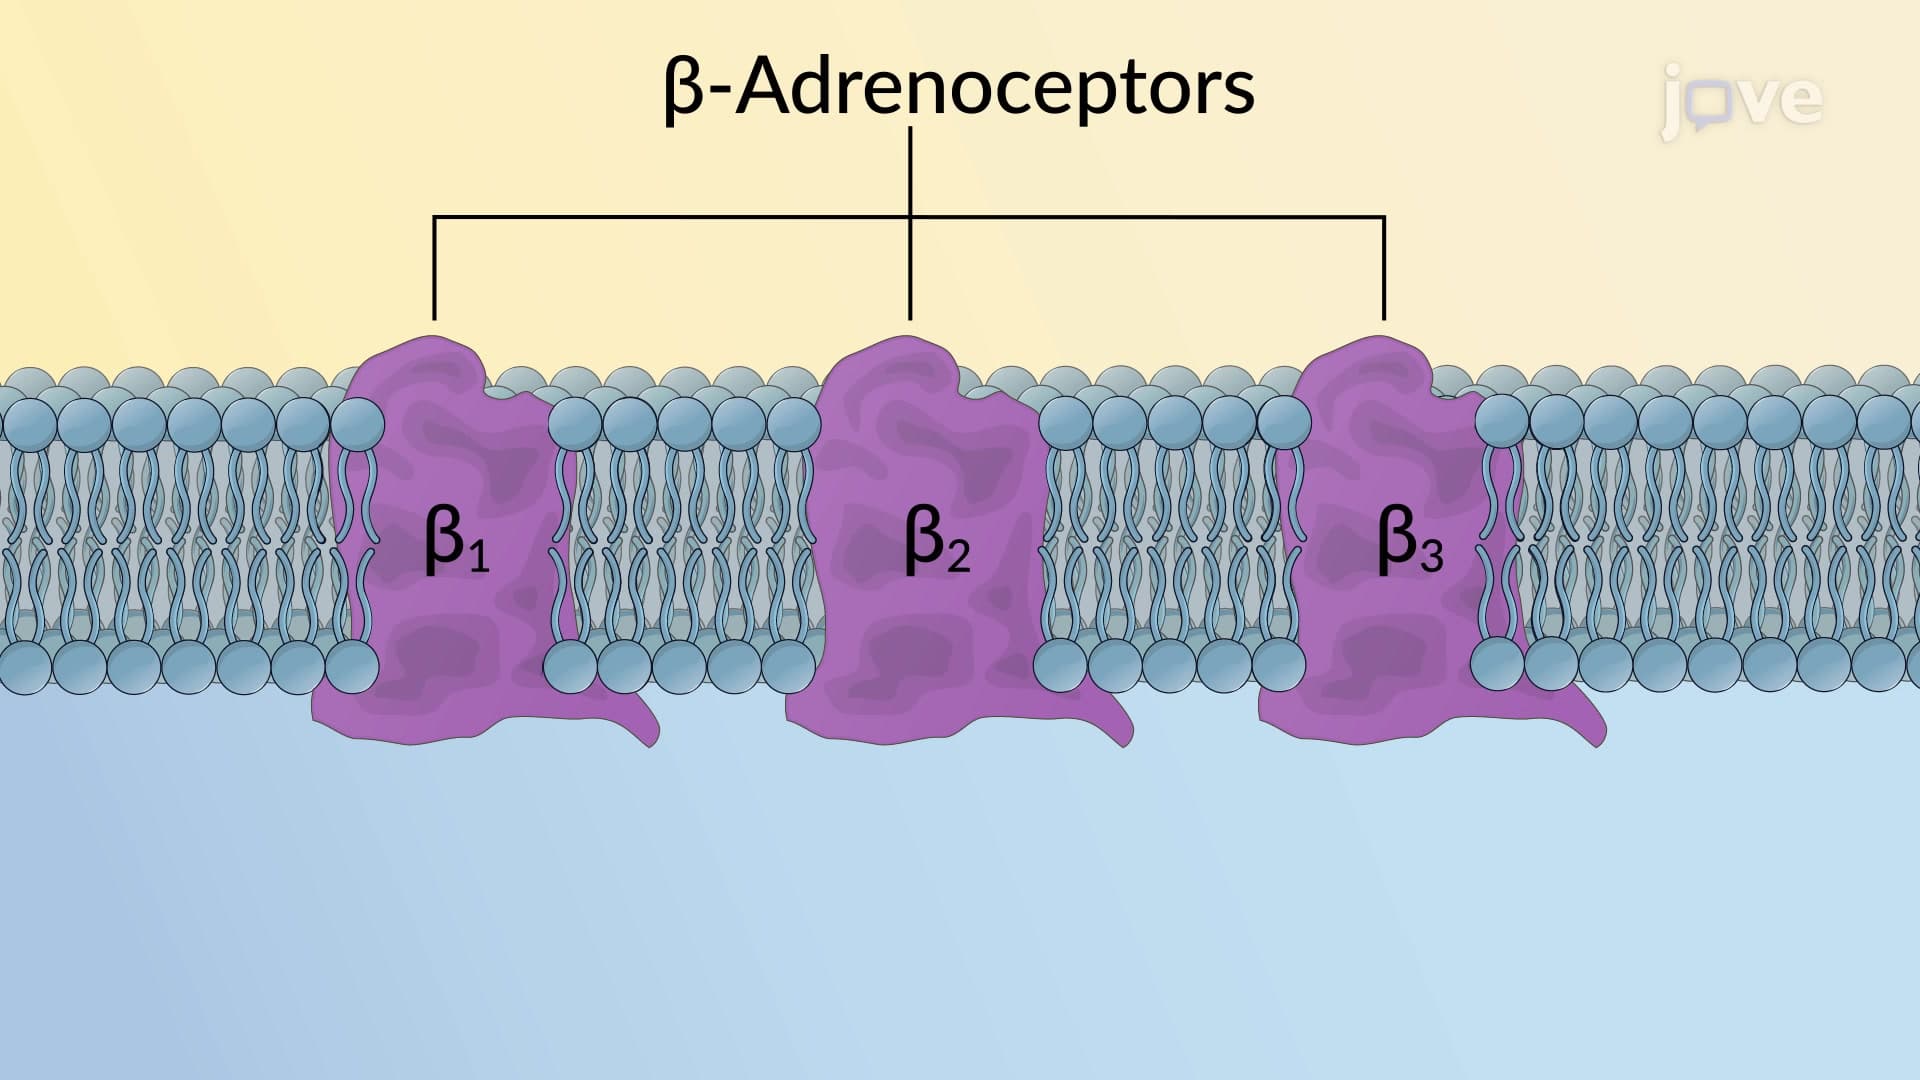
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:29
Heart Failure II: Pathophysiology