Related Experiment Video
Updated: Aug 6, 2026

Assessing Changes in Volatile General Anesthetic Sensitivity of Mice after Local or Systemic Pharmacological Intervention
Published on: October 17, 2013
Pharmacokinetic/pharmacodynamic modeling of anesthetics in children: therapeutic implications
1Département d'Anesthésie-Réanimation, AP-HP, Université Paris-Sud, Hôpital Bicêtre, Le Kremlin-Bicêtre, France. Jean-Xavier.Mazoit@kb.u-psud.fr

Abstract:
Modeling the pharmacokinetics and pharmacodynamics of anesthetics in children is performed as a response to the clinical need for safe and efficacious administration of drugs with a low therapeutic index. Rates and concentrations of these drugs, which are the primary parameters used by anesthesiologists, depend on physiologic parameters that are markedly affected by development. Volatile anesthetics have been used for >50 years in pediatric patients. The pharmacokinetics of inhalation agents are context sensitive, but little difference between age groups has been described. These agents are not only eliminated unchanged by the lung but they are also metabolized by the liver. Halothane has Michaelis-Menten kinetics, with up to 40% of the administered dose metabolized by the liver. For volatile anesthetics, the effect measured is the minimum alveolar concentration (MAC) that leads to movement of the limb in response to skin incision in 50% of the patients studied. The MAC is higher in infants than in children and adults. Infants aged 6 months have a MAC 1.5-1.8 times the MAC observed in adults aged 40 years. Children have a greater clearance and volume of distribution of propofol than adults. In order to achieve similar plasma concentrations, children require three times the initial dose used in adults. In adults, an increased sensitivity to propofol has been demonstrated with aging, but nothing is known about the effects in children. However, it is clear that equipotent doses of propofol induce marked deleterious hemodynamic effects in infants compared with children. Regional anesthesia is used in pediatrics, both in combination with general anesthesia during surgery or alone for postoperative analgesia. A marked decrease in protein binding has been described in infants. In the postoperative period, a rapid increase in binding because of inflammation decreases the free fraction, but the free drug concentration remains constant because of the resulting decrease in total clearance. A low clearance because of liver function immaturity has been observed during the first year(s) of life for bupivacaine and ropivacaine. Pharmacodynamic interactions between general anesthesia and regional anesthesia need to be modeled. This is one of the future tasks for pharmacokineticists. Methods such as the Dixon up-and-down allocation and the isobolographic technique are promising in this field.
More Related Videos
 06:38
Use of a Piglet Model for the Study of Anesthetic-induced Developmental Neurotoxicity (AIDN): A Translational Neuroscience Approach
Published on: June 11, 2017
 08:23
Adaptation of Microelectrode Array Technology for the Study of Anesthesia-induced Neurotoxicity in the Intact Piglet Brain
Published on: May 12, 2018
Related Concept Videos
 01:24
Parenteral Anesthetics: Overview
 01:20
Pharmacokinetic Models: Overview
There are three primary types of models: empirical, compartment, and physiological. Empirical models, with minimal assumptions,...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:29
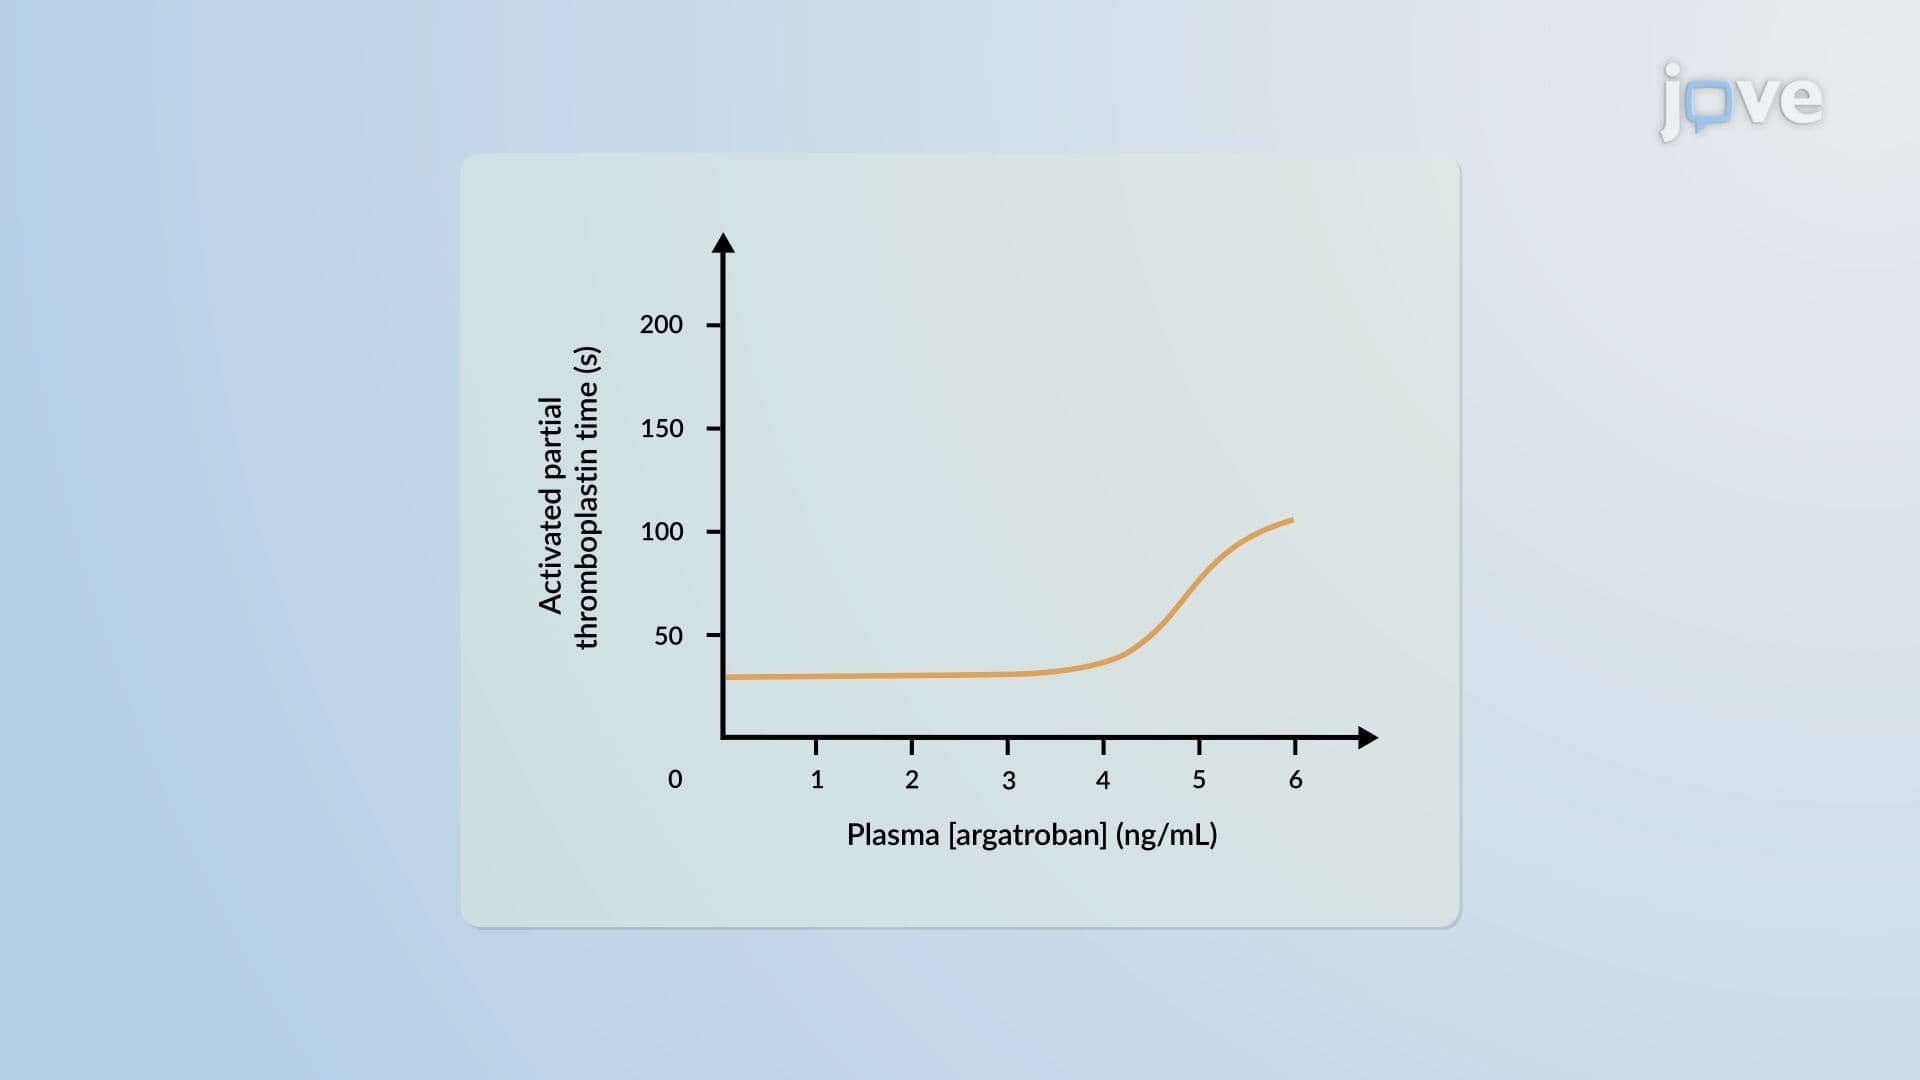
Pharmacodynamic Models: Direct Effect Model and Indirect Response Model
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions