Related Experiment Video
Updated: Aug 1, 2026


Electrophysiology on Isolated Brainstem-spinal Cord Preparations from Newborn Rodents Allows Neural Respiratory Network Output Recording
Published on: November 19, 2015
Maturational changes in the rhythms, patterning, and coordination of respiration and swallow during feeding in
1Division of Neonatology, Department of Pediatrics and Human Development, Michigan State University College of Human Medicine, East Lansing, MI 48912, USA. gewolb@msu.edu

Insights
The coordination of breathing and swallowing improves with infant postmenstrual age (PMA). This improved coordination, particularly reduced apneic swallows, begins after 36 weeks
Area of Science:
- Neonatal Physiology
- Developmental Neuroscience
- Pediatric Respiration and Swallowing
Background:
- Feeding coordination in infants involves complex integration of suck, swallow, and respiration.
- Previous research indicates stabilization of suck and suck-swallow rhythms around 36 weeks postmenstrual age (PMA).
- The developmental trajectory of respiration-swallow coordination requires further elucidation.
Purpose of the Study:
- To investigate the coordination between respiration and swallowing rhythms in preterm and term infants.
- To determine how this coordination evolves with increasing postmenstrual age (PMA).
- To assess the predictive value of swallow-respiration coordination for infant development.
Main Methods:
- Feeding episodes were assessed in preterm and term infants using pharyngeal pressure transducers for swallows and thoracoabdominal strain gauges for respiratory efforts.
- Analysis included coefficients of variation (COVs) of breath-breath and swallow-breath intervals, percentage of apneic swallows, and respiratory phase relative to swallowing.
- Infants were categorized by postmenstrual age (PMA), including preterm infants (< or =35 weeks PMA and >35 weeks PMA) and term infants (1-4 days and 1 month).
Main Results:
- The percentage of apneic swallows significantly decreased with increasing PMA (p<0.001).
- Term infants exhibited significantly lower breath-breath interval variability (BR-BR COV) compared to preterm infants.
- Swallow-respiration phase relation stabilized with increasing PMA, showing decreased apnea and more swallows at end-inspiration.
Conclusions:
- Improvement in respiration-swallow coordination emerges later than suck-swallow rhythm stabilization, beginning after approximately 36 weeks' PMA.
- Enhanced coordination is characterized by fewer apneic swallows and a stable respiratory phase during swallowing.
- The coordination of swallow-respiration and suck-swallow rhythms may serve as a predictor for feeding, respiratory, and neurodevelopmental outcomes.
Abstract:
To study the coordination of respiration and swallow rhythms we assessed feeding episodes in 20 preterm infants (gestational age range at birth 26-33wks; postmenstrual age [PMA] range when studied 32-40wks) and 16 term infants studied on days 1 to 4 (PMA range 37-41wks) and at 1 month (PMA range 41-45wks). A pharyngeal pressure transducer documented swallows and a thoracoabdominal strain gauge recorded respiratory efforts. Coefficients of variation (COVs) of breath-breath (BR-BR) and swallow-breath (SW-BR) intervals during swallow runs, percentage of apneic swallows (at least three swallows without interposed breaths), and phase of respiration relative to swallowing efforts were analyzed. Percentage of apneic swallows decreased with increasing PMA (16.6% [SE 4.7] in preterm infants


Related Concept Videos
 01:26
Respiratory Volumes and Capacities I
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...
 01:18
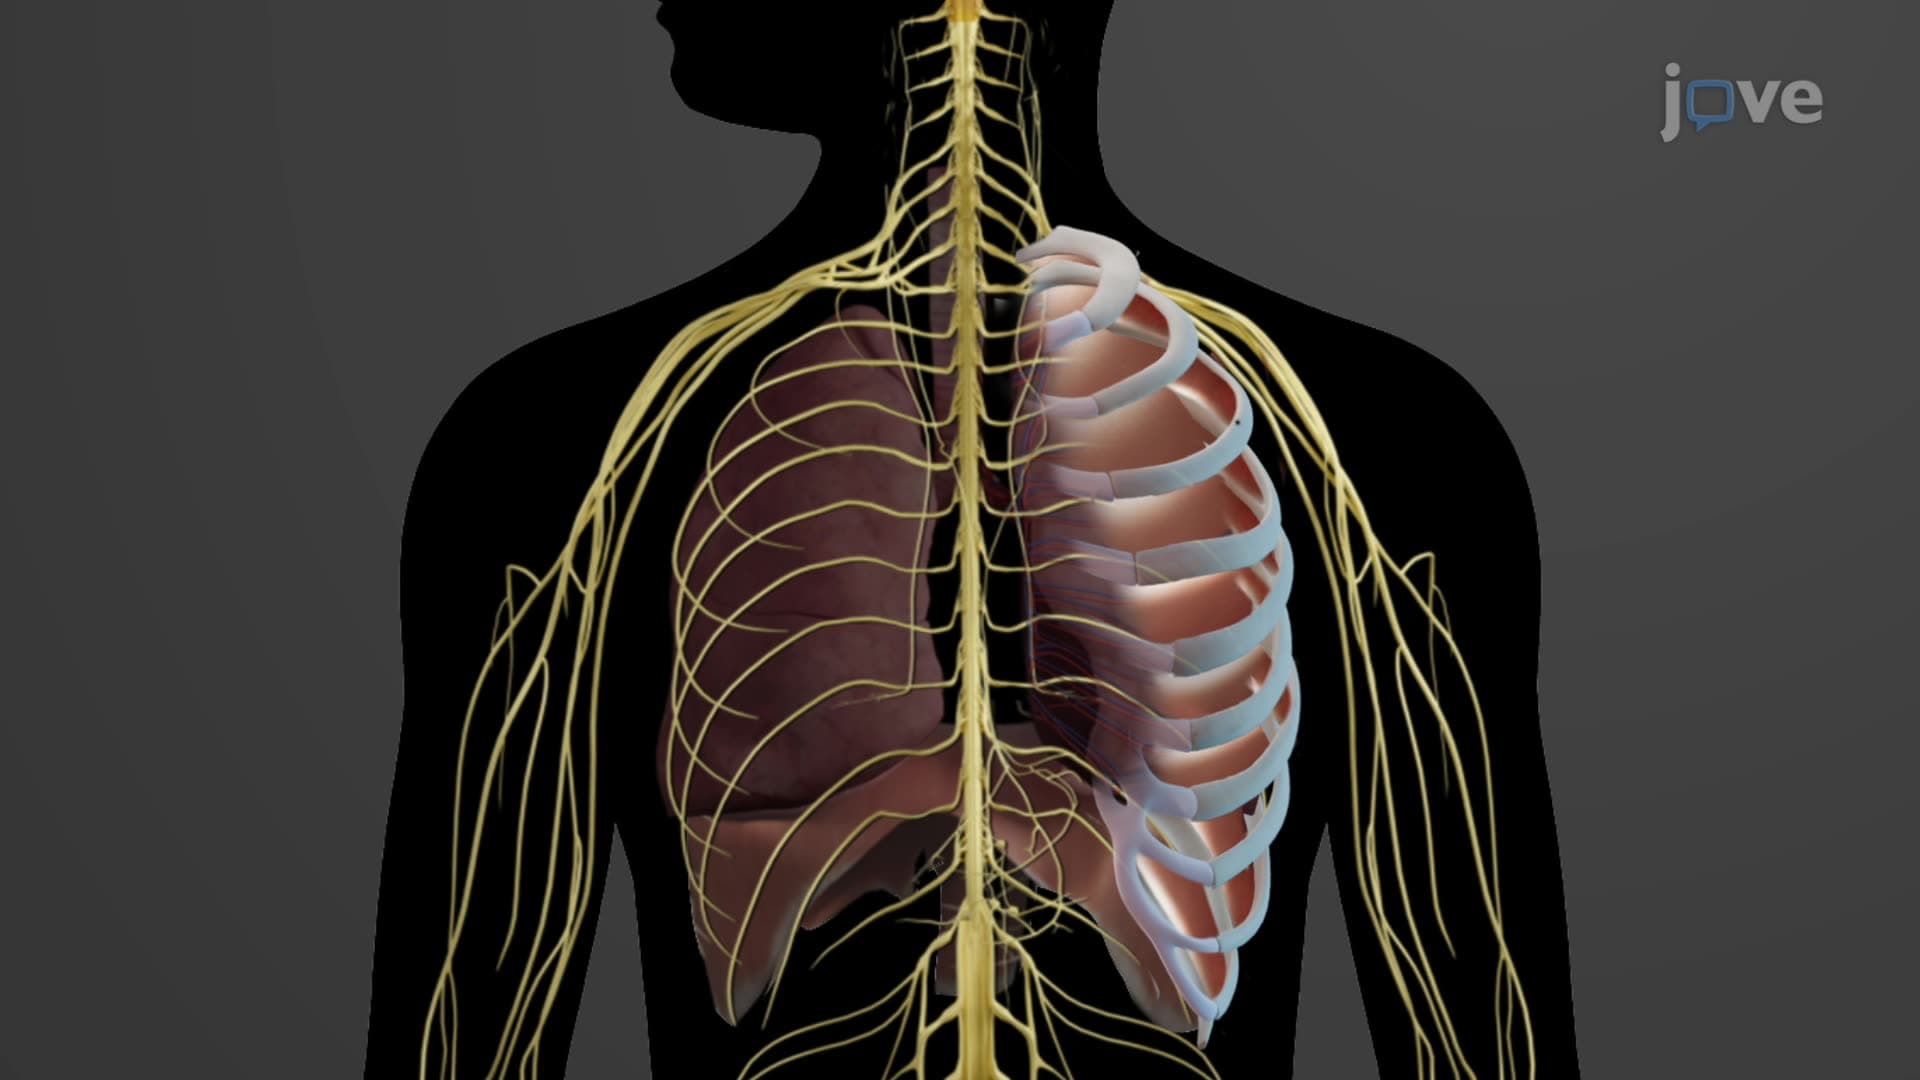
Neural Control of Respiration
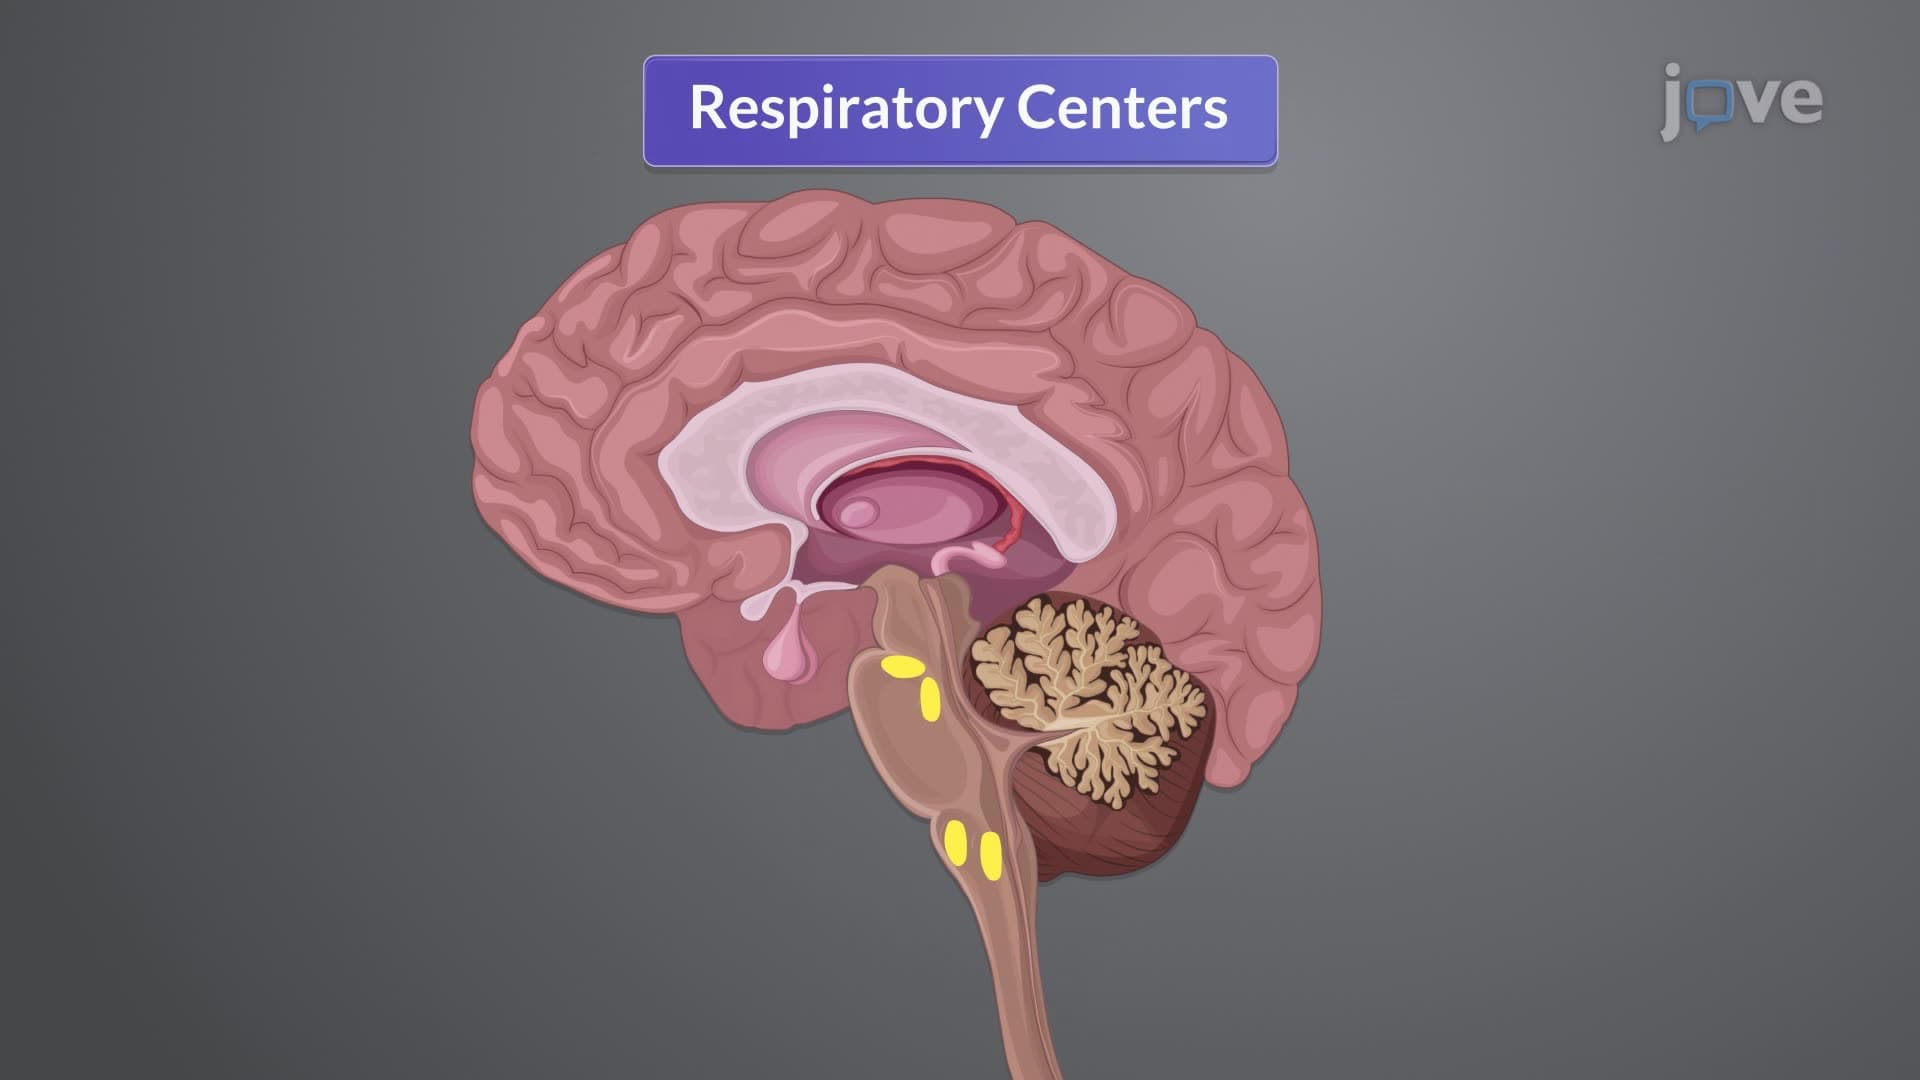
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:17
Other Factors Affecting Respiration Centers
However, the ability to hold one's breath voluntarily is not limitless. When the CO2 concentration in the blood reaches a critical level,...
 01:22
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers: