Related Experiment Video
Updated: Aug 7, 2026
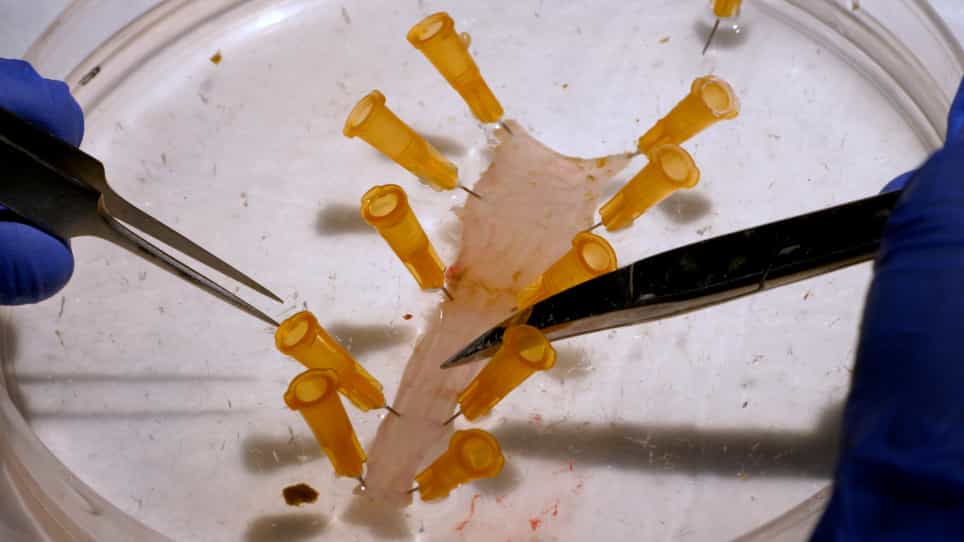

A TNBS-Induced Rodent Model to Study the Pathogenic Role of Mechanical Stress in Crohn's Disease
Published on: March 1, 2022
Skeletal morbidity in inflammatory bowel disease
R A van Hogezand1, N A T Hamdy
1Department of Gastroenterology and Hepatology, Leiden University Medical Center, Leiden, The Netherlands. R.A.van_Hogezand.mdlz@lumc.nl

Abstract:
Patients with Crohn's disease are at increased risk of developing disturbances in bone and mineral metabolism because of several factors, including the cytokine-mediated nature of the inflammatory bowel disease, the intestinal malabsorption resulting from disease activity or from extensive intestinal resection and the use of glucucorticoids to control disease activity. Inability to achieve peak bone mass when the disease starts in childhood, malnutrition, immobilization, low BMI, smoking and hypogonadism may also play a contributing role in the pathogenesis of bone loss. The relationship between long-term use of glucocorticoids for any disease indication and increased risk for osteoporosis and fractures is well established. However, the relationship between Crohn's disease and ulcerative colitis and bone loss remains controversial. Depending on the population studied the prevalence of osteoporosis has thus been variably reported to range from 12 to 42% in patients with inflammatory bowel disease (IBD). In IBD most studies demonstrate a negative correlation between bone mineral density (BMD) and glucocorticoid use, but not all authors agree on the relationship between long-term glucocorticoid use and continuing bone loss. Whereas prospective studies do suggest sustained bone loss at both trabecular and cortical sites in long-term glucocorticoid users with inflammatory bowel disease, a decrease in bone mass is also observed in patients with active Crohn's disease not using glucocorticoids, and bone loss is not universally observed in patients with Crohn's disease using orally or rectally administered glucocorticoids. Data on vertebral fractures are scarce and there is no agreement about the risk of non-vertebral fractures in patients with Crohn's disease, although it has been suggested that non-vertebral fracture risk may be increased by up to 60% in patients with IBD. A recent publication reports an increased risk of hip fractures in Crohn's disease related to current and cumulative corticosteroid use and use of opiates, although these fractures could not be related to the severity of osteoporosis. The issue of the magnitude of the problem of osteoporosis has become particularly relevant in Crohn's disease, since the ability of therapeutic interventions to beneficially influence skeletal morbidity has been clearly established in patients with osteoporosis, whether post-menopausal women, men or glucocorticoid users. The main question that arises is whether all patients with Crohn's disease should be treated with bone protective agents on the assumption that they all have the potential to develop osteoporosis or whether the use of these agents should be restricted to patients clearly at risk of osteoporosis and fractures, providing these can be identified. We recommend, based on the available literature and our own experience, that all patients with Crohn's disease should be screened for osteoporosis by means of a bone mineral density measurement in addition to full correction of any potential calcium and vitamin D deficiency, to allow timely therapeutic intervention of the patient at risk while sparing the vast majority unnecessary medical treatment.

Related Concept Videos
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by transmural...
 01:20
Inflammatory Bowel Disease IV: Clinical Manifestations
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:26
Inflammatory Bowel Disease I: Introduction