Related Experiment Video
Updated: Aug 7, 2026


Profiling Luminal pH in Three-Dimensional Gastrointestinal Organoids Using Microelectrodes
Published on: July 5, 2024
Role of prostaglandin E receptor subtypes in gastroduodenal HCO3- secretion
Koji Takeuchi1, Eitaro Aihara, Masamune Hayashi
1Department of Pharmacology and Experimental Therapeutics, Kyoto Pharmaceutical University, Misasagi, Yamashina, Kyoto 607, Japan. takeuchi@mb.kyoto-phu.ac.jp

Abstract:
Gastroduodenal HCO3- secretion is a key process that aids in preventing acid-peptic injury. Endogenous prostaglandins (PGs) play a particularly important role in the local control of this secretion. The secretion of HCO3- in both the stomach and duodenum was increased in response to PGE2 as well as mucosal acidification, the latter occurring with concomitant enhancement of mucosal PG generation. These HCO3- responses in the duodenum were markedly reduced by prior administration of the EP4 antagonist in rats, and profoundly decreased in the animals lacking EP3 receptors but not EP1 receptors. In contrast, gastric HCO3- responses induced by PGE2 and mucosal acidification were prevented by the EP1 antagonist and disappeared in EP1, but not EP3-knockout mice. Consistent with these findings, duodenal HCO3- secretion was stimulated by both EP3 and EP4 agonists but not EP1 or EP2 agonists, while gastric HCO3- secretion was increased by the EP1 agonist but not EP2, EP3 or EP4 agonists. In addition, the HCO3- stimulatory action of sulprostone (EP1/EP3 agonist) in the stomach was inhibited by the Ca2+ antagonist verapamil but not affected by IBMX, the inhibitor of phosphodiesterase, while that in the duodenum was inhibited by verapamil and enhanced by IBMX. Forskolin, the stimulator of adenylate cyclase, increased HCO3- secretion in the duodenum but not the stomach. Thus, the HCO3- stimulatory action of PGE2 in the duodenum is mediated by both EP3 and EP4 receptors being coupled intracellularly with both Ca2+ and cAMP, while that in the stomach is mediated by EP1 receptors, coupled with Ca2+.

Related Concept Videos
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:13
Acid Suppressive Drugs for Peptic Ulcer Disease: Proton Pump Inhibitors
Gastric acid, a potent cocktail of hydrogen and chloride ions, is produced in specialized parietal cells within the...
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:21
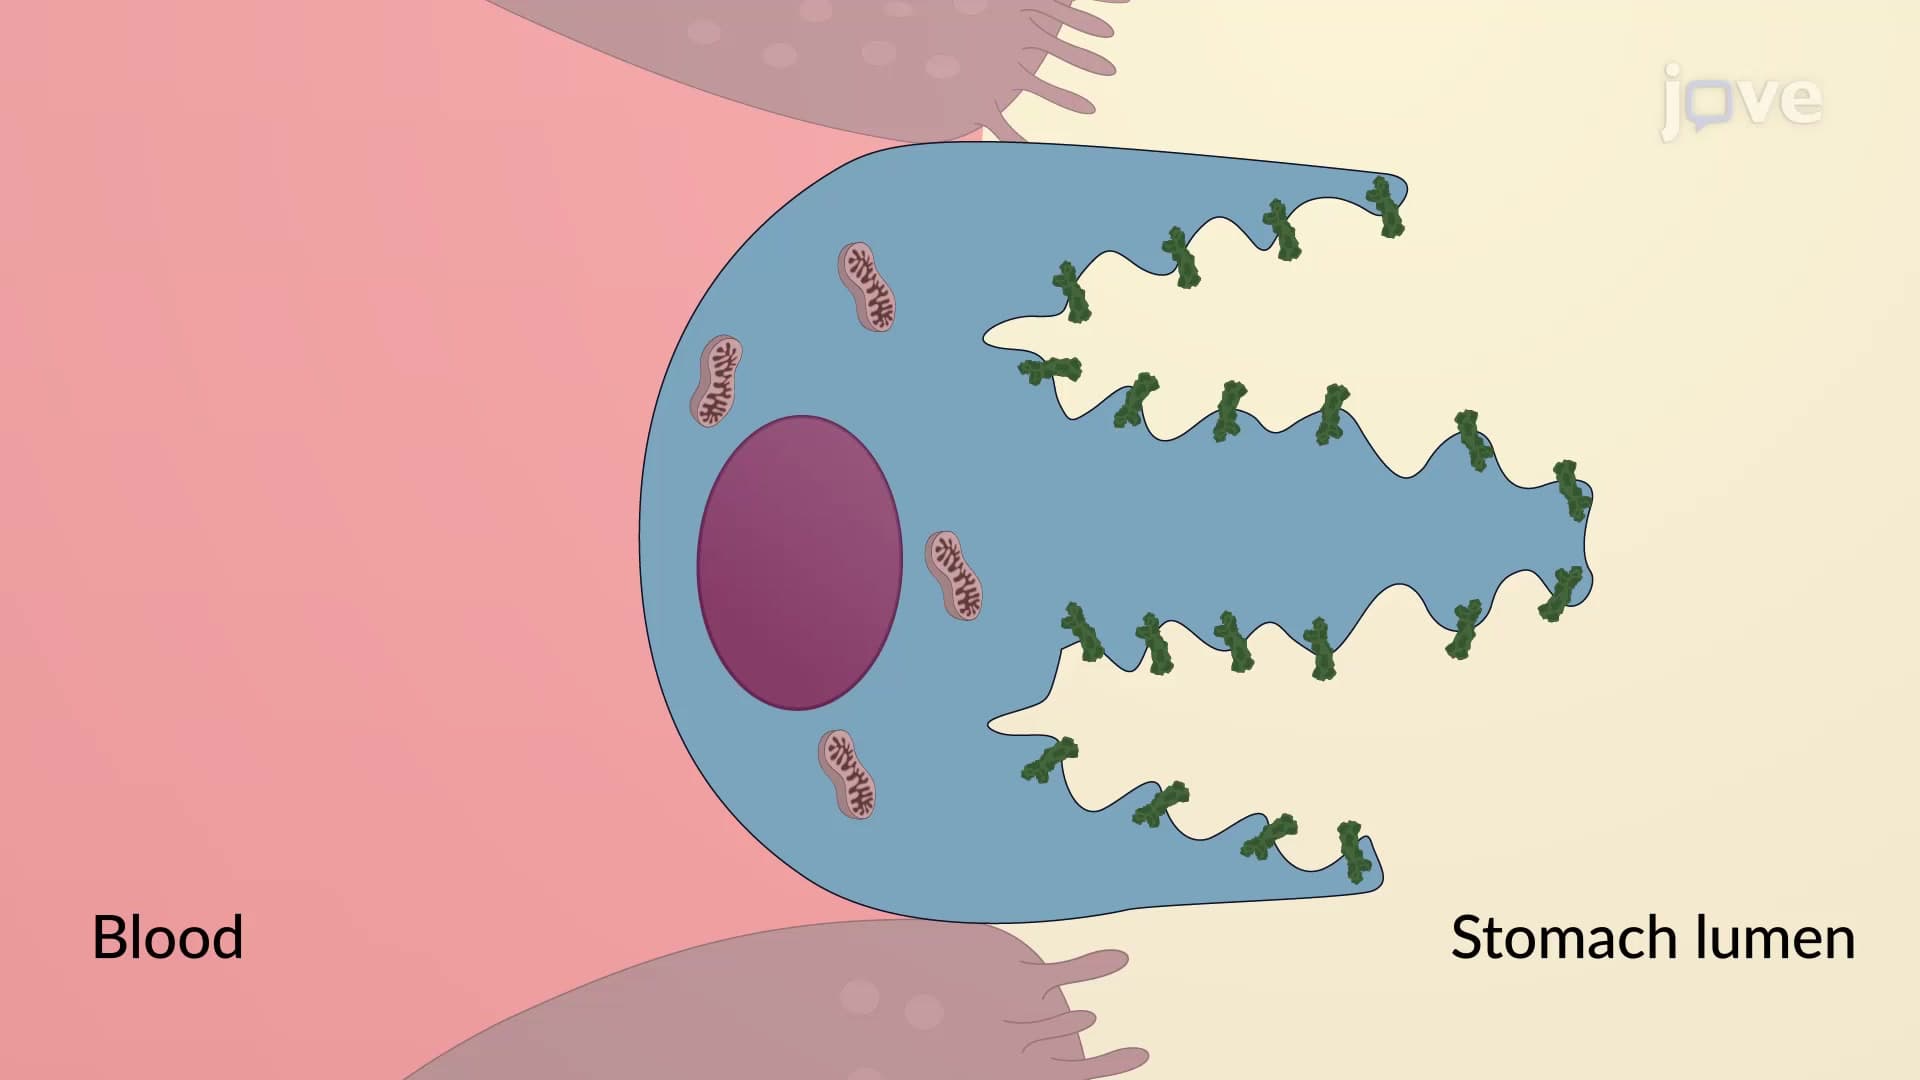
Stomach pH Regulation
The acid-secreting gastric mucosal epithelial cells (parietal cells) lining the stomach lumen maintain the low pH in the lumen. Numerous ion transporters and channels on these parietal...