Survival of propofol infusion syndrome in a head-injured patient
Related Experiment Videos
Stephanie Mallow Corbett1, Jesse Moore, Jill A Rebuck
1Department of Surgery, Division of Trauma/Critical Care, University of Vermont College of Medicine Burlington, USA.

Objective:
To describe the clinical progression of an adult patient with traumatic brain injury who survived propofol infusion syndrome.
Design:
Case report.
Setting:
Tertiary care surgical intensive care unit.
Patient:
A 21-yr-old male with traumatic brain injury was administered high doses of propofol for sedation and intracranial pressure control combined with vasopressor therapy to maintain cerebral perfusion pressure >60 mmHg. He developed a significant metabolic acidosis with a lactic acid level of 10.9 mmol/L.
Interventions:
Exploratory laparotomy, discontinuation of propofol infusion.
Measurements And Main Results:
An exploratory abdominal laparotomy was negative for traumatic injury. During the procedure, the propofol infusion was considered a possible cause and was discontinued. On review, it became apparent that a combination of high-dose propofol and catecholamines were responsible for the lactic acidosis. An echocardiogram revealed severe left ventricular dysfunction and cardiomyopathy, which resolved within 19 days.
Conclusions:
High-dose propofol should be avoided and alternative agents should be instituted for sedation and intracranial pressure management. The use of catecholamine infusions to maintain cerebral perfusion pressure in the setting of a high-dose propofol infusion may be pharmacologically unsound and may be a triggering factor for propofol infusion syndrome. Identification of the syndrome and discontinuation of propofol resulted in complete reversal of symptoms in the case described.
Related Concept Videos
 01:24
Parenteral Anesthetics: Overview
 01:26
Pharmaceutical Poisoning: Treatment Strategies
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:22
Stages of General Anesthesia
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:28
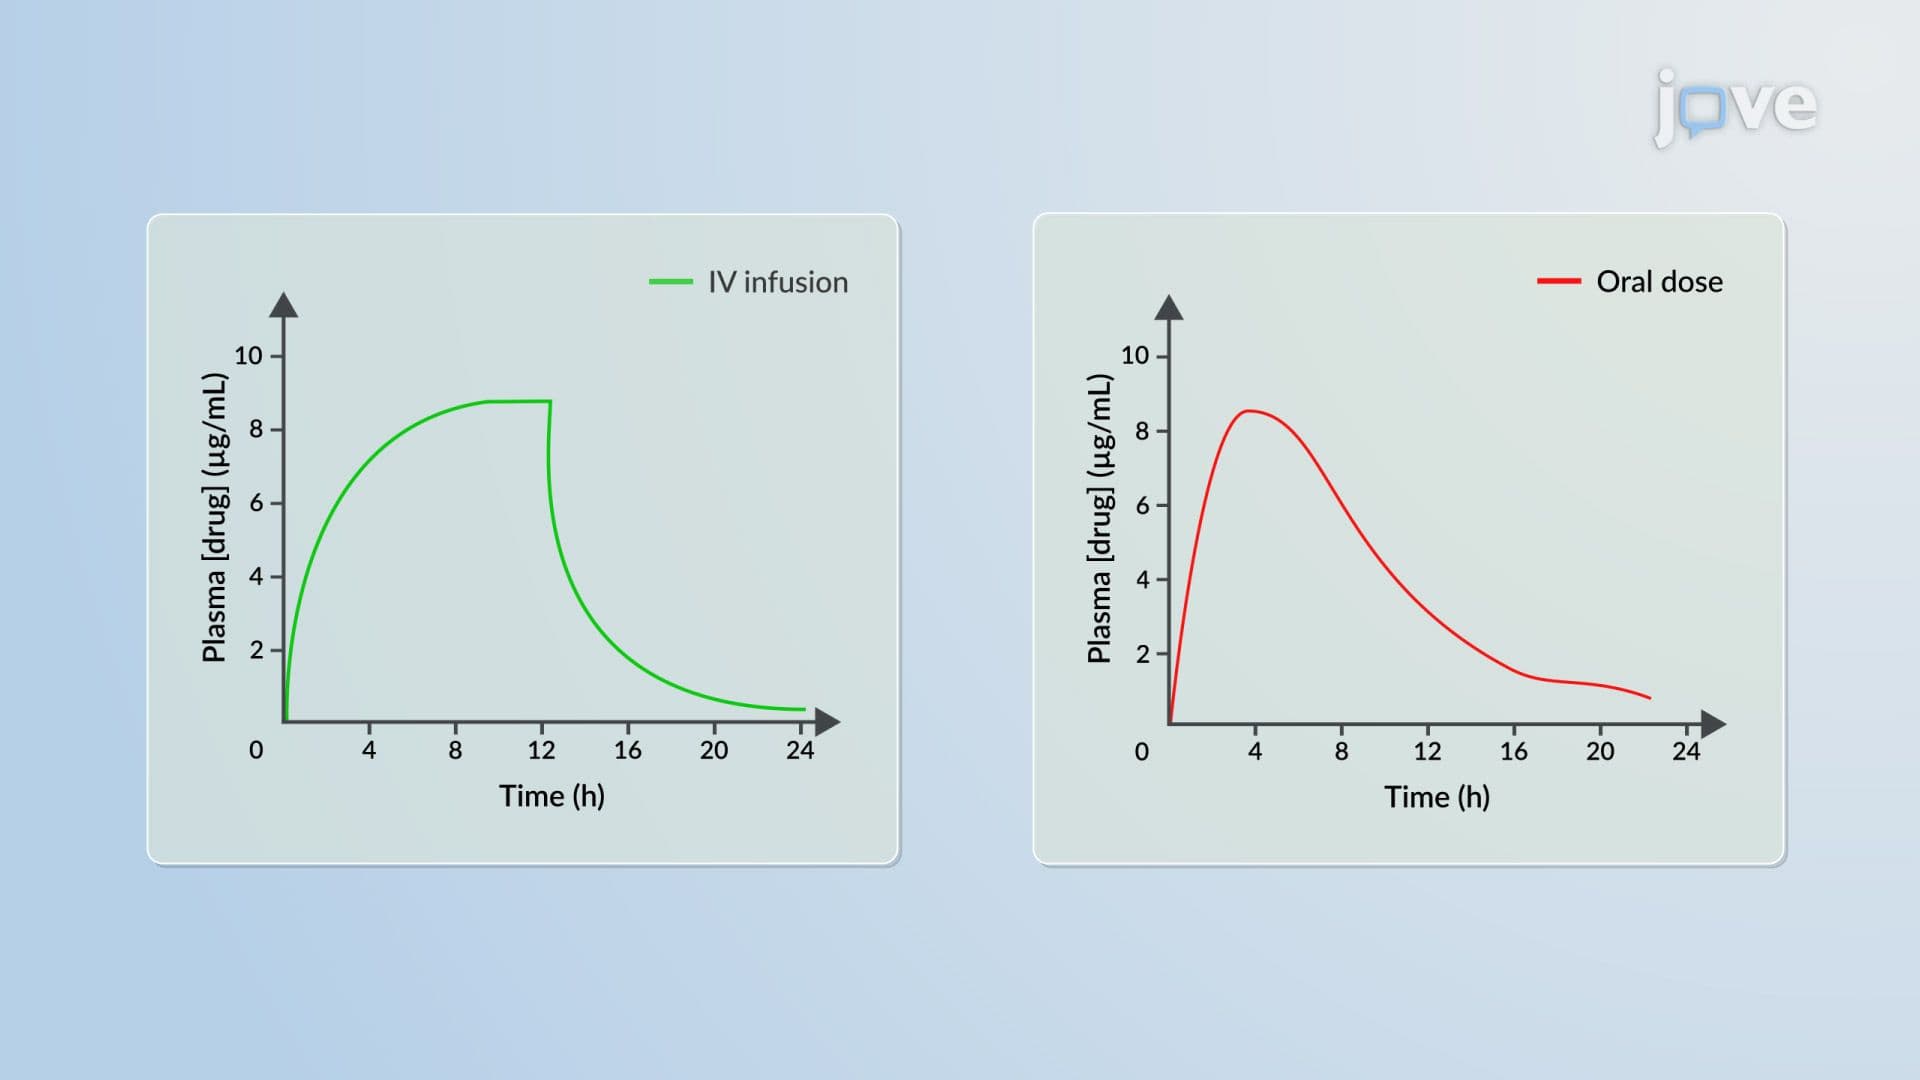
IV Infusion to Oral Dosing: Conversion Methods