Related Experiment Video
Updated: Aug 7, 2026


Fetal Echocardiography and Pulsed-wave Doppler Ultrasound in a Rabbit Model of Intrauterine Growth Restriction
Published on: June 29, 2013
Advanced maternal age is an independent risk factor for intrauterine growth restriction
Anthony O Odibo1, Deborah Nelson, David M Stamilio
1Department of Obstetrics and Gynecology, Washington University, St. Louis, Missouri 63110, and Pennsylvania Hospital of the University of Pennsylvania Health System, Obstetrics and Gynecology, Philadelphia, USA.

Reports on the association between advanced maternal age (AMA) and intrauterine growth restriction (IUGR) are conflicting. Our objective was to determine if AMA is an independent risk factor for IUGR. Our case-control study compared cases with IUGR (birthweight<10th percentile for gestational age) and a control group without IUGR. Gestational ages were all confirmed by ultrasound. The study included only singletons and fetal anomalies were excluded. Both groups were evaluated for maternal demographics and clinical risk factors. AMA was defined as maternal age>35 years. Univariate and multivariate analyses were used to examine associations. During the study period, there were 824 cases with IUGR meeting the inclusion criteria; these were compared with 1648 controls (no IUGR) randomly selected from the same population during the same study period. The significant factors associated with IUGR multivariate analyses were black race (odds ratio [OR], 22.4; 95% confidence interval [CI], 17.8 to 28); chronic hypertension (OR, 2.2; 95% CI, 1.5 to 3.2); pregestational diabetes (OR, 3.3; 95% CI, 1.6 to 7) illicit drug use (OR, 3.3; 95% CI, 2.2 to 5.2), and AMA (OR, 1.4; 95% CI, 1.1 to 1.8). There was a positive dose-response association between increasing maternal age and increasing risk for IUGR. At maternal age of 40 years or older, the OR and 95% CI for IUGR was 3.2 and 1.9 to 5.4, respectively. AMA is an independent risk factor for IUGR. Our findings suggest that screening for IUGR is indicated in women age 35 years or older.
Reports on the association between advanced maternal age (AMA) and intrauterine growth restriction (IUGR) are conflicting. Our objective was to determine if AMA is an independent risk factor for IUGR. Our case-control study compared cases with IUGR (birthweight<10th percentile for gestational age) and a control group without IUGR. Gestational ages were all confirmed by ultrasound. The study included only singletons and fetal anomalies were excluded. Both groups were evaluated for maternal demographics and clinical risk factors. AMA was defined as maternal age>35 years. Univariate and multivariate analyses were used to examine associations. During the study period, there were 824 cases with IUGR meeting the inclusion criteria; these were compared with 1648 controls (no IUGR) randomly selected from the same population during the same study period. The significant factors associated with IUGR multivariate analyses were black race (odds ratio [OR], 22.4; 95% confidence interval [CI], 17.8 to 28); chronic hypertension (OR, 2.2; 95% CI, 1.5 to 3.2); pregestational diabetes (OR, 3.3; 95% CI, 1.6 to 7) illicit drug use (OR, 3.3; 95% CI, 2.2 to 5.2), and AMA (OR, 1.4; 95% CI, 1.1 to 1.8). There was a positive dose-response association between increasing maternal age and increasing risk for IUGR. At maternal age of 40 years or older, the OR and 95% CI for IUGR was 3.2 and 1.9 to 5.4, respectively. AMA is an independent risk factor for IUGR. Our findings suggest that screening for IUGR is indicated in women age 35 years or older.
Related Concept Videos
 02:07
Oogenesis
 01:21
Nondisjunction
 01:07
Teratogenicity
 02:57
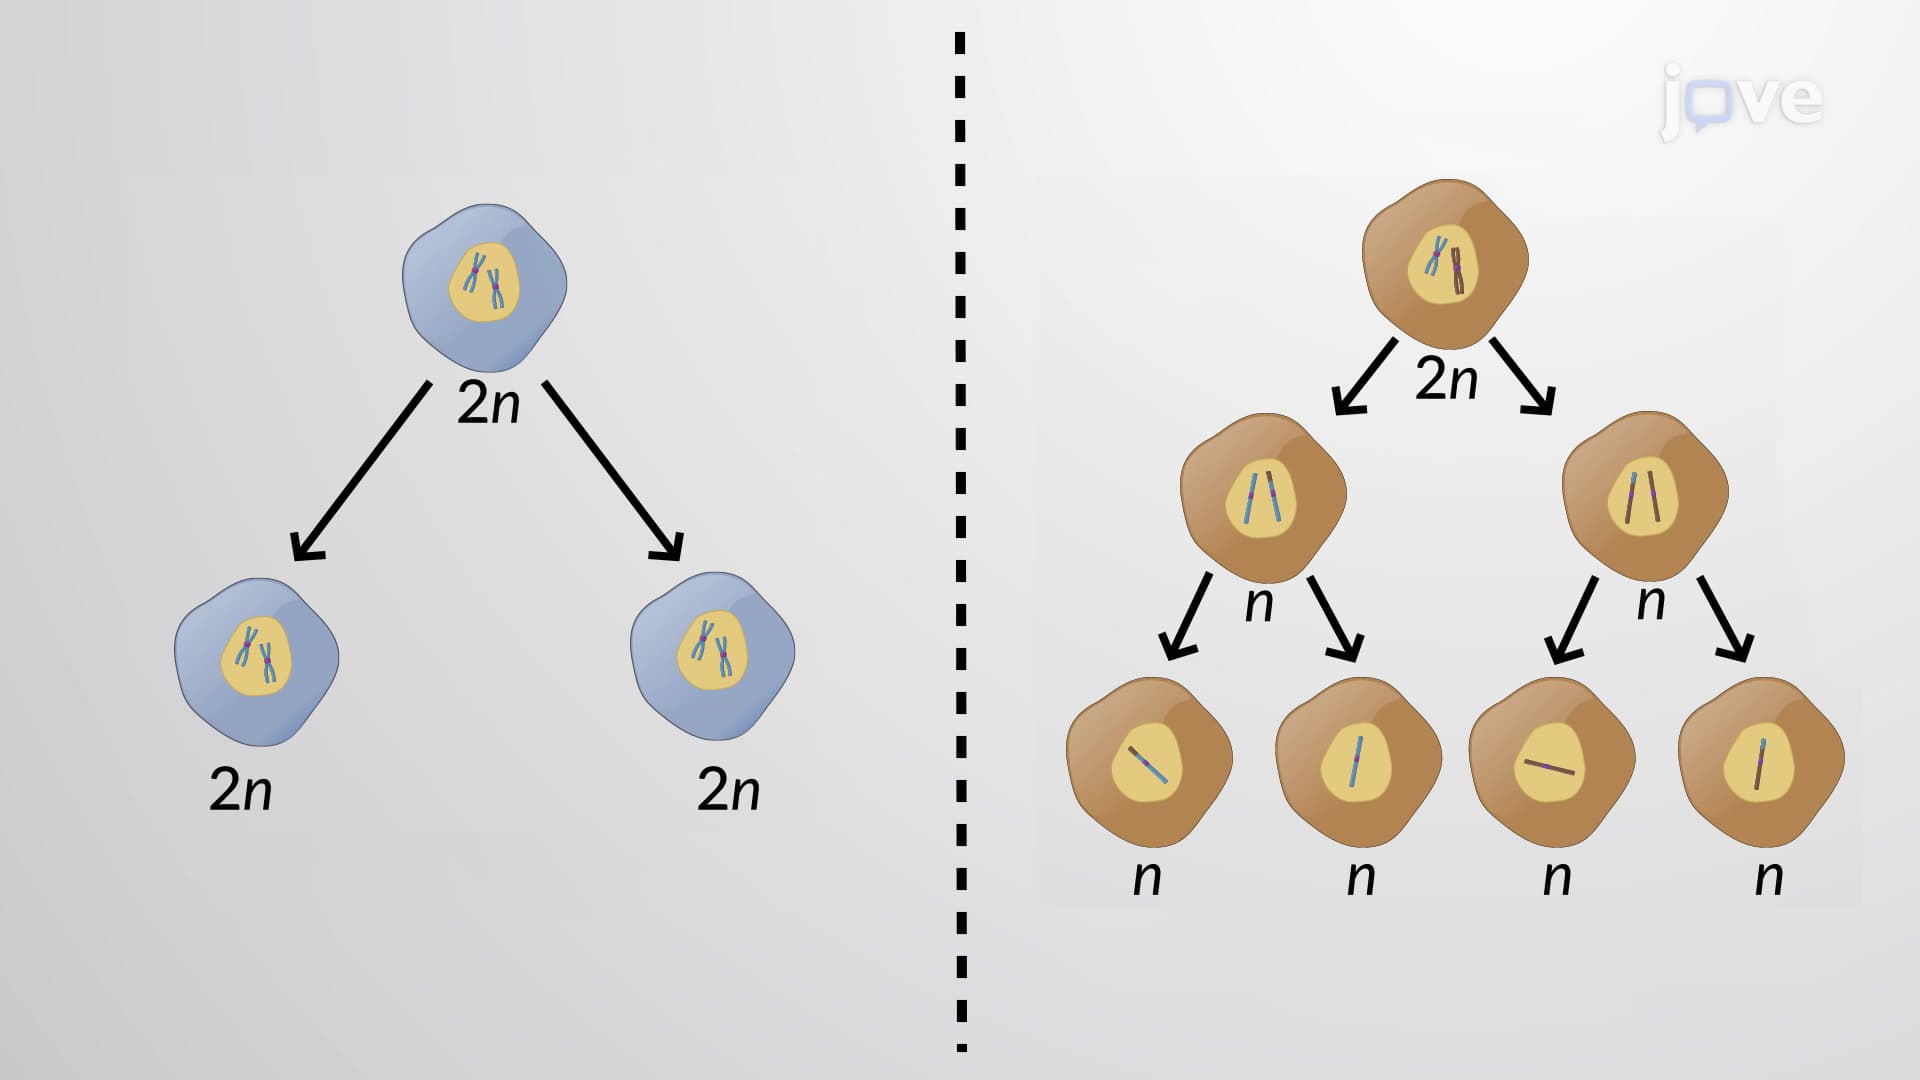
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:52
Regression Toward the Mean