Related Experiment Video
Updated: Aug 7, 2026
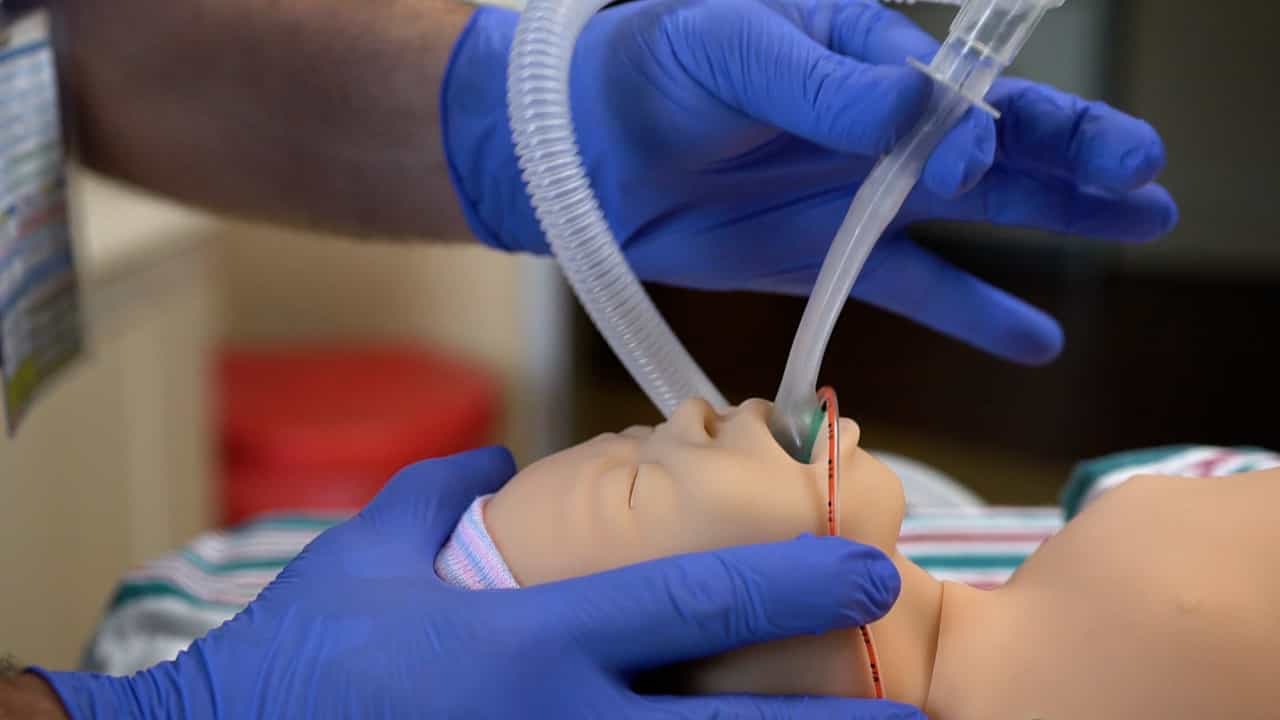
Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
Effect of propofol anesthesia and continuous positive airway pressure on upper airway size and configuration in
Mark W Crawford1, Denise Rohan, Christopher K Macgowan
1Department of Anesthesia, The Hospital for Sick Children, University of Toronto, Ontario, Canada. mark.crawford@sickkids.ca

Insights
Propofol anesthesia narrows infant airways, primarily in the front-to-back dimension. Continuous positive airway pressure (CPAP) effectively widens the airway, counteracting this narrowing by increasing its side-to-side dimension.
Area of Science:
- Anesthesiology
- Pediatric Airway Management
- Medical Imaging
Background:
- Infants are susceptible to upper airway obstruction during general anesthesia.
- Continuous positive airway pressure (CPAP) is a common intervention for anesthesia-induced airway obstruction.
- Understanding the interplay between anesthetic agents and airway support is crucial for patient safety.
Purpose of the Study:
- To investigate the effects of propofol anesthesia depth on infant airway caliber.
- To evaluate the impact of continuous positive airway pressure (CPAP) on propofol-induced airway narrowing in infants.
- To analyze the dimensional changes in the infant airway under different anesthetic and CPAP conditions.
Main Methods:
- Nine infants undergoing elective brain MRI were studied.
- Magnetic resonance imaging (MRI) captured airway images at key anatomical levels (soft palate, tongue base, epiglottis).
- Airway dimensions were assessed during light propofol, deep propofol, and deep propofol with CPAP (10 cm H2O).
Main Results:
- Increasing propofol anesthesia depth led to decreased airway caliber, mainly through anteroposterior narrowing.
- Application of CPAP completely reversed the propofol-induced airway narrowing.
- CPAP primarily increased the transverse (side-to-side) dimension of the airway, counteracting the anteroposterior narrowing.
Conclusions:
- Propofol-induced airway narrowing in infants is primarily anteroposterior.
- CPAP effectively mitigates propofol-induced airway narrowing by increasing the transverse dimension.
- While overall airway caliber may appear similar, significant configurational differences exist between light anesthesia and deep anesthesia with CPAP.
Background:
Infants are prone to obstruction of the upper airway during general anesthesia. Continuous positive airway pressure (CPAP) is often used to prevent or treat anesthesia-induced airway obstruction. The authors studied the interaction of propofol anesthesia and CPAP on airway caliber in infants using magnetic resonance imaging.
Methods:
Nine infants undergoing elective magnetic resonance imaging of the brain were studied. Head position was standardized. Spin echo magnetic resonance images of the airway were acquired at the level of the soft palate, base of the tongue, and tip of the epiglottis. Four sets of images were acquired in sequence: (1) during light propofol anesthesia at an infusion rate of 80 microg . kg(-1) . min(-1), (2) after increasing the depth of propofol anesthesia by administering a bolus dose (2.0 mg/kg) and increasing the infusion rate to 240 microg . kg(-1) . min(-1), (3) during continued infusion of 240 microg . kg(-1). min propofol and application of 10 cm H2O CPAP, and (4) after removal of CPAP and continued infusion of 240 microg . kg(-1). min propofol.
Results:
Increasing depth of propofol anesthesia decreased airway caliber at each anatomical level, predominantly due to anteroposterior narrowing. Application of CPAP completely reversed the propofol-induced decrease in airway caliber, primarily by increasing the transverse dimension.
Conclusions:
Airway narrowing with increasing depth of propofol anesthesia results predominantly from a reduction in anteroposterior dimension, whereas CPAP acts primarily to increase the transverse dimension. Although airway caliber during deep propofol anesthesia and application of CPAP was similar to that during light propofol anesthesia, there were significant configurational differences.
Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...