Related Experiment Video
Updated: Aug 7, 2026
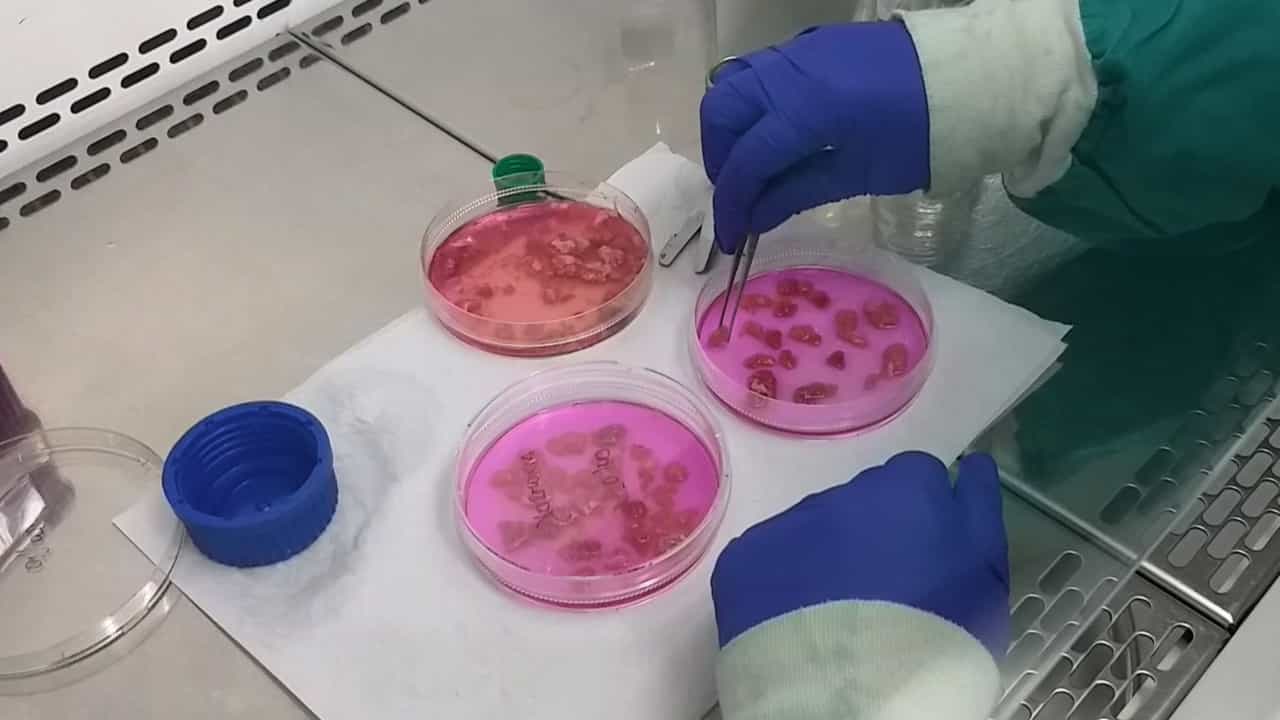
Disruption of the Mouse Blood-Brain Barrier by Small Extracellular Vesicles from Hypoxic Human Placentas
Published on: January 26, 2024
Shared and disparate components of the pathophysiologies of fetal growth restriction and preeclampsia
1Department of Epidemiology, University of Pittsburgh, Graduate School of Public Health, Pittsburgh, PA 15261, USA. repro@pitt.edu

Intrauterine growth restriction (IUGR) and preeclampsia differ in their association with maternal disease but share a similar placental pathology. Moreover, mothers who have had pregnancies complicated by preeclampsia or IUGR are at elevated later-life cardiovascular risk. Why, then, do some women develop IUGR and others develop preeclampsia? In this clinical opinion, based on a review of the literature, we hypothesize that both women experiencing preeclampsia and IUGR enter pregnancy with some degree of endothelial dysfunction, a lesion that predisposes to shallow placentation. In our opinion, preeclampsia develops when abnormal placentation, through the mediator of elevated circulating cytokines, interacts with maternal metabolic syndrome, comprised of adiposity, insulin resistance/hyperglycemia, hyperlipidemia, and coagulopathy. IUGR develops in the absence of antenatal metabolic syndrome. Among these women, the baby is affected by shallow placentation but the mother does not develop clinically apparent disease. This conceptualization provides a testable framework for future etiologic studies of preeclampsia and IUGR.
Intrauterine growth restriction (IUGR) and preeclampsia differ in their association with maternal disease but share a similar placental pathology. Moreover, mothers who have had pregnancies complicated by preeclampsia or IUGR are at elevated later-life cardiovascular risk. Why, then, do some women develop IUGR and others develop preeclampsia? In this clinical opinion, based on a review of the literature, we hypothesize that both women experiencing preeclampsia and IUGR enter pregnancy with some degree of endothelial dysfunction, a lesion that predisposes to shallow placentation. In our opinion, preeclampsia develops when abnormal placentation, through the mediator of elevated circulating cytokines, interacts with maternal metabolic syndrome, comprised of adiposity, insulin resistance/hyperglycemia, hyperlipidemia, and coagulopathy. IUGR develops in the absence of antenatal metabolic syndrome. Among these women, the baby is affected by shallow placentation but the mother does not develop clinically apparent disease. This conceptualization provides a testable framework for future etiologic studies of preeclampsia and IUGR.

Related Concept Videos
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...
 01:07
Teratogenicity
 01:33
Hormonal Regulation
 01:19
Interactions Between Signaling Pathways
Convergence and divergence, and cross-talk between signaling pathways
Two distinct signaling pathways can converge on a single functional unit, which may either be a single protein or a complex of proteins. The response is either functionally distinct or synergistic between the two pathways but different from the response...
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:23
Factors Affecting Drug Distribution: Physiological Barriers
The capillary endothelial barrier allows only smaller molecules below 600 Da (Daltons) to pass through. It also restricts drugs like heparin that are bound to blood components, limiting their movement within the bloodstream.
The...