Related Experiment Video
Updated: May 28, 2026
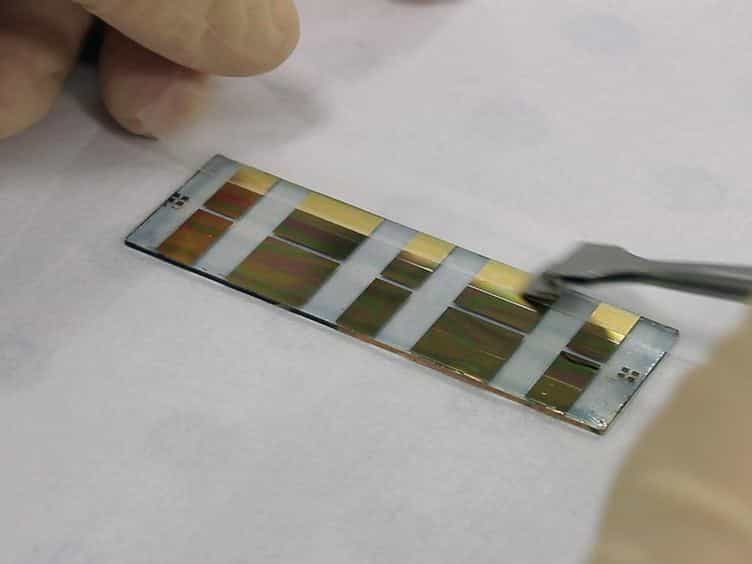

Sensing of Barrier Tissue Disruption with an Organic Electrochemical Transistor
Published on: February 10, 2014
Changes in expression and distribution of claudin 2, 5 and 8 lead to discontinuous tight junctions and barrier
S Zeissig1, N Bürgel, D Günzel
1Department of Gastroenterology, Charité, Campus Benjamin Franklin, Hindenburgdamm 30, 12200 Berlin, Germany.

Background:
Epithelial barrier function is impaired in Crohn's disease.
Aim:
To define the underlying cellular mechanisms with special attention to tight junctions.
Methods:
Biopsy specimens from the sigmoid colon of patients with mild to moderately active or inactive Crohn's disease were studied in Ussing chambers, and barrier function was determined by impedance analysis and conductance scanning. Tight junction structure was analysed by freeze fracture electron microscopy, and tight junction proteins were investigated immunohistochemically by confocal laser scanning microscopy and quantified in immunoblots. Epithelial apoptosis was analysed in terminal deoxynucleotidyl transferase-mediated deoxyuridine triphosphate nick-end labelling and 4',6-diamidino-2-phenylindole staining.
Results:
Patients with active Crohn's disease showed an impaired intestinal barrier function as indicated by a distinct reduction in epithelial resistance. As distribution of conductivity was even, focal epithelial lesions (eg, microerosions) did not contribute to barrier dysfunction. Instead, freeze fracture electron microscopy analysis showed reduced and discontinuous tight junction strands. Occludin and the sealing tight junction proteins claudin 5 and claudin 8 were downregulated and redistributed off the tight junction, whereas the pore-forming tight junctions protein claudin 2 was strongly upregulated, which constitute the molecular basis of tight junction changes. Other claudins were unchanged (claudins 1, 4 and 7) or not detectable in sigmoid colon (claudins 11, 12, 14, 15 and 16). Claudin 2 upregulation was less pronounced in active Crohn's disease compared with active ulcerative colitis and was inducible by tumour necrosis factor alpha. As a second source of impaired barrier function, epithelial apoptosis was distinctly increased in active Crohn's disease (mean (SD) 5.2 (0.5)% v 1.9 (0.2)% in control). By contrast, barrier function, tight junction proteins and apoptosis were unaffected in Crohn's disease in remission.
Conclusion:
Upregulation of pore-forming claudin 2 and downregulation and redistribution of sealing claudins 5 and 8 lead to altered tight junction structure and pronounced barrier dysfunction already in mild to moderately active Crohn's disease.
More Related Videos


Related Concept Videos
 01:29
Tight Junctions
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by transmural...
 01:20
Inflammatory Bowel Disease II: Ulcerative Colitis
 01:25
Inflammatory Bowel Disease III: Crohn's Disease
 01:20
Inflammatory Bowel Disease IV: Clinical Manifestations