Related Experiment Video
Updated: Aug 7, 2026

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Pre-surgical evaluation and surgical treatment in children with extratemporal epilepsy
Ricardo Silva Centeno1, Elza Marcia Yacubian, Americo Ceiki Sakamoto
1Universidade Federal de São Paulo, Departamento de Neurologia/Neurocirurgia, Disciplina de Neurocirurgia. Rua Napoleão de Barros, 715-6 andar Vila Clementino 04024-002, São Paulo, SP, Brazil.

Insights
Early epilepsy surgery offers improved outcomes for children with medically refractory seizures. Advances in neuroimaging and neuronavigation enhance surgical precision and patient quality of life.
Area of Science:
- Pediatric Neurology
- Neurosurgery
Background:
- Extratemporal epilepsy in children often presents with variable ictal behavior and medically refractory seizures.
- Focal cortical resection is effective but carries risks, especially with widespread lesions.
- Anterior temporal lobectomy may be a safer alternative for certain cases.
Purpose of the Study:
- To review pre-surgical evaluation and surgical treatment strategies for pediatric extratemporal epilepsy.
- To highlight the importance of identifying the epileptogenic zone and its relation to eloquent areas.
- To emphasize the goal of seizure control, reduced morbidity, and improved quality of life.
Main Methods:
- Review of pre-surgical evaluation protocols for extratemporal epilepsy.
- Analysis of surgical treatment options, including focal cortical resection and anterior temporal lobectomy.
- Consideration of neuroimaging and neuronavigation technologies in surgical planning.
Main Results:
- The pediatric brain's plasticity facilitates greater functional recovery post-surgery compared to adults.
- Preoperative evaluation and surgical strategy are tailored to the epileptogenic zone and lesion characteristics.
- Technological advancements, particularly MRI-based neuronavigation, improve surgical accuracy.
Conclusions:
- Early surgical intervention is recommended for children with intractable epilepsy.
- Surgical treatment is a recognized therapeutic option for chronic pediatric epilepsy.
- Improved neuroimaging and neuronavigation facilitate consideration of surgical treatment for epilepsy.
Introduction:
This review summarizes some patterns of pre-surgical evaluation and surgical treatment of extratemporal epilepsy in pediatric patients with medically refractory seizures, whose ictal behavior is variable. The most effective treatment for intractable partial epilepsy is a focal cortical resection with excision of the epileptogenic zone (the area of ictal onset and initial seizure propagation). This might be risky, though, in the case of a widespread lesion, sometimes encroaching one or more lobes, given the risk to the functional cerebral cortex. An anterior temporal lobectomy might prove more effective then in preventing seizures with fewer potential complications. If partial extratemporal epilepsy is associated with pharmaco-resistant seizures, the preoperative evaluation and operative strategy are determined according to the epileptogenic zone and to the relationship between a substrate-directed disorder and eloquent areas. The pediatric treatment of extratemporal epilepsy is aimed at controlling the seizures, avoiding morbidity, and improving the patient's quality of life through psychosocial integration. Since the immature brain is more plastic than when mature, the recovery of functions after surgery is greater in children than in adults.
Recommendation:
Early surgery is recommended for children with intractable epilepsy, and is now accepted as an important therapeutic modality also for children with chronic epilepsy.
Conclusion:
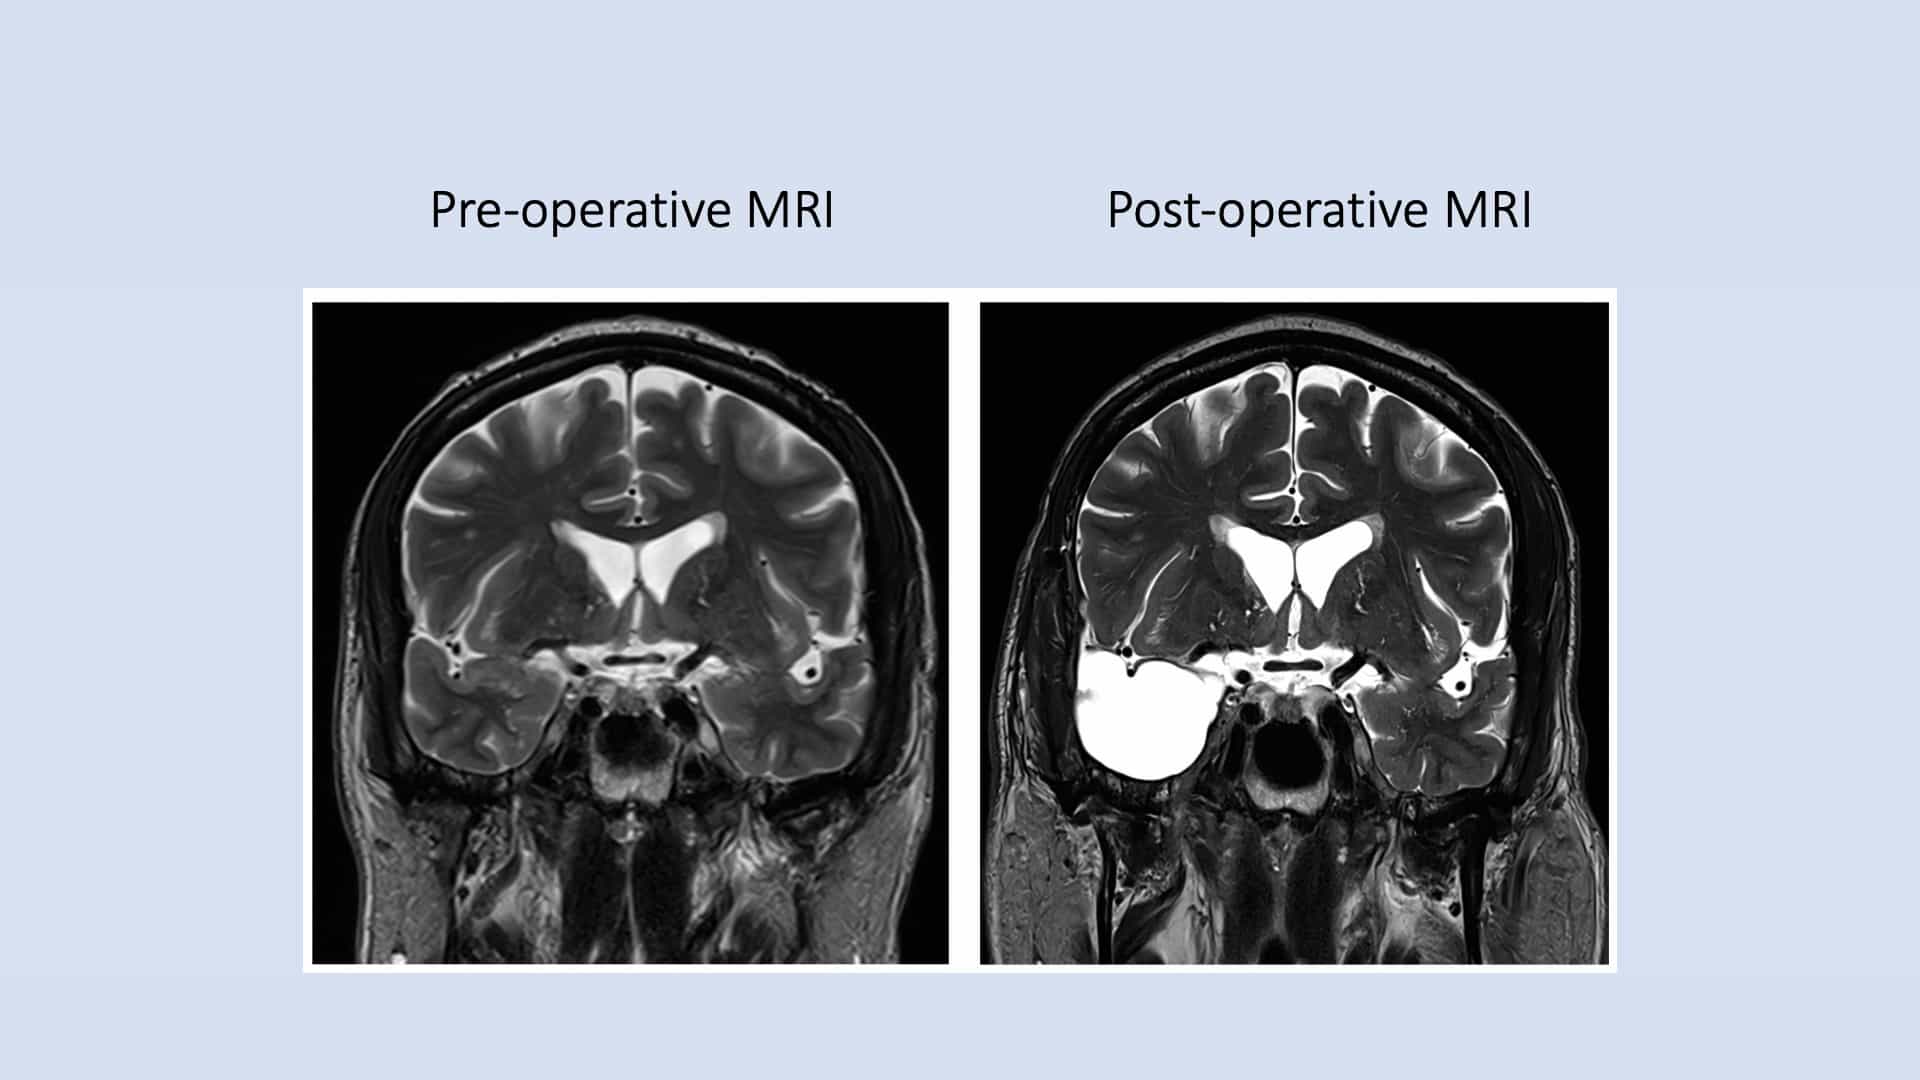
Technological advances in the last two decades, mainly in neuroimaging, have led many medical centers to consider surgical treatment of epilepsy, accuracy being granted by MRI-based neuronavigation systems-an interface between the lesion seen in the preoperative magnetic resonance imaging (MRI) and the operative field, often invisible to the surgeon.