Related Experiment Video
Updated: Aug 7, 2026
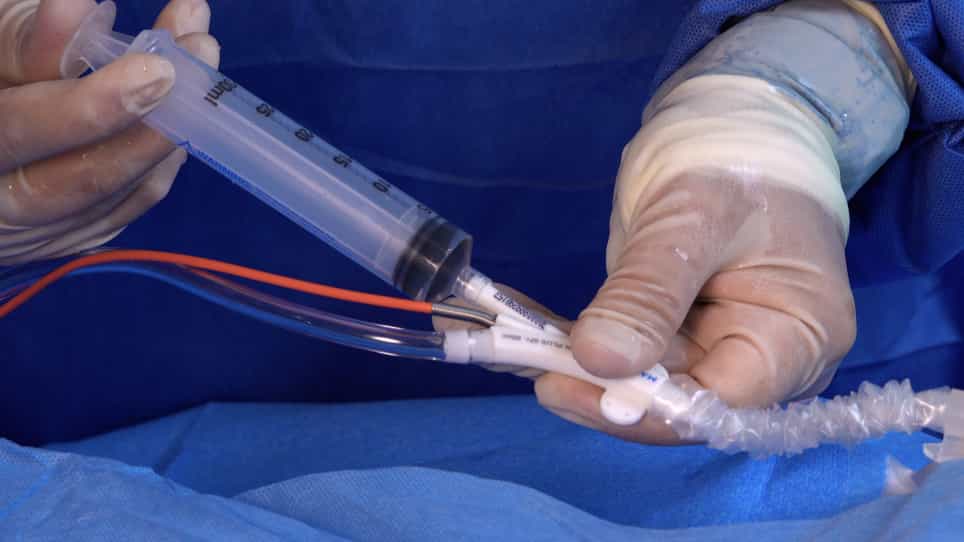
The Intra-Aortic Balloon Pump
Published on: February 5, 2021
[Coronary angioplasty for primary cardiogenic shock following acute myocardial infarction]
Georges Badaoui1, Antoine Sarkis, Rabih Azar
1Service de Cardiologie, Hôtel-Dieu de France, Beyrouth, Liban. georges.badaoui@hdf.usj.edu.lb

Insights
Emergency percutaneous coronary angioplasty (PTCA) for acute myocardial infarction (AMI) complicated by cardiogenic shock (CS) significantly reduces in-hospital mortality. Early revascularization is crucial for improving survival rates in these critical patients.
Area of Science:
- Cardiology
- Interventional Cardiology
- Acute Myocardial Infarction Research
Context:
- Acute myocardial infarction (AMI) complicated by cardiogenic shock (CS) historically carries a high mortality rate.
- While emergency percutaneous coronary angioplasty (PTCA) is known to reduce mortality in primary CS, outcomes in unselected AMI patients with immediate CS onset require further investigation.
Purpose:
- To evaluate the in-hospital mortality rate for patients admitted with Q-wave AMI presenting with CS.
- To assess the effectiveness of direct PTCA in managing AMI complicated by CS.
Summary:
- A study of 30 consecutive patients with AMI and CS treated with direct PTCA showed an 87% success rate.
- In-hospital mortality was 37%, with survival significantly higher when revascularization occurred within 120 minutes of CS onset.
- Key interventions included PTCA, intra-aortic balloon pumps, cardiopulmonary resuscitation, and inotropes.
Impact:
- Direct PTCA for AMI with CS can be performed successfully, leading to a significant reduction in in-hospital mortality.
- Early revascularization (within 120 minutes) is associated with the most substantial improvement in survival for these high-risk patients.
Background:
In the setting of acute myocardial infarction (AMI), several investigators have demonstrated that emergency coronary angioplasty (PTCA) reduces in-hospital mortality of primary cardiogenic shock (CS) from 90% to less than 50% ; however, few studies have focused on the current outcome of non selected patients in whom the onset of AMI is immediately complicated by CS.
Purpose Of The Study:
To evaluate in-hospital mortality of the patients admitted to our institution for Q wave AMI presented in CS.
Material And Method:
Between 05/93 and 05/03, 30 consecutive pts, 26 men and 4 women, in CS following AMI were treated with direct PTCA, 26 without thrombolysis and 4 as rescue after failed streptokinase. AMI was defined by prolonged chest pain and > or =1 mm ST segment elevation in > or =2 contiguous peripheral leads or > or =2 mm for precordial leads on the admission ECG. The diagnosis of CS was based on the combination of systolic blood pressure of <90 mm Hg, unresponsive to volume expansion, signs of acute circulatory failure (cyanosis, cold extremities, restlessness, mental confusion or coma) and congestive heart failure secondary to myocardial dysfunction. In 40% of cases the diagnosis of CS was only clinical and in 60% of cases was confirmed by a Swan Ganz catheter. Mean age was 62.3 +/- 12.3 years, 7 had triple vessel disease, 14 a double vessel disease, 8 a single vessel disease and in one case a left main disease. The AMI was anterior in 22 pts (73%), inferior in 8 (27%). Intraaortic balloon was used in 3 pts, CPR in 16 (47%), transitory pacemaker in 1 pt, inotropes in 25 pts, emergency coronary artery bypass grafting (CABG) in 1 pt.
Results:
Success for PTCA with a residual stenosis < 50% and a TIMI flow III was obtained in 26 pts (87%). Mean time between CS and revascularization was 219 +/- 302 minutes. 19 pts (63%) survived and 11 pts (37%) died while at the hospital, 6 from intractable shock, 4 from multiple organ failure and in 1 case from pulmonary hemorrhage. Mean time of revascularization for the surviving was 190 +/- 329 min, and for the dead 295 +/- 212 min. Hospital mortality for inferior infarction is 12.5% after successful angioplasty. Comparison of surviving and non surviving number of patients according to revascularization time showed a significant difference of these groups whether the revascularization was accomplished before or after 120 minutes. [table: see text]
Conclusion:
Direct PTCA for AMI immediately complicated by CS, can be achieved with a high success rate, and can significantly reduce in-hospital mortality; this improvement of survival is most evident if revascularizarion is performed early.
More Related Videos
 14:35
Post-Myocardial Infarction Heart Failure in Closed-chest Coronary Occlusion/Reperfusion Model in Göttingen Minipigs and Landrace Pigs
Published on: April 17, 2021
 06:10
Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
Related Concept Videos
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:30
Acute Coronary Syndrome I: Introduction
 01:26
Acute Coronary Syndrome V: Nursing Management
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
Angina IV: Management