Further errors in polymorph identification: furosemide and finasteride

Sohrab Karami1, Yang Li, David S Hughes

  • 1School of Chemistry, University of Southampton, Highfield, Southampton SO17 1BJ, England.

Related Concept Videos

Renal Failure: Dose Adjustments01:11

Renal Failure: Dose Adjustments

In patients with renal impairment, drugs undergo significant changes in their pharmacokinetics, which require dosage adjustments to ensure safe and effective therapy.
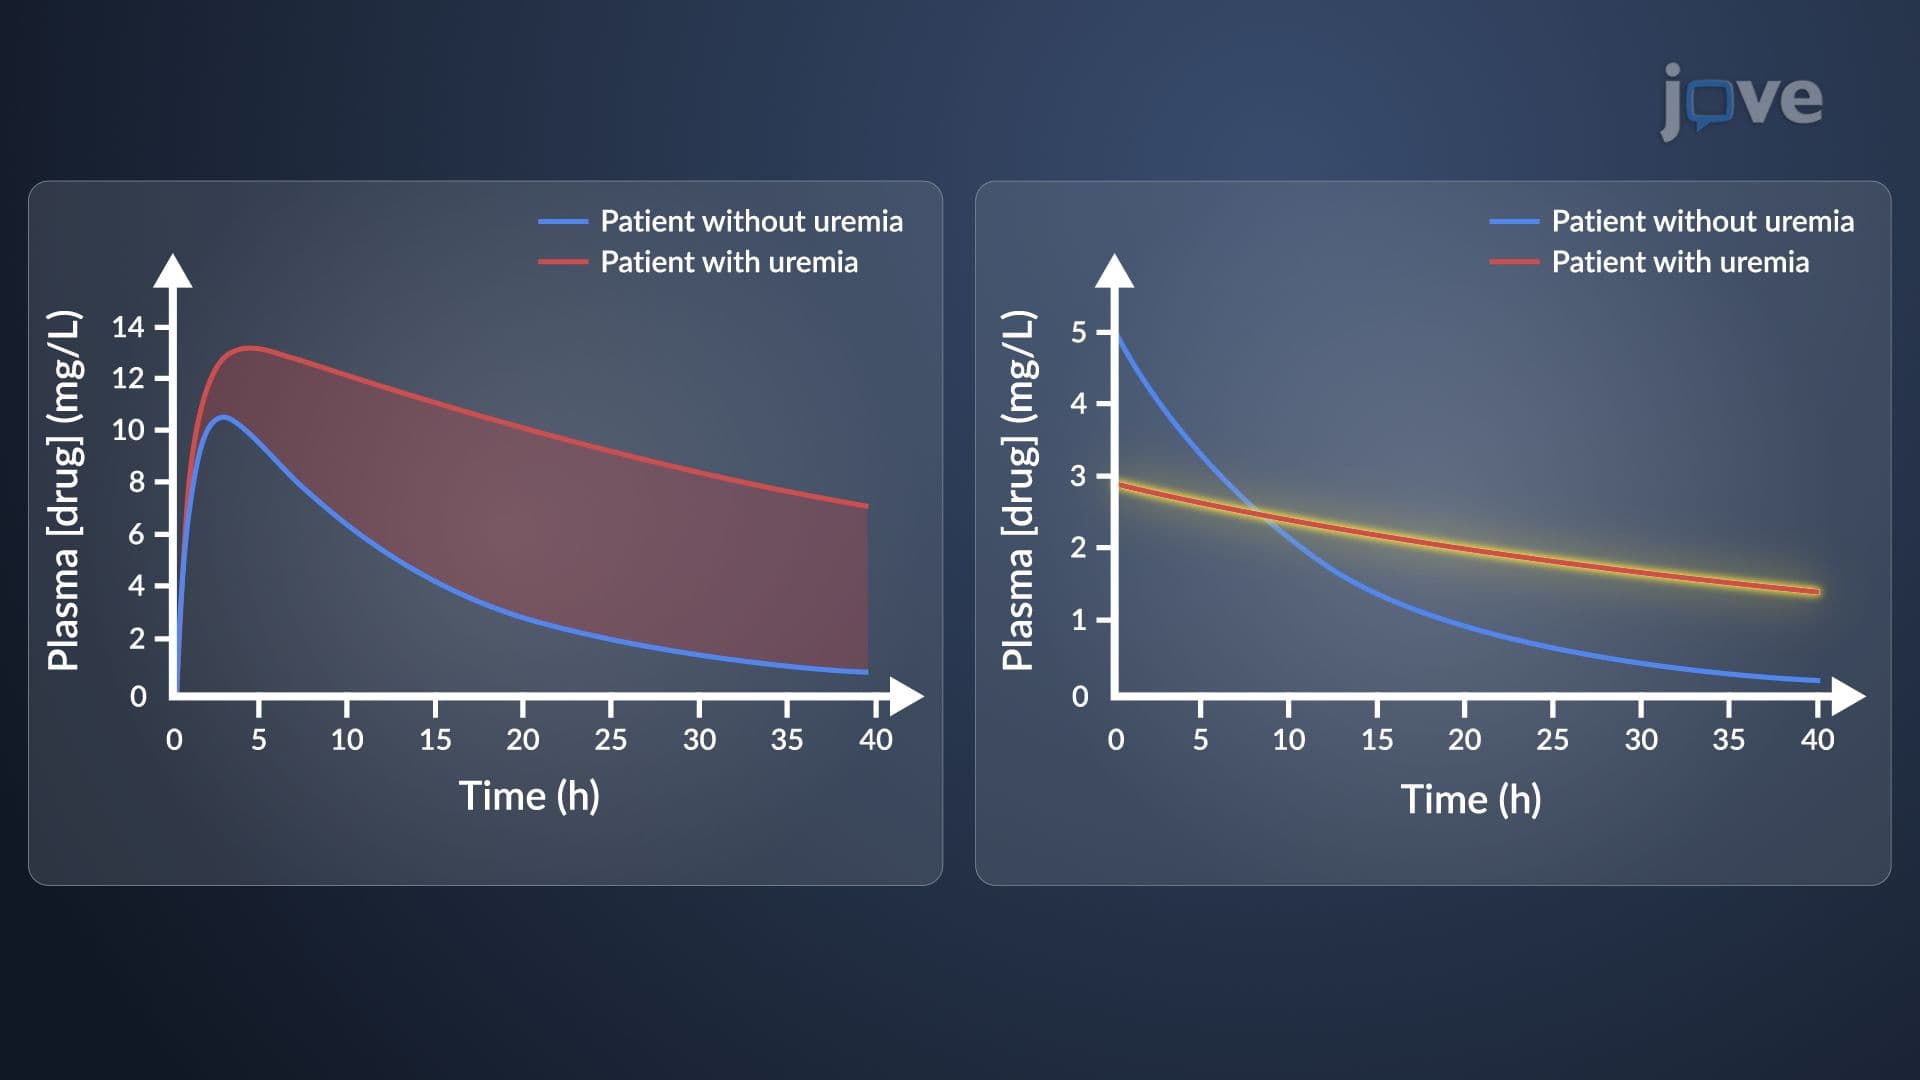
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
Pharmaceutical Alternatives: Polymorphic Form-Related and Particle Size-Related Therapeutic Nonequivalence01:27

Pharmaceutical Alternatives: Polymorphic Form-Related and Particle Size-Related Therapeutic Nonequivalence
Changes in polymorphic forms can significantly influence the bioavailability of poorly soluble drugs. Although the FDA defines pharmaceutical equivalence based on having the same active ingredient, dosage form, and route of administration, it does not automatically disqualify products with different polymorphic forms. This means two products with different polymorphs can still be deemed pharmaceutically equivalent. However, polymorphic differences can affect properties like wettability,...
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant01:25

Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant

In patients with renal disease, dosage adjustments are necessary to maintain therapeutic plasma drug concentrations and prevent toxicity or subtherapeutic exposure. Renal impairment alters drug pharmacokinetics, especially in conditions like uremia, where changes such as prolonged elimination half-life and altered apparent volume of distribution can significantly affect drug disposition. These changes require careful modification of the dosing regimen to achieve the desired clinical...
Renal Drug Excretion: Tubular Secretion01:28

Renal Drug Excretion: Tubular Secretion

Active tubular secretion is a robust, energy-demanding process that utilizes carrier systems to transport drugs into renal tubules. The active renal secretion systems include the organic anion transporter (OAT) for weak acids and the organic cation transporter (OCT) for weak bases. Structurally similar drugs can compete for the same transporter, potentially leading to drug accumulation and toxicity. However, this principle can be exploited therapeutically. One example is probenecid (Probalan),...
Nephrotic Syndrome II : Assessment and Medical Management01:26

Nephrotic Syndrome II : Assessment and Medical Management

IntroductionNephrotic syndrome is a kidney disorder marked by excessive protein loss in the urine, leading to various systemic complications. This condition often results from damage to the glomeruli—the kidney's filtering units—causing proteinuria, low blood protein levels, and fluid retention. Understanding the assessment, diagnosis, and management of nephrotic syndrome is essential for effective treatment and prevention of further kidney damage.AssessmentPatient History: Document any history...
Pharmacogenetics of Drug Metabolism: Overview01:27

Pharmacogenetics of Drug Metabolism: Overview

Genetic polymorphism in drug metabolism is crucial to the inter-individual variability observed in drug responses. Drug metabolism primarily involves the chemical modification of drugs and other xenobiotics to enhance their elimination by increasing their polarity. Two main classes of enzymes mediate this biotransformation process: Phase I enzymes, primarily cytochrome P450s, catalyze oxidation and reduction reactions, while other enzymes, such as esterases, mediate hydrolysis, and Phase II...

