
How can the response to volume expansion in patients with spontaneous respiratory movements be predicted?
Sarah Heenen1, Daniel De Backer, Jean-Louis Vincent
1Department of Intensive Care, Erasme University Hospital, Free University of Brussels, Route de Lennik, 808, B-1070 Brussels, Belgium. sheenen@ulb.ac.be

Introduction:
The aim of the study was to evaluate the ability of different static and dynamic measurements of preload to predict fluid responsiveness in patients with spontaneous respiratory movements.
Methods:
The subjects were 21 critically ill patients with spontaneous breathing movements receiving mechanical ventilation with pressure support mode (n = 9) or breathing through a face mask (n = 12), and who required a fluid challenge. Complete hemodynamic measurements, including pulmonary artery occluded pressure (PAOP), right atrial pressure (RAP), pulse pressure variation (DeltaPP) and inspiratory variation in RAP were obtained before and after fluid challenge. Fluid challenge consisted of boluses of either crystalloid or colloid until cardiac output reached a plateau. Receiver operating characteristics (ROC) curve analysis was used to evaluate the predictive value of the indices to the response to fluids, as defined by an increase in cardiac index of 15% or more.
Results:
Cardiac index increased from 3.0 (2.3 to 3.5) to 3.5 (3.0 to 3.9) l minute-1 m-2 (medians and 25th and 75th centiles), p < 0.05. At baseline, DeltaPP varied between 0% and 49%. There were no significant differences in DeltaPP, PAOP, RAP and inspiratory variation in RAP between fluid responders and non-responders. Fluid responsiveness was predicted better with static indices (ROC curve area +/- SD: 0.73 +/- 0.13 for PAOP, p < 0.05 vs DeltaPP and 0.69 +/- 0.12 for RAP, p = 0.054 compared with DeltaPP) than with dynamic indices of preload (0.40 +/- 0.13 for DeltaPP and 0.53 +/- 0.13 for inspiratory changes in RAP, p not significant compared with DeltaPP).
Conclusion:
In patients with spontaneous respiratory movements, DeltaPP and inspiratory changes in RAP failed to predict the response to volume expansion.
Related Concept Videos
 01:15
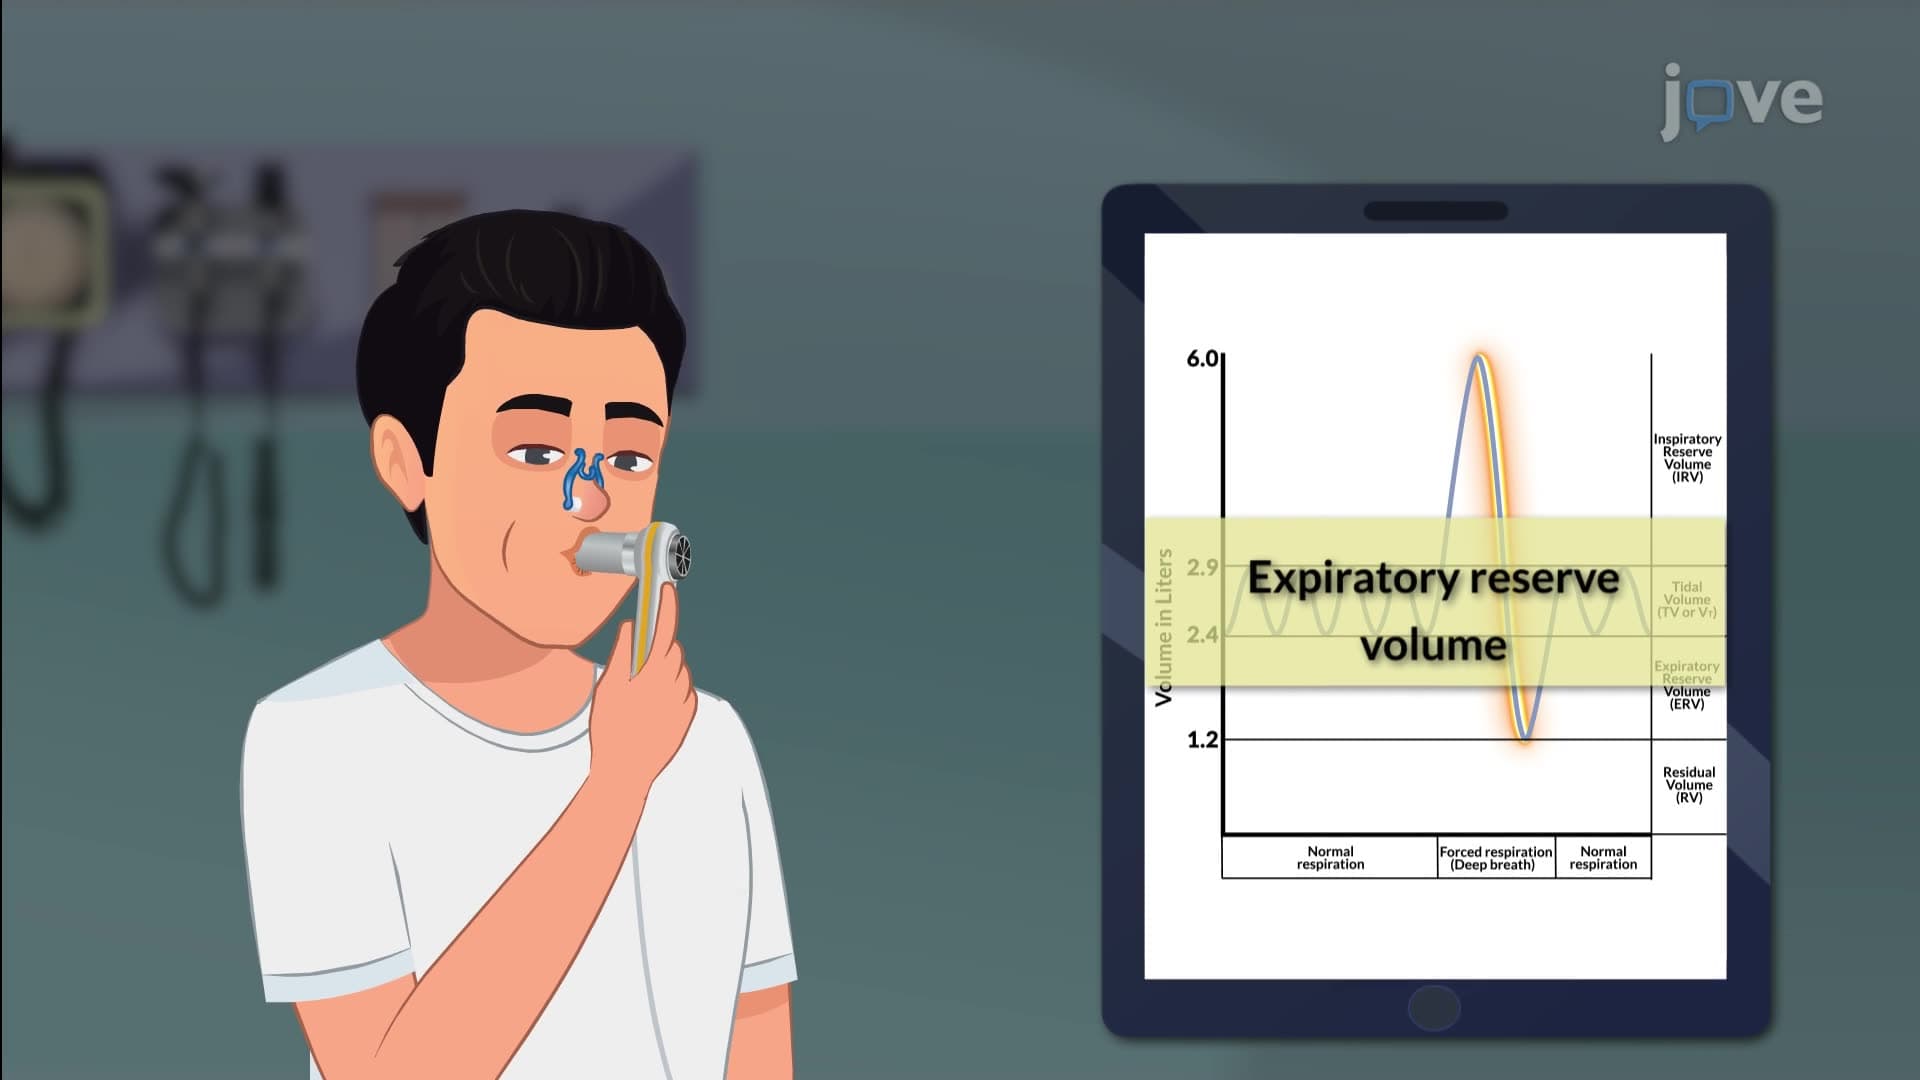
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:26
Respiratory Volumes and Capacities I
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:22
Respiratory Volumes and Capacities
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: