

Anorectal functions in patients with lumbosacral spinal cord injury
1Neuroscience Center and Department of Urology, Xiehe Hospital, Tongji Medical College, Huazhong University of Science and Technology, Wuhan 430022, China.

Objective:
To investigate the anorectal status in patients with lumbosacral spinal cord injury (SCI).
Methods:
Twenty six patients (23 males, 3 females) with lumbosacral SCI and 13 normal volunteers were enrolled into this study as controls. The median age was 43.7 years (ranging 17-68 years) and the median time of patients since injury was 59.1 months (ranging 8 months-15 years). They were diagnosed as complete lumbosacral SCI (n =2, American Spinal Injury Association (ASIA) score A), or incomplete lumbosacral SCI (n=24, ASIA score B-D) with mixed symptoms of constipation and/or fecal incontinence, and were studied by anorectal manometry. None of the patients had any medical treatments for neurogenic bowel prior to this study.
Results:
The maximum anal resting pressure in lumbosacral SCI patients group was slightly lower than that in control group (One-way ANOVA: P=0.939). During defecatory maneuvers, 23 of 26 (88.5%) patients with lumbosacral SCI and 1 of 13 (7.7%) in the control group showed pelvic floor dysfunction (PFD) (Fisher's exact test: P<0.0001). Rectoanal inhibitory reflex (RAIR) was identified in both patients with lumbosacral SCI and the controls. The rectal volume for sustained relaxation of the anal sphincter tone in lumbosacral SCI patients group was significantly higher than that in the control group (Independent-Samples t test: P<0.0001). The mean rectal volume to generate the first sensation was 92.7 ml+/-57.1 ml in SCI patients, 41.5 ml+/-13.4 ml in the control group (Independent-Samples t test: P<0.0001).
Conclusions:
Most of the patients with lumbosacral SCI show PFD during defecatory maneuvers and their rectal sensation functions are severely damaged. Some patients exhibit abnormal cough reflex. Anorectal manometry may be helpful to find the unidentified supraconal lesions. RAIR may be modulated by central nervous system (CNS).

Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:21
Spinal Nerves: Plexus II
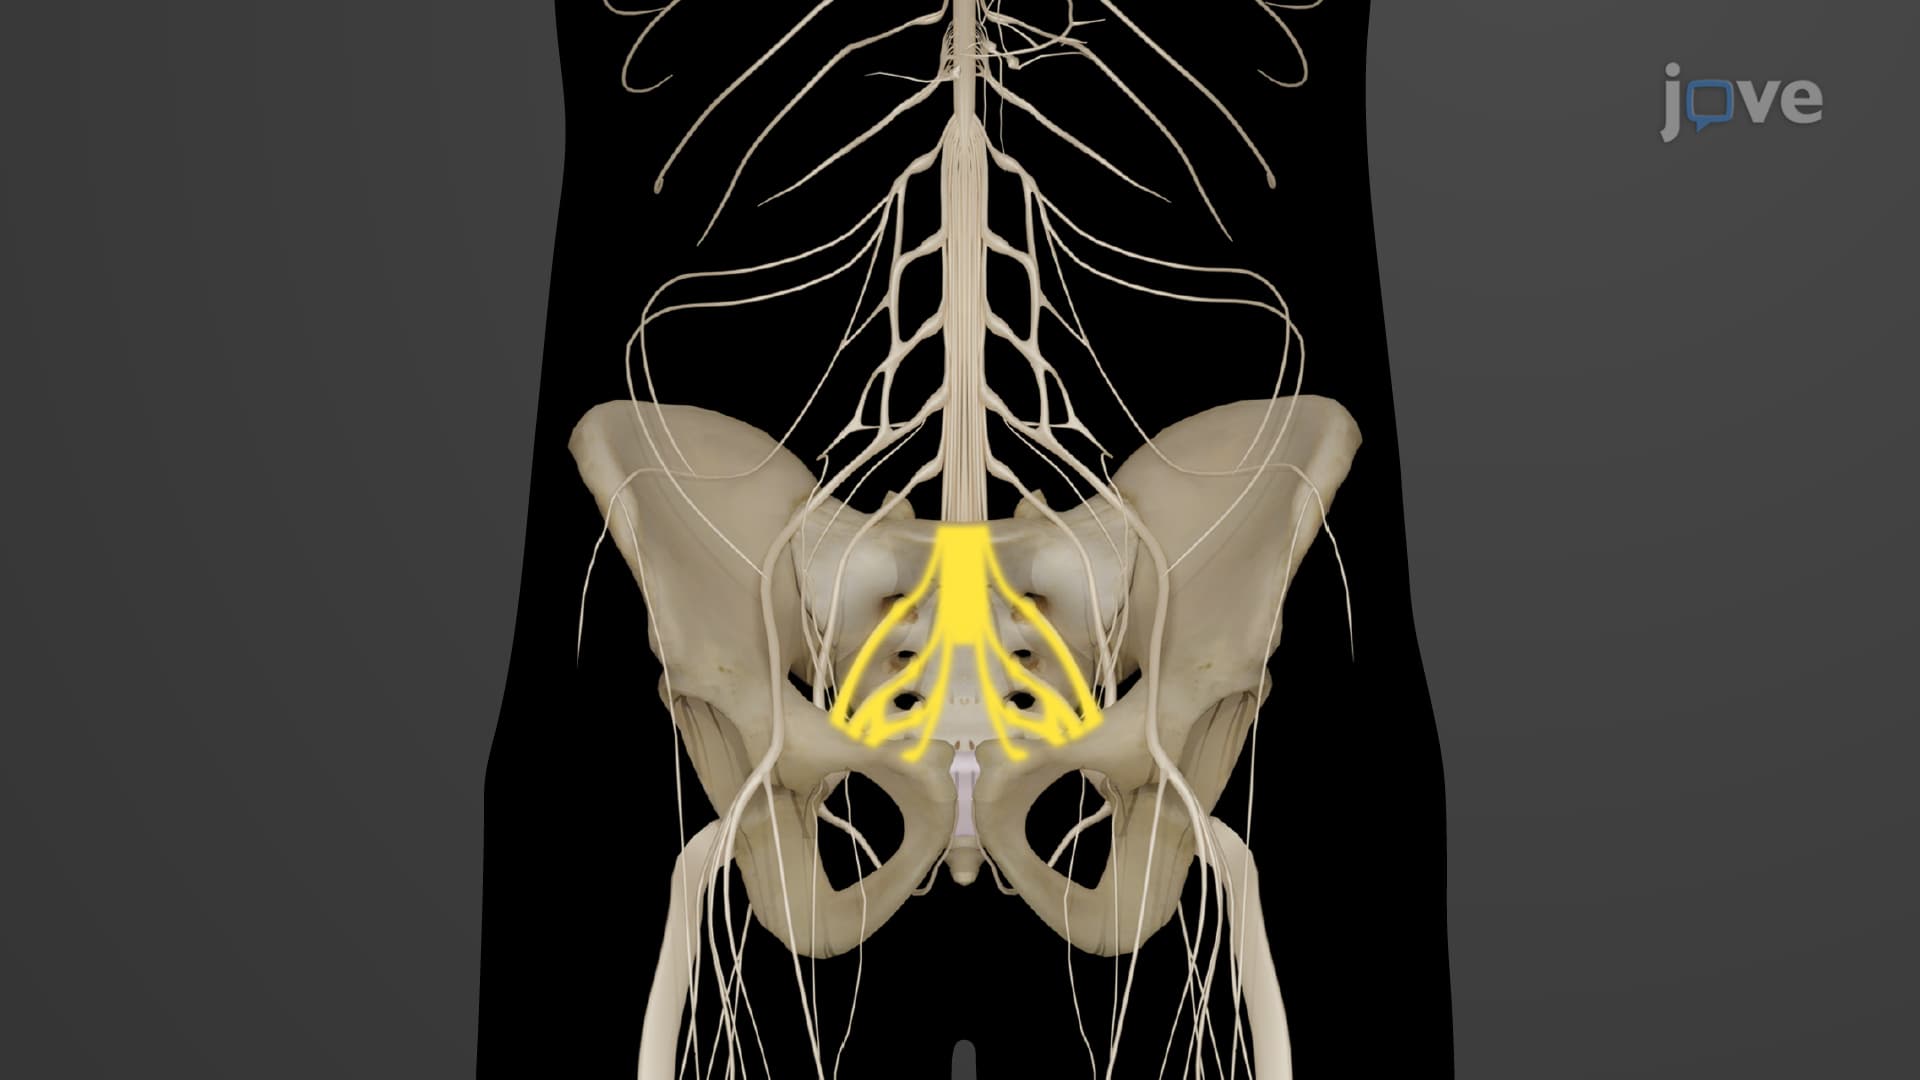
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:29
Herniated Intervertebral Disc l: Introduction
 01:23
Spinal Nerves: Anatomy
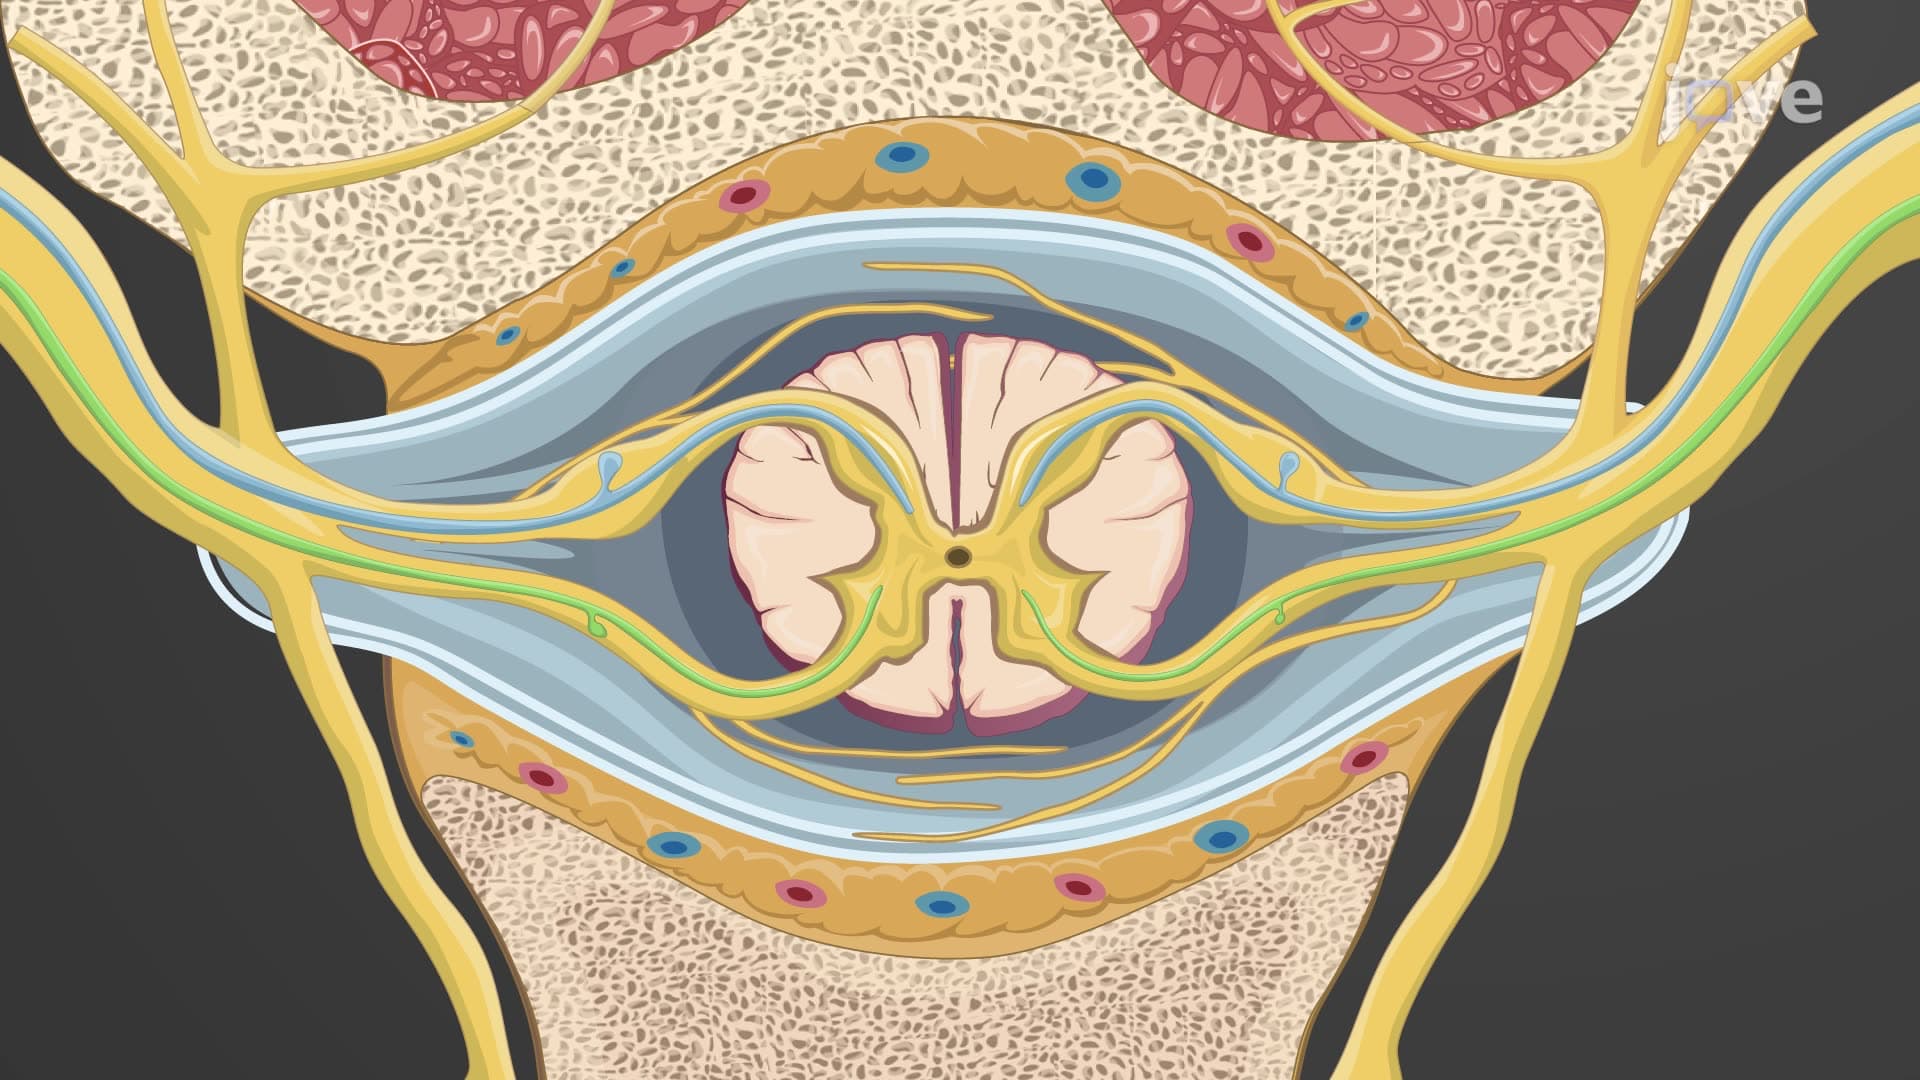
There are 31 bilateral pairs of spinal nerves, each emerging from the spinal cord through the intervertebral foramina—openings between adjacent vertebrae. These nerves are...