Related Experiment Video
Updated: Aug 6, 2026
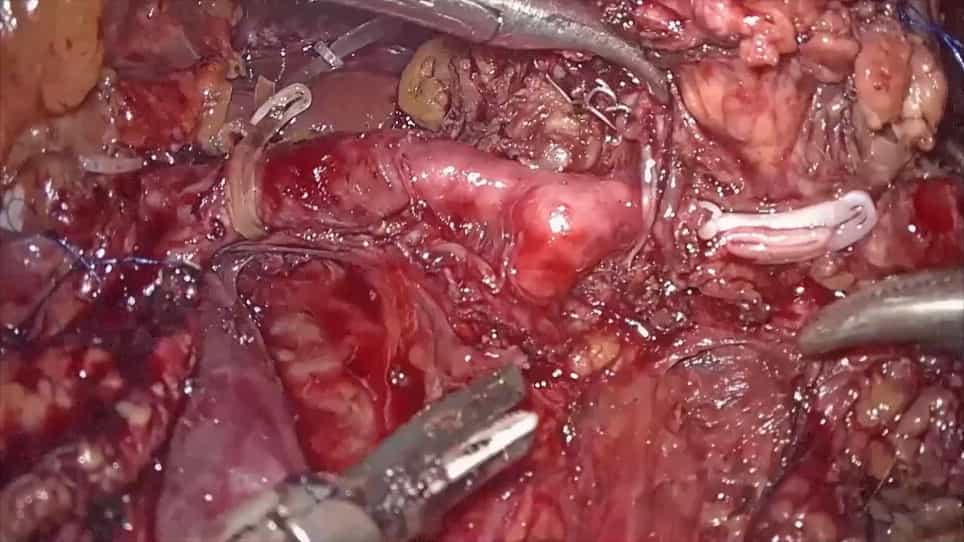
Laparoscopic Radical Antegrade Modular Pancreatosplenectomy via Dorsal-Caudal Artery Approach for Pancreatic Neck-Body Cancer
Published on: November 18, 2022
Borderline resectable pancreatic cancer: definitions, management, and role of preoperative therapy
Gauri R Varadhachary1, Eric P Tamm, James L Abbruzzese
1Department of Gastrointestinal Medical Oncology, Unit 426, The University of Texas M. D. Anderson Cancer Center, 1515 Holcombe Boulevard, Houston, Texas 77030, USA. gvaradha@mdanderson.org

Abstract:
With recent advances in pancreatic imaging and surgical techniques, a distinct subset of pancreatic tumors is emerging that blurs the distinction between resectable and locally advanced disease: tumors of "borderline resectability." In our practice, patients with borderline-resectable pancreatic cancer include those whose tumors exhibit encasement of a short segment of the hepatic artery, without evidence of tumor extension to the celiac axis, that is amenable to resection and reconstruction; tumor abutment of the superior mesenteric artery involving <180 degrees of the circumference of the artery; or short-segment occlusion of the superior mesenteric vein, portal vein, or their confluence with a suitable option available for vascular reconstruction because the veins are normal above and below the area of tumor involvement. With currently available surgical techniques, patients with borderline-resectable pancreatic head cancer are at high risk for a margin-positive resection. Therefore, our approach to these patients is to use preoperative systemic therapy and local-regional chemoradiation to maximize the potential for an R0 resection and to avoid R2 resections. In our experience, patients with favorable responses to preoperative therapy (radiographical evidence of tumor regression and improvement in serum tumor marker levels) are the subset of patients who have the best chance for an R0 resection and a favorable long-term outcome.
