Related Experiment Video
Updated: Jul 22, 2026

Do's and Don'ts in the Preparation of Muscle Cryosections for Histological Analysis
Published on: May 15, 2015
What more can we learn from muscle histopathology in children with dermatomyositis/polymyositis?
J C Wargula1, D J Lovell, M H Passo
1William S. Rowe Division of Rheumatology, University of Cincinnati College of Medicine, Children's Hospital Medical Center, OH, USA. j.wargula@att.net

Insights
Direct immunofluorescence arterial staining and infarct on muscle biopsy are linked to chronic ulcerative disease in juvenile idiopathic inflammatory myopathies. These findings in juvenile dermatomyositis (JDM) and juvenile polymyositis (JPM) may guide early treatment.
Area of Science:
- Pediatric Rheumatology
- Muscle Pathology
- Autoimmune Diseases
Background:
- Juvenile idiopathic inflammatory myopathies, including juvenile dermatomyositis (JDM) and juvenile polymyositis (JPM), present with diverse clinical courses and complications.
- Understanding the histopathological correlates of disease progression is crucial for effective management in pediatric patients.
Purpose of the Study:
- To investigate the correlation between specific muscle biopsy findings and the disease course and complications in children with JDM and JPM.
- To identify histopathological markers that predict severe disease outcomes in juvenile idiopathic inflammatory myopathies.
Main Methods:
- Retrospective cohort analysis of 59 children diagnosed with JDM or JPM between 1965 and 1998.
- Evaluation of muscle biopsy features including capillary loss, infarct, perifascicular myopathy, and direct immunofluorescence (DIF) staining patterns.
- Correlation of histopathological findings with clinical disease course (limited, chronic non-ulcerative, chronic ulcerative) and complications (calcinosis, contractures, ulcerations, death).
Main Results:
- Direct immunofluorescence (DIF) staining localized to intramuscular arteries, but not capillaries, was significantly associated with chronic ulcerative disease (69% vs. 8-32%, p<0.001).
- Infarct on muscle biopsy was significantly associated with chronic ulcerative disease (23% vs. 0-4%, p=0.02) and correlated with gastrointestinal ulceration and death.
- Loss of intramuscular capillaries and perifascicular myopathy did not significantly correlate with disease course or complications.
Conclusions:
- Direct immunofluorescence arterial staining and infarct on muscle biopsy are significant predictors of chronic ulcerative disease in JDM and JPM.
- These findings suggest that the presence of DIF-arterial staining and infarct on biopsy may warrant early consideration of aggressive therapeutic strategies.
- Perifascicular myopathy and capillary network loss are not associated with disease course in these juvenile idiopathic inflammatory myopathies.
Objective:
To correlate disease course and complications in children with juvenile dermatomyositis (JDM) and polymyositis (JPM) with specific features of muscle pathology on biopsy.
Methods:
This is a retrospective cohort analysis of 59 children diagnosed with JDM or JPM between 1965 and 1998 and followed at the Cincinnati Children's Hospital Medical Center (CCHMC) for a mean duration of 7.3 years (range 1.1-24.5 years). Disease course was characterized as limited, chronic non-ulcerative or chronic ulcerative, similar to previously defined disease course subtypes reported by Crowe et al.(1). All subjects had diagnostic muscle biopsies performed at CCHMC and had disease for at least two years' duration in order to classify their disease course as either limited or chronic. Features of muscle histopathology that were evaluated included loss of the intramuscular capillary bed, infarct, perifascicular myopathy, direct immunofluorescence (DIF) staining of the intramuscular vasculature and specifically, the locale of DIF staining, i.e., small arteries or capillaries. Disease complications that were assessed included calcinosis, contractures, muscle atrophy, lipodystrophy, gastrointestinal ulceration, cutaneous ulceration and death. Data analysis was completed using Chi-square or Fisher's exact tests and logistic regression modeling.
Results:
Twenty-two children (37%) had limited disease, 24 (41%) had chronic non-ulcerative disease and 13 (22%) had chronic ulcerative disease. Neither loss of the intramuscular capillary bed nor perifascicular myopathy on muscle biopsy significantly correlated with disease course or the various complications evaluated in this study. DIF staining of intramuscular vessels overall was not significantly associated with clinical disease course, but the localization of DIF staining to intramuscular arteries (rather than to capillaries) was significantly associated with the outcome of chronic ulcerative disease. Nine of the 13 children with chronic ulcerative disease had DIF-arterial staining on muscle biopsy (69%), significantly greater than DIF-arterial staining in children with limited disease (32% had DIF-arterial staining) (p = 0.04), chronic non-ulcerative disease (8% had DIF-arterial staining) (p = 0.0002), and non-ulcerative disease overall (limited + chronic non-ulcerative disease groups combined) (20% had DIF-arterial staining), with p = 0.001. Additionally, lack of DIF-arterial staining on biopsy was significantly correlated with patients not having gastrointestinal ulceration (p = 0.002), cutaneous ulceration (p = 0.004) and/or death (p = 0.02) as disease-related complications. Infarct on muscle biopsy was significantly associated with the development of chronic ulcerative disease (p = 0.02), being present on biopsy in 23% of children with chronic ulcerative disease compared with none of the patients with chronic non-ulcerative disease and 4% of those with limited disease. Infarct on muscle biopsy correlated with the outcomes of death (p = 0.01) and gastrointestinal ulceration (p = 0.03), but not with the development of cutaneous ulceration (p = 0.18).
Conclusion:
DIF-arterial staining and infarct on muscle biopsy are significantly associated with the development of chronic ulcerative disease in JDM and JPM, while perifascicular myopathy and loss of the intramuscular capillary network are not associated with disease course. The presence of DIF-arterial staining and infarct on biopsy should suggest early use of second-line therapeutic agents to more quickly bring disease activity under control.
Related Concept Videos
 01:21
Satellite Stem Cells and Muscular Dystrophy
 01:25
Overview of Muscle Tissues
Elasticity
Elasticity is the ability of muscles to stretch and return to their original shape. This property is partly due to elastic fibers — macromolecules that run through the muscles. These fibers are firm and resilient,...
 01:13
Microscopic Anatomy of Skeletal Muscles
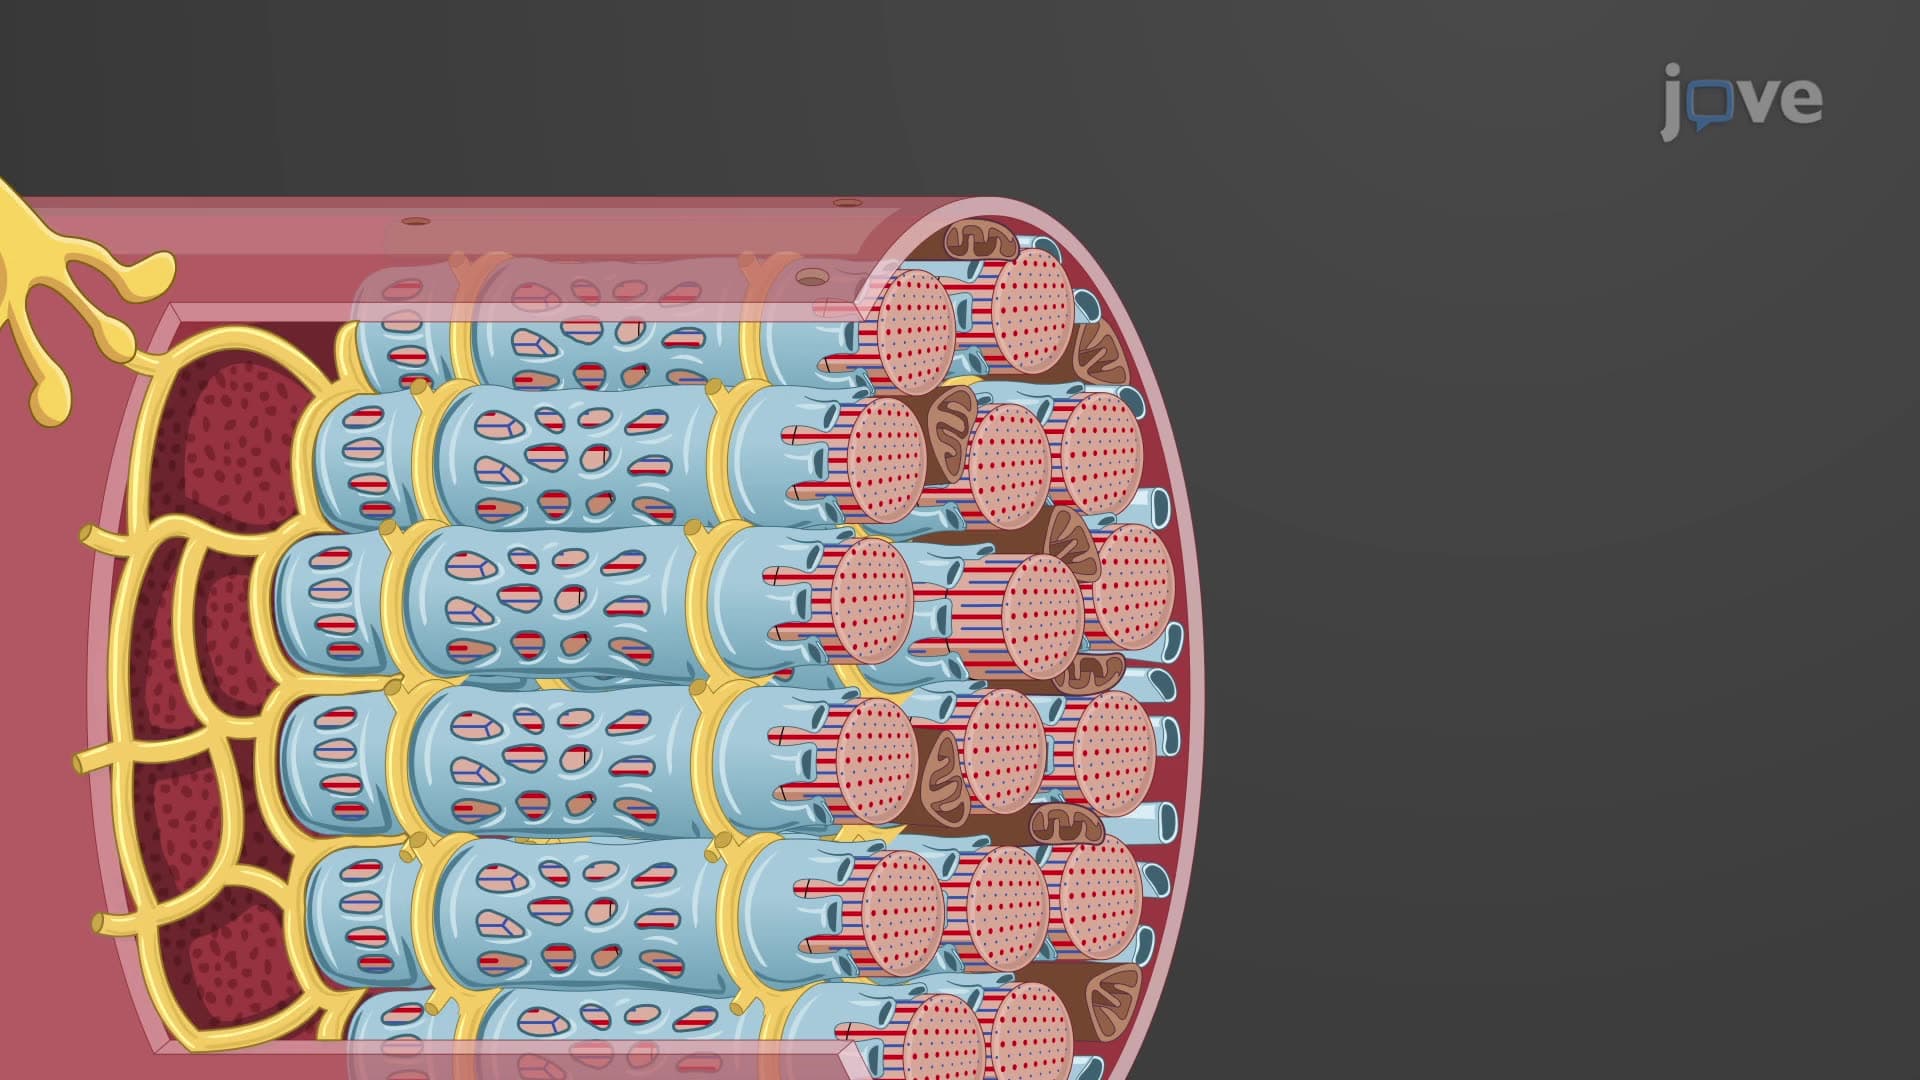
The muscle sarcolemma is a plasma membrane enclosing each muscle cell that conducts electrical signals called action potentials. The sarcolemma extends into the cell to form T-tubules, ensuring the neural impulses are uniformly distributed across the entire muscle...
 01:28
Disorders of the Skeletal Muscle
Musculoskeletal disorders
Musculoskeletal disorders involve injuries and conditions affecting the skeletal muscles and associated connective tissues. These disorders can arise from acute biomechanical stresses or chronic overuse and can occur across different age groups. Common injuries include sprains, fractures, and muscular strains, often resulting from...
 01:21
Myocarditis I: Introduction
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests