Related Experiment Video
Updated: Aug 6, 2026

Study of In Vivo Glucose Metabolism in High-fat Diet-fed Mice Using Oral Glucose Tolerance Test (OGTT) and Insulin Tolerance Test (ITT)
Published on: January 7, 2018
Different mechanisms for impaired fasting glucose and impaired postprandial glucose tolerance in humans
Christian Meyer1, Walkyria Pimenta, Hans J Woerle
1Department of Endocrinology, Carl T. Hayden VA Medical Center, Phoenix, AZ 85012, USA. christian.meyer@med.a.gov

Objective:
To compare the pathophysiology of impaired fasting glucose (IFG) and impaired glucose tolerance (IGT) in a more comprehensive and standardized fashion than has hitherto been done.
Research Design And Methods:
We studied 21 individuals with isolated IFG (IFG/normal glucose tolerance [NGT]), 61 individuals with isolated IGT (normal fasting glucose [NFG]/IGT), and 240 healthy control subjects (NFG/NGT) by hyperglycemic clamps to determine first- and second-phase insulin release and insulin sensitivity. Homeostasis model assessment (HOMA) indexes of beta-cell function (HOMA-%B) and insulin resistance (HOMA-IR) were calculated from fasting plasma insulin and glucose concentrations.
Results:
Compared with NFG/NGT, IFG/NGT had similar fasting insulin concentrations despite hyperglycemia; therefore, HOMA-IR was increased approximately 30% (P < 0.05), but clamp-determined insulin sensitivity was normal (P > 0.8). HOMA-%B and first-phase insulin responses were reduced approximately 35% (P < 0.002) and approximately 30% (P < 0.02), respectively, but second-phase insulin responses were normal (P > 0.5). NFG/IGT had normal HOMA-IR but approximately 15% decreased clamp-determined insulin sensitivity (P < 0.03). Furthermore, HOMA-%B was normal but both first-phase (P < 0.0003) and second-phase (P < 0.0001) insulin responses were reduced approximately 30%. IFG/NGT differed from NFG/IGT by having approximately 40% lower HOMA-%B (P < 0.012) and approximately 50% greater second-phase insulin responses (P < 0.005).
Conclusions:
Since first-phase insulin responses were similarly reduced in IFG/NGT and NFG/IGT, we conclude that IFG is due to impaired basal insulin secretion and preferential resistance of glucose production to suppression by insulin, as reflected by fasting hyperglycemia despite normal plasma insulin concentrations and increased HOMA-IR, whereas IGT mainly results from reduced second-phase insulin release and peripheral insulin resistance, as reflected by reduced clamp-determined insulin sensitivity.
More Related Videos
 08:30
Intraperitoneal Glucose Tolerance Test, Measurement of Lung Function, and Fixation of the Lung to Study the Impact of Obesity and Impaired Metabolism on Pulmonary Outcomes
Published on: March 15, 2018
 08:03
Glucose Uptake Measurement and Response to Insulin Stimulation in In Vitro Cultured Human Primary Myotubes
Published on: June 25, 2017
Related Concept Videos
 01:24
Type II Diabetes II: Pathophysiology
 01:02
Glucose Homeostasis: Regulation of Blood Glucose
During fasting, when blood glucose levels are low, the pancreas secretes glucagon. it...
 01:15
Hypoglycemia and Glucagon
 01:29
Hyperglycemia
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...
 01:18
Metabolic States of the Body: The Postabsorptive State
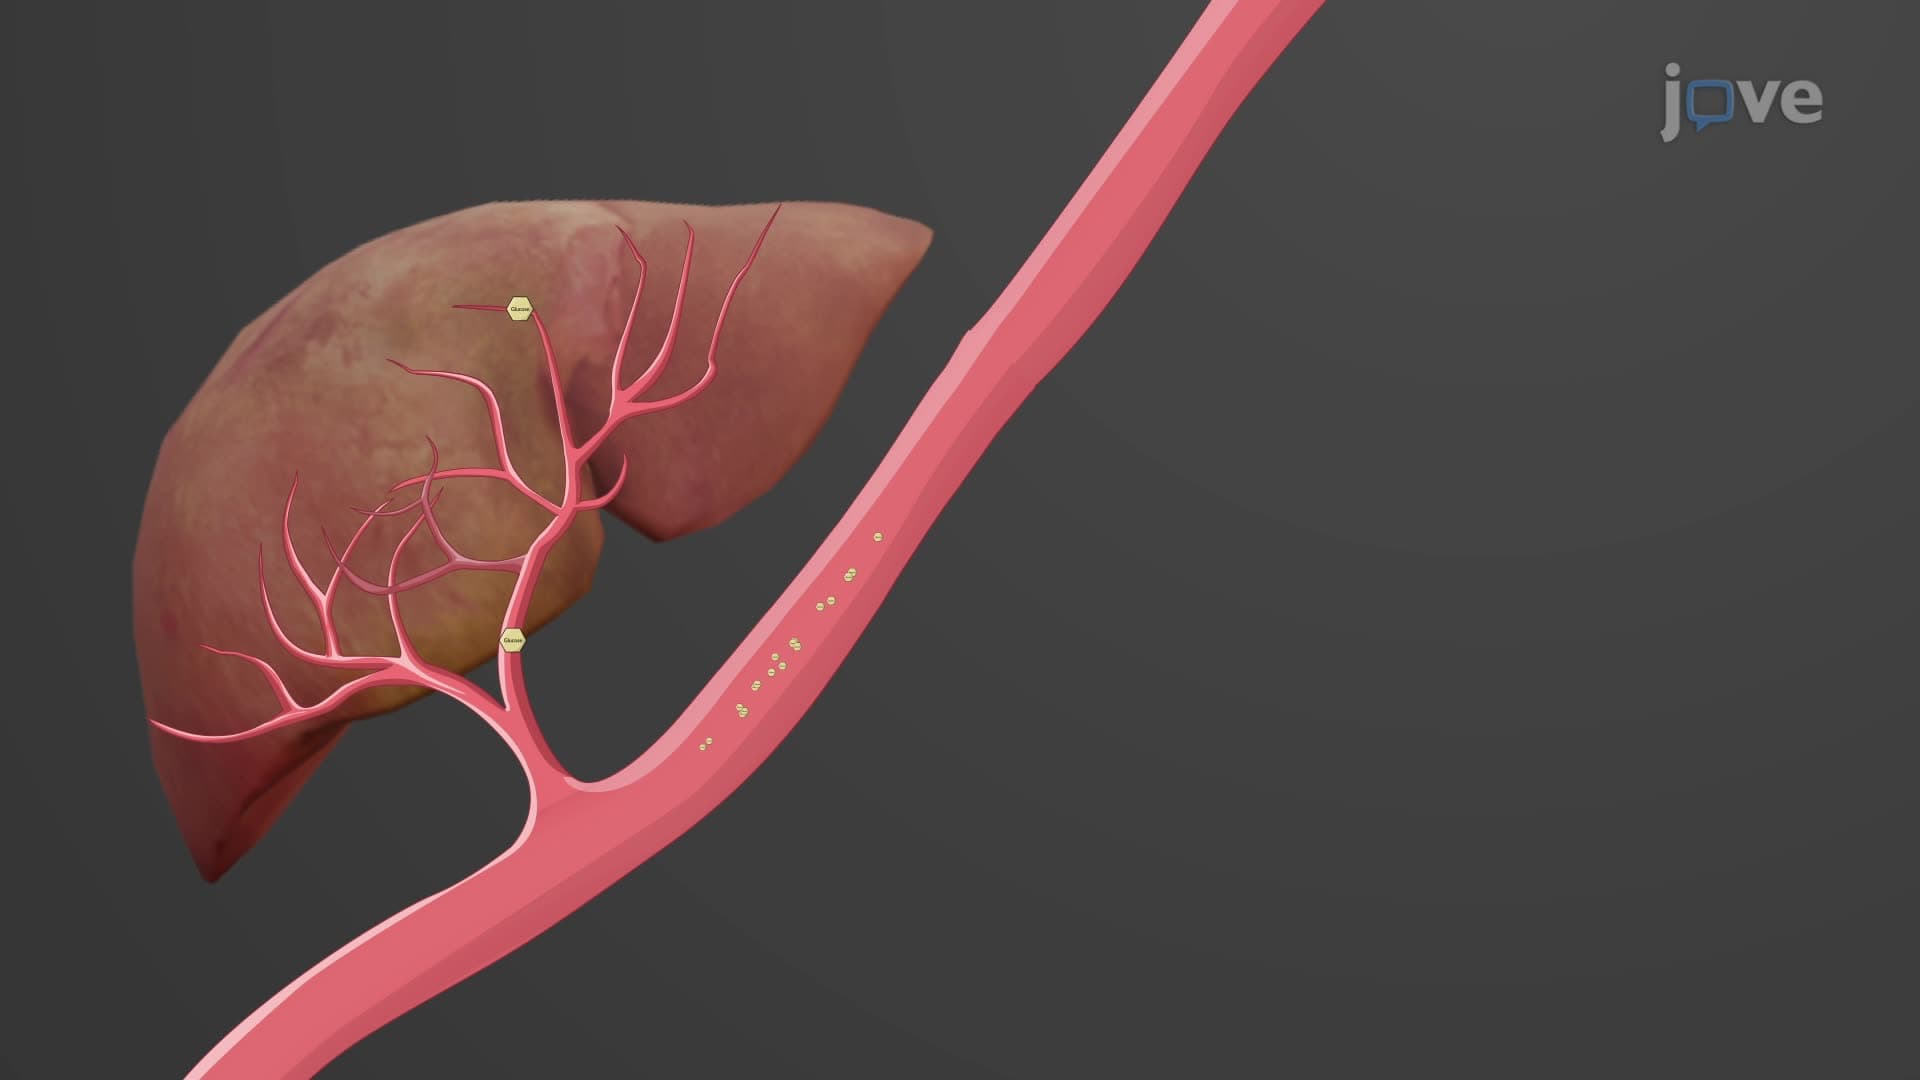
Initially, glycogen stored in the liver is broken down to release glucose into the bloodstream, while glycogen in the muscles is broken down to supply glucose for energy directly within the muscle cells. As glycogen stores diminish,...