

Refractory ventricular tachycardia secondary to cardiac sarcoid: electrophysiologic characteristics, mapping, and
Bruce A Koplan1, Kyoko Soejima, Kenneth Baughman
1Cardiac Arrhythmia Service, Brigham and Women's Hospital, Boston, Massachusetts 02115, USA. bkoplan@partners.org

Background:
Cardiac sarcoidosis is a recognized cause of ventricular tachycardia (VT) and sudden death that has not been well studied.
Objectives:
The purpose of this study was to describe the clinical characteristics of a consecutive series of eight patients with recurrent monomorphic VT due to cardiac sarcoidosis and to define the electrophysiologic characteristics of the VT and its electrophysiologic substrate.
Methods/Results:
Of 98 patents with nonischemic cardiomyopathy and VT referred for ablation over a 7-year period, sarcoid was the etiology in 8%. Mean age was 42 +/- 8 years, and all but one patient had a reduced left ventricular ejection fraction (mean 34% +/- 15%). VT was the initial manifestation of sarcoid disease in 5 of 8 cases based on retrospective analysis. All patients had not responded to therapy with multiple antiarrhythmic drugs (mean 2.5 +/- 1). Cardiac biopsy initially was negative in 3 of 7 patients, and in 2 patients the diagnosis was not made until posttransplant examination of the heart. Two patients (25%) had a previous presumptive diagnosis of arrhythmogenic right ventricular dysplasia. Electrophysiologic study revealed evidence of scar-related reentry with multiple monomorphic VTs induced (4 +/- 2 VTs per patient) with both right bundle branch block and left bundle branch block QRS configurations. Areas of low-voltage scar were present in the right ventricle in all 8 of 8 patients, in the left ventricle in 5 (63%) of 8 patients, and in the epicardium in 2 patients undergoing epicardial mapping. Ablation abolished one or more VTs in 6 (75%) of 8 patients, but other VTs remained inducible in all but one patient. Postablation, some form of sustained VT recurred in 6 of 8 patients within 6 months. However, at longer follow-up (range 6 months to 7 years), 4 of 8 patients currently are free of VT with antiarrhythmic drugs and immunosuppression. Cardiac transplantation eventually was required in 5 of 8 patients because of either recurrent VT (n = 4) or heart failure (n = 1).
Conclusion:
Sarcoid is an important diagnostic consideration in scar-related VT. Sarcoid can be misdiagnosed as idiopathic or arrhythmogenic right ventricular cardiomyopathy. Arrhythmia control can be difficult, although ablation can be helpful in some patients.

Related Concept Videos
 01:29
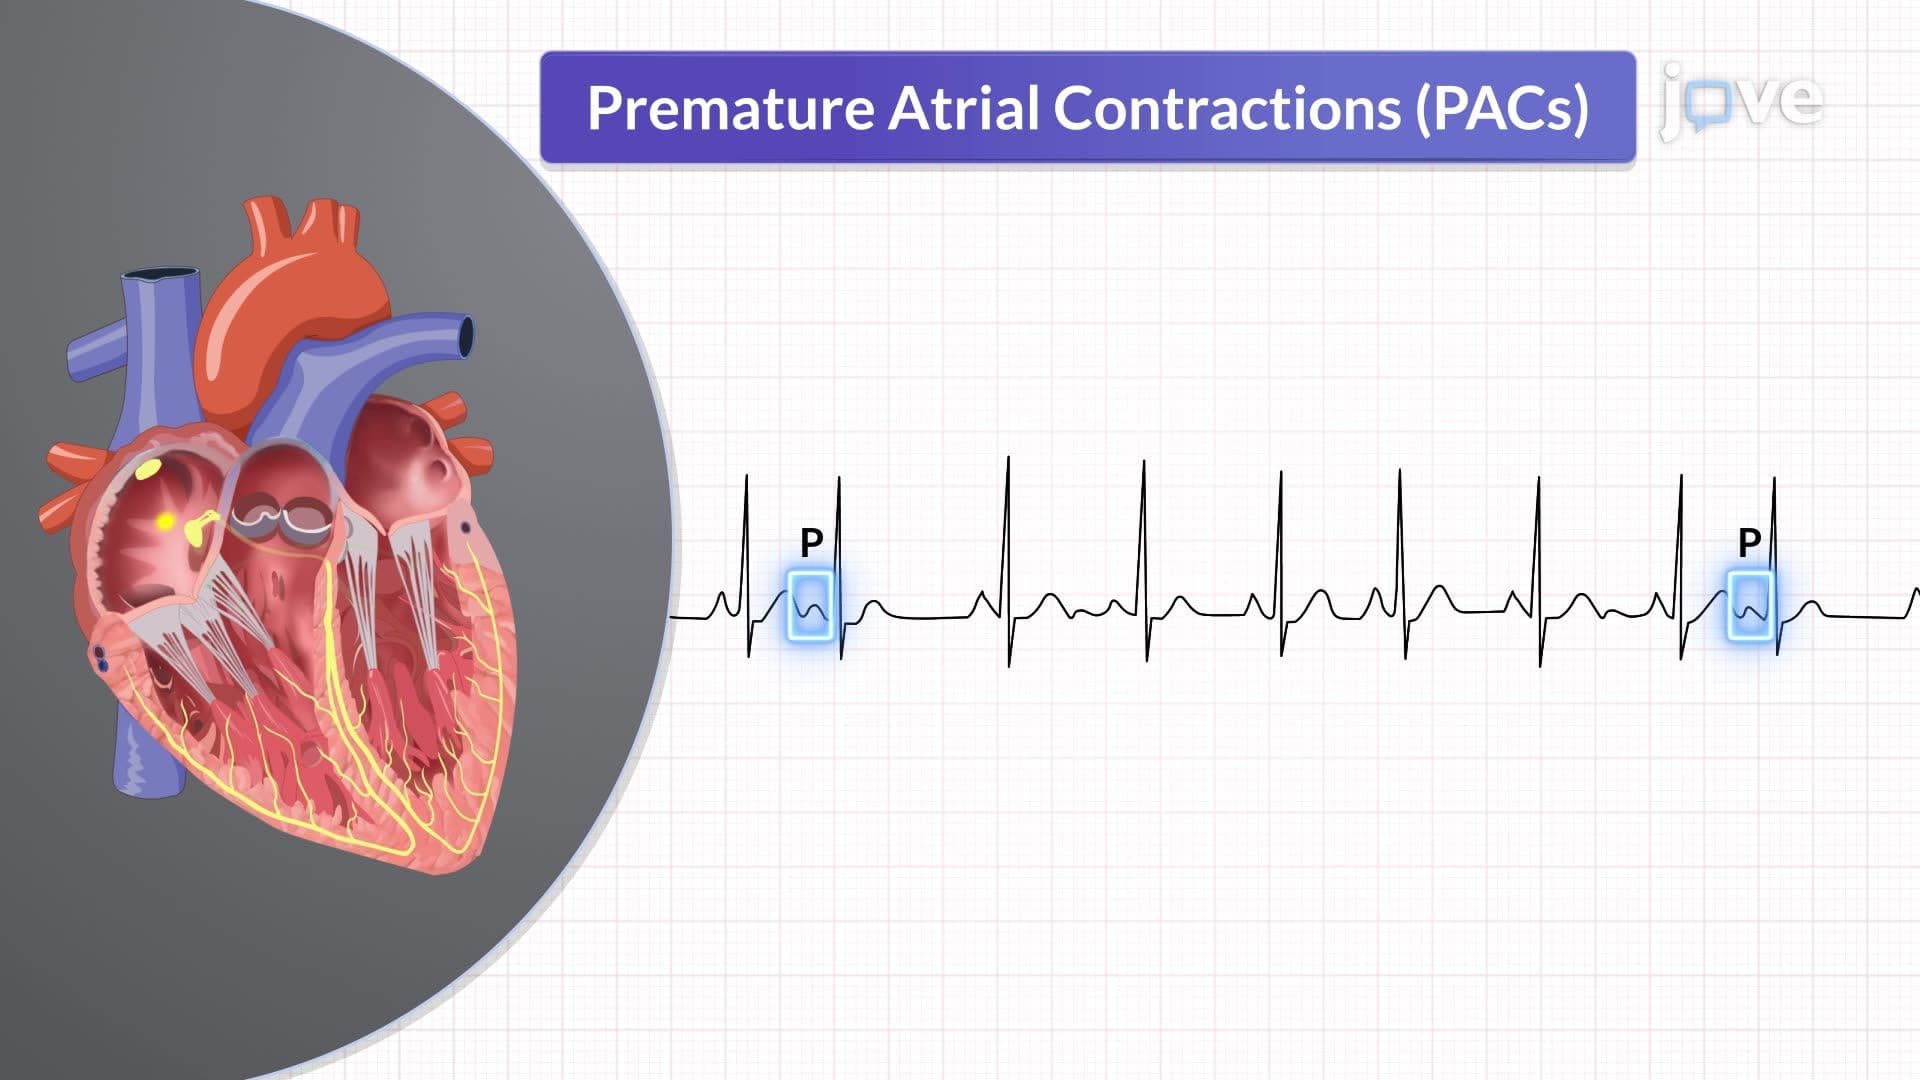
Dysrhythmias III: Characteristics of Dysrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:30
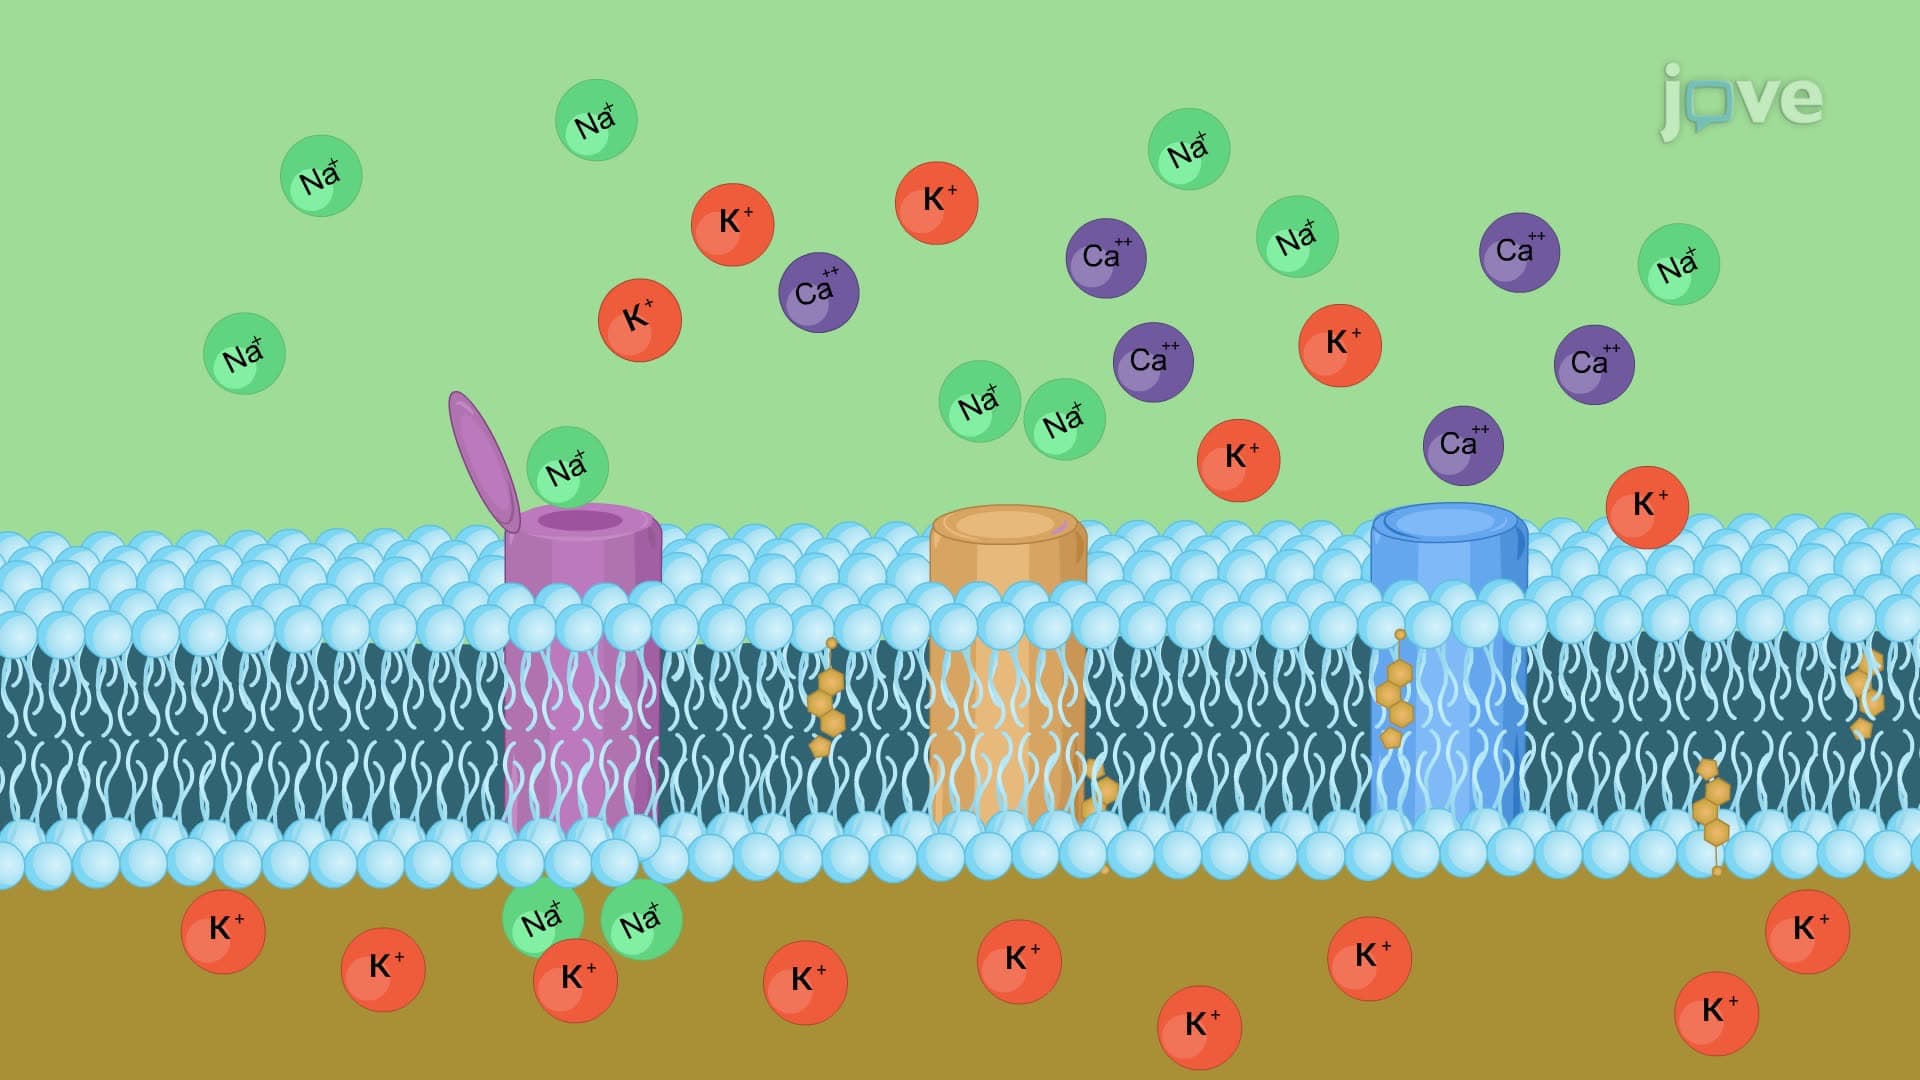
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:28
Mechanism of Cardiac Arrhythmias
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...