Related Experiment Video
Updated: Aug 6, 2026


Ultrasonography of the Adult Male Urinary Tract for Urinary Functional Testing
Published on: August 14, 2019
Management of benign prostate hyperplasia: an overview of alpha-adrenergic antagonist
Gopal Garg1, Deependra Singh, Swarnlata Saraf
1Institute of Pharmacy, Pt. Ravishankar Shukla University, India. rsofiop_gg@rediffmail.com

Abstract:
Benign prostate hyperplasia (BPH) is common among above 50 years age group, interfere with normal activities of lower urinary tract function and reduce the sense of well being. It can also be progressive, with a lost of urinary retention, bladder infection, bladder calculus and renal failure. Although many men with mild to moderate symptoms to well without therapy, others have gradually increasing symptoms and require medical therapy or surgery. BPH is the non-malignant, uncontrolled growth of cells in the prostate gland. This cell growth usually occurs in the tissue that surrounds the urethra as it passes through the prostate gland to the bladder. As BPH progresses, the gland constricts the urethra and obstructs the urine outflow. The bladder no longer empties completely, creating an environment in which infections, bladder stones, and chronic prostatities may develop. If left untreated, chronic obstruction can lead to the back up of urine into the ureters and compromise kidney function. In hyperplastic prostate tissue, the prostate capsule, and the bladder neck are blocked, by using alpha-adrenergic antagonist drugs; the smooth muscle tone of these structures is decreased. As a result, resistance to urinary flow through the bladder neck and the prostatic urethra decreases and urinary flow increases. A variety of alpha-adrenergic antagonists with distinct properties have been investigated as possible treatments for benign prostate hyperplasia.

Related Concept Videos
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:17
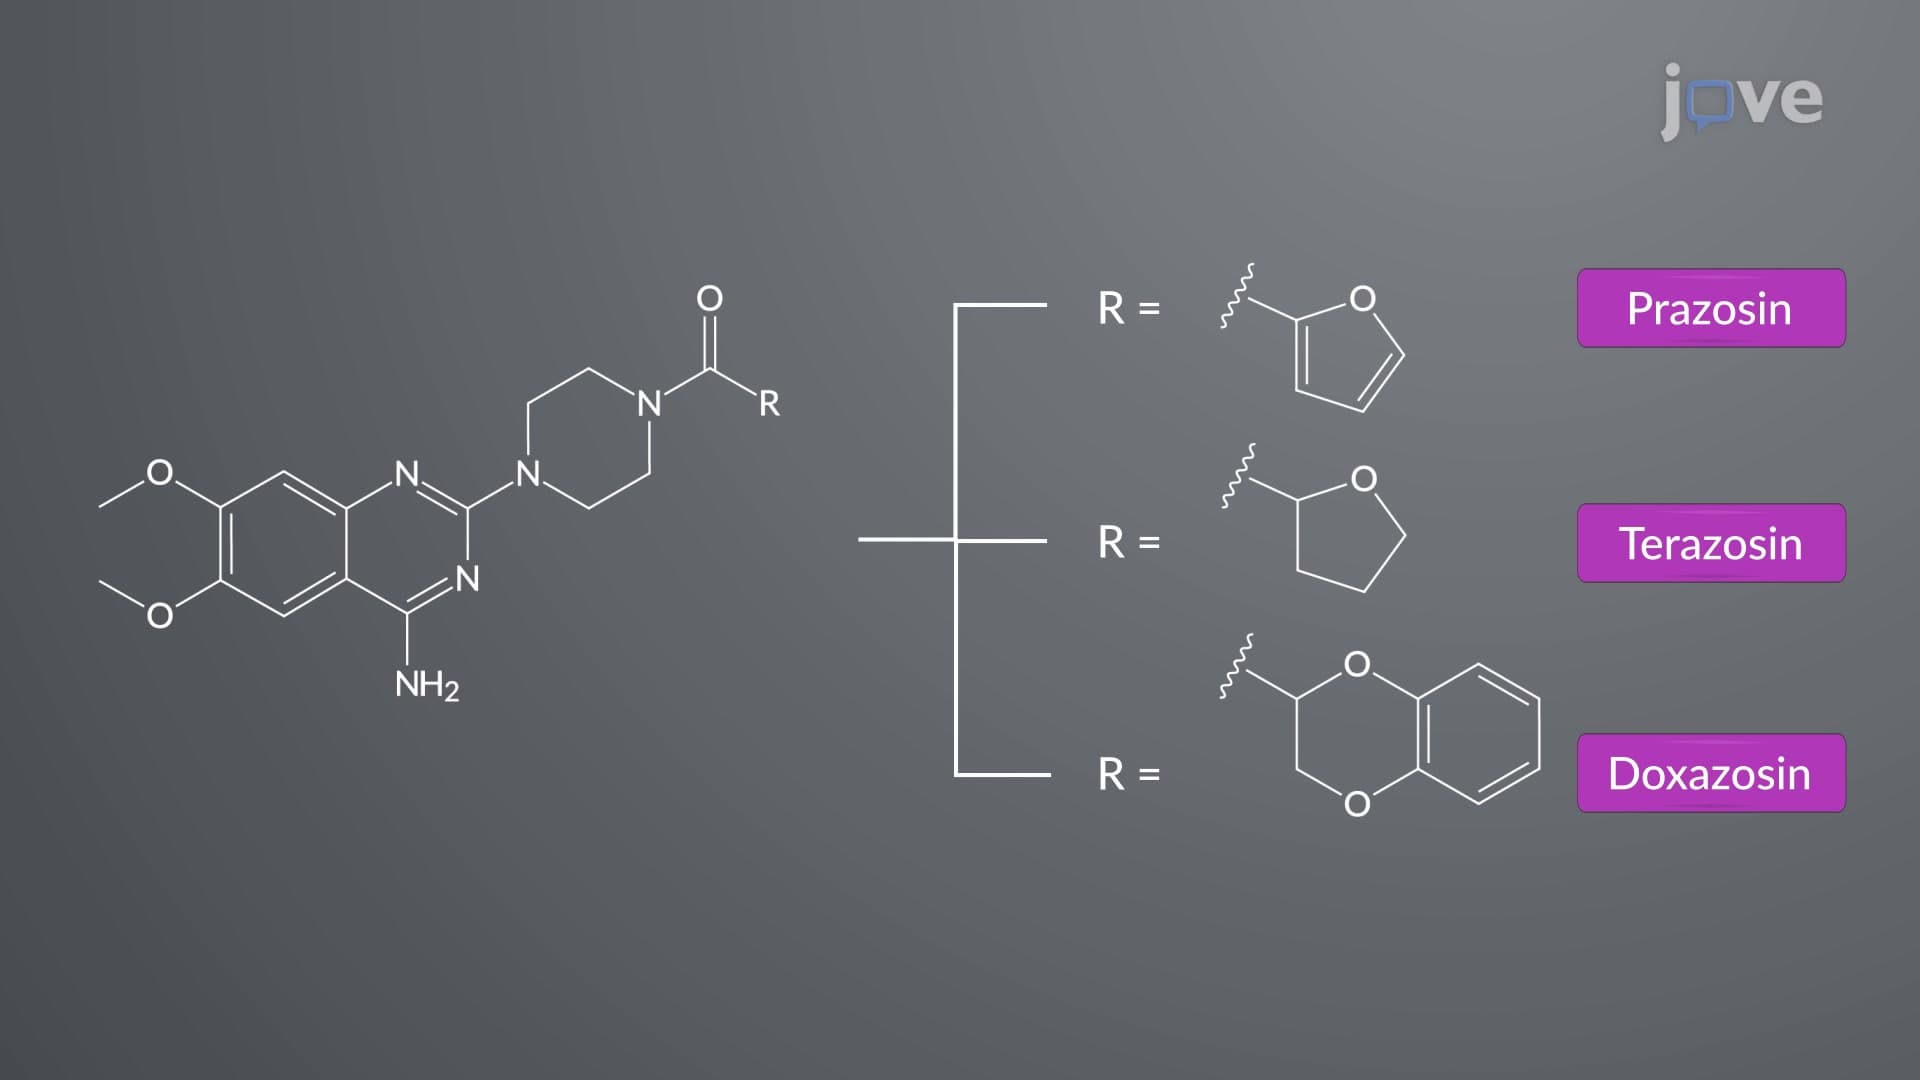
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:31
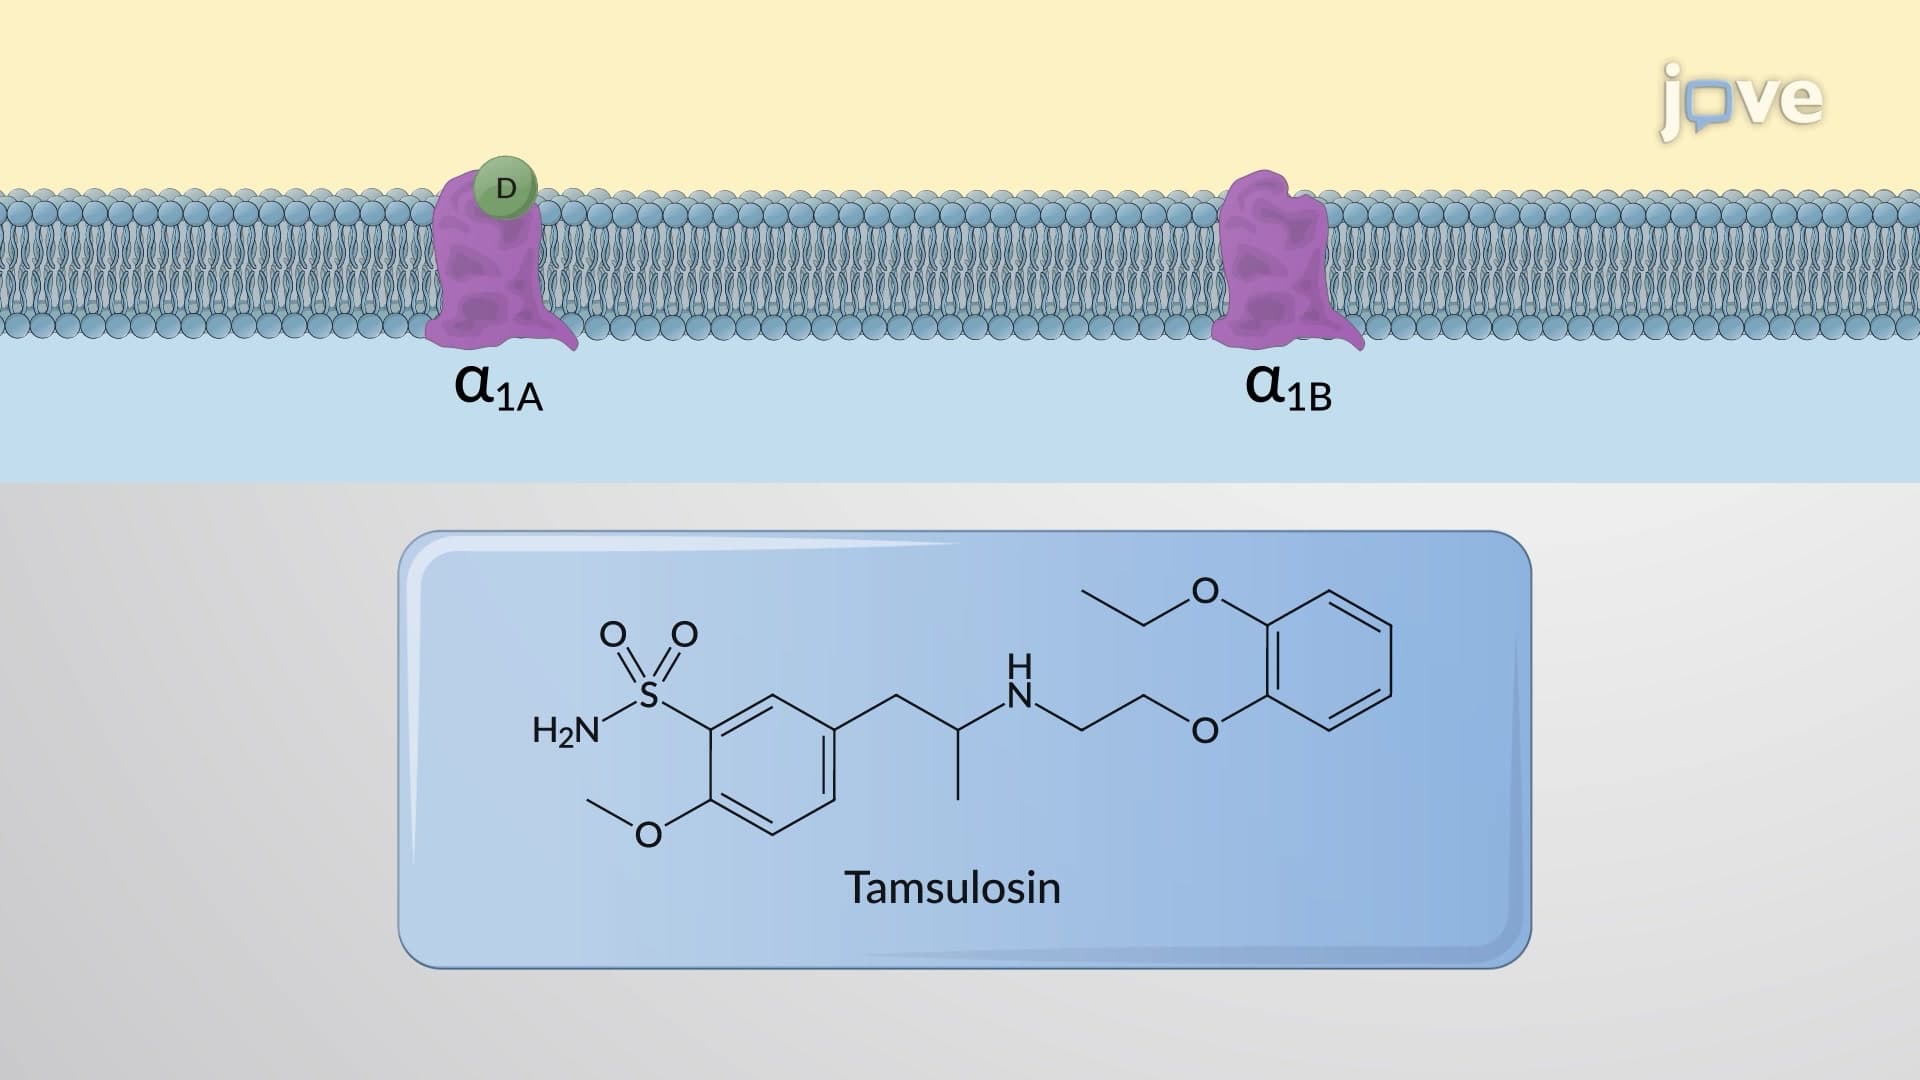
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers