Related Experiment Video
Updated: Aug 6, 2026
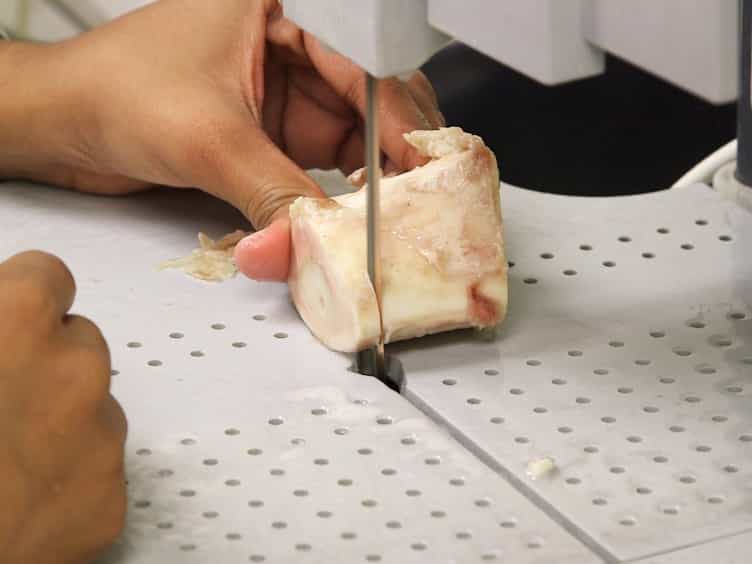

Fragility Assessment of Bovine Cortical Bone Using Scratch Tests
Published on: November 30, 2017
Bone fragility in men--where are we?

Insights
Further research is needed to understand bone fragility in men. Many aspects of fracture epidemiology, pathogenesis, and treatment require more investigation to improve patient outcomes.
Area of Science:
- Gerontology
- Orthopedics
- Endocrinology
Background:
- Advances in understanding male osteoporosis have been made, but significant challenges persist.
- The epidemiology of non-vertebral fractures in men is less defined than hip fractures, despite their substantial contribution to the global fracture burden.
- Most fragility fractures in men occur in individuals without a diagnosis of osteoporosis, highlighting an unmet clinical challenge.
Purpose of the Study:
- To summarize current knowledge and identify research gaps in the epidemiology, pathogenesis, and treatment of bone fragility in men.
- To reassess established notions regarding age-related bone loss in men compared to women.
- To highlight the need for further investigation into the role of sex hormones and the growth hormone/IGF-1 axis in bone health.
Main Methods:
- Review of proceedings from the Third International Osteoporosis in Men meeting (Genoa, May 2005).
- Analysis of epidemiological data on vertebral and non-vertebral fractures in men.
- Discussion of existing research on bone mineral density (BMD), fracture risk, and hormonal influences.
Main Results:
- The incidence of vertebral fractures in men over 50 is lower than in women, but traumatic fractures in younger men complicate prevalence data.
- Absolute fracture risk appears similar between sexes for the same age and BMD, suggesting current diagnostic thresholds for osteoporosis in women may apply to men.
- Current understanding of age-related bone loss mechanisms and the effects of sex hormones and growth factors on bone remodeling in men is incomplete.
Conclusions:
- Significant research is required to advance the understanding of bone fragility in men.
- Further studies are needed to clarify the proportion of traumatic vertebral fractures in men and identify individuals at high risk of fragility fractures.
- The anti-fracture efficacy and safety of various treatments, including androgens, remain incompletely investigated in the male population.
Introduction:
This is a summary of several aspects of the epidemiology, pathogenesis and treatment arising directly and indirectly from the proceedings of the Third International Osteoporosis in Men meeting held in Genoa in May 2005. Advances in the study of bone fragility in men have taken place, but many challenges remain.
Observations:
Although the epidemiology of hip fractures is well documented, the epidemiology of other non-vertebral fractures is less well defined even though these fractures contribute substantially to the global burden of fractures in men. The epidemiology of vertebral fragility fractures is derived mostly from cross sectional data. The comparable prevalence of vertebral fractures in men and women is likely to be misleading because of traumatic vertebral fractures that arise in young men. Prospective studies are needed to define the proportion of these fractures that are traumatic. After the age of 50 years, the incidence of vertebral fractures in men is about one third to one half of that in women. As in women, most vertebral and non-vertebral fragility fractures occur in persons without osteoporosis. Identifying these individuals is an unmet challenge. The absolute risk for fractures appears no different by sex in men and women of the same age and bone mineral density (BMD) so that the diagnostic threshold for osteoporosis in women can be used in men. Fracture risk varies around the world and is unlikely to be explained solely by variations in BMD, though there are few data comparing men and women of different races. Both the notion that men lose less bone than women from the endosteal envelope and that they gain more on the periosteal envelope during advancing age needs reassessment as recent evidence challenges these observations. Sex differences in the net gain and loss from these surfaces are likely to be site specific, and research is needed to specify this heterogeneity and the reasons for it. The independent and co-dependent effects of sex hormones and the growth hormone/insulin like growth factor 1 axis on periosteal and endosteal modeling and remodeling during growth as well as ageing are poorly defined. The anti-fracture efficacy and safety of androgens and other agents remain incompletely investigated in men.
Conclusion:
A great deal of research is needed to advance our understanding of bone fragility in men.


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:40
Bone Remodeling
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:24
Stress-Strain Diagram - Brittle Materials
 01:20
Disorders of the Male Reproductive System
Prostate disorders are another major concern. These conditions can impair urinary flow due to the prostate's location around the urethra. Symptoms...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...