Related Experiment Video
Updated: Aug 6, 2026


A Retrospective Study on Endoscopic Surgery for the Treatment of Paravertebral Abscess in Spinal Tuberculosis Patients
Published on: October 25, 2024
Dosing schedules of 6-month regimens and relapse for pulmonary tuberculosis
Kwok C Chang1, Chi C Leung, Wing W Yew
1Tuberculosis and Chest Service, Center for Health Protection, Department of Health; Tuberculosis and Chest Unit, Grantham Hospital, Hong Kong, China. kc_chang@dh.gov.hk

Rationale:
The optimal approach for reducing tuberculosis relapse is open.
Objectives:
We examined the possibility of reducing relapse by increasing dosing schedules.
Methods:
We conducted a systematic review of published clinical trials involving adult cohorts with pulmonary tuberculosis treated using 6-mo rifamycin-containing regimens, which were grouped under seven categories ordered by dosing schedules. Assuming cavitation and positive 2-mo culture were the driving forces for relapse, a static deterministic model apportioned observed numbers with and without relapse in each cohort into eight subgroups. Combining subgroups stratified by cavitation, 2-mo culture, and regimens enabled estimation of adjusted relapse risks. chi2 Tests for trend and logistic regression analysis examined the relationship between relapse and dosing schedules.
Results:
We identified 200 cases of bacteriologic relapse out of 5,208 patients in 32 cohorts. A logistic risk model showed a significant dose-response relationship between dosing schedules and relapse, with the following odds (95% confidence intervals) of relapse relative to daily regimens: 1.6 (0.6-4.1) for daily initial phase (IP) plus thrice-weekly continuation phase (CP), 2.8 (1.3-6.1) for daily IP plus twice-weekly CP, 2.8 (1.4-5.7) for thrice-weekly, 5.0 (2.4-10.5) for daily IP plus once-weekly rifapentine, and 7.1 (3.3-15.3) for thrice-weekly IP plus once-weekly rifapentine. In the presence of cavitation, only 6-mo daily or daily IP plus thrice-weekly CP attained best-estimated relapse risks below 5%; they reached 6% when 2-mo culture was also positive.
Conclusions:
Cavitary tuberculosis is best treated with 6-mo regimens comprising daily IP and thrice-weekly CP, which may be extended when 2-mo culture is positive.
Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:01
Dosage Regimen: Fixed Dose
Fixed-dose regimens can be used for various routes of administration, including intravenous (IV) injections and oral medications. For IV administration, a predetermined amount of the drug is...
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady state,...
 01:25
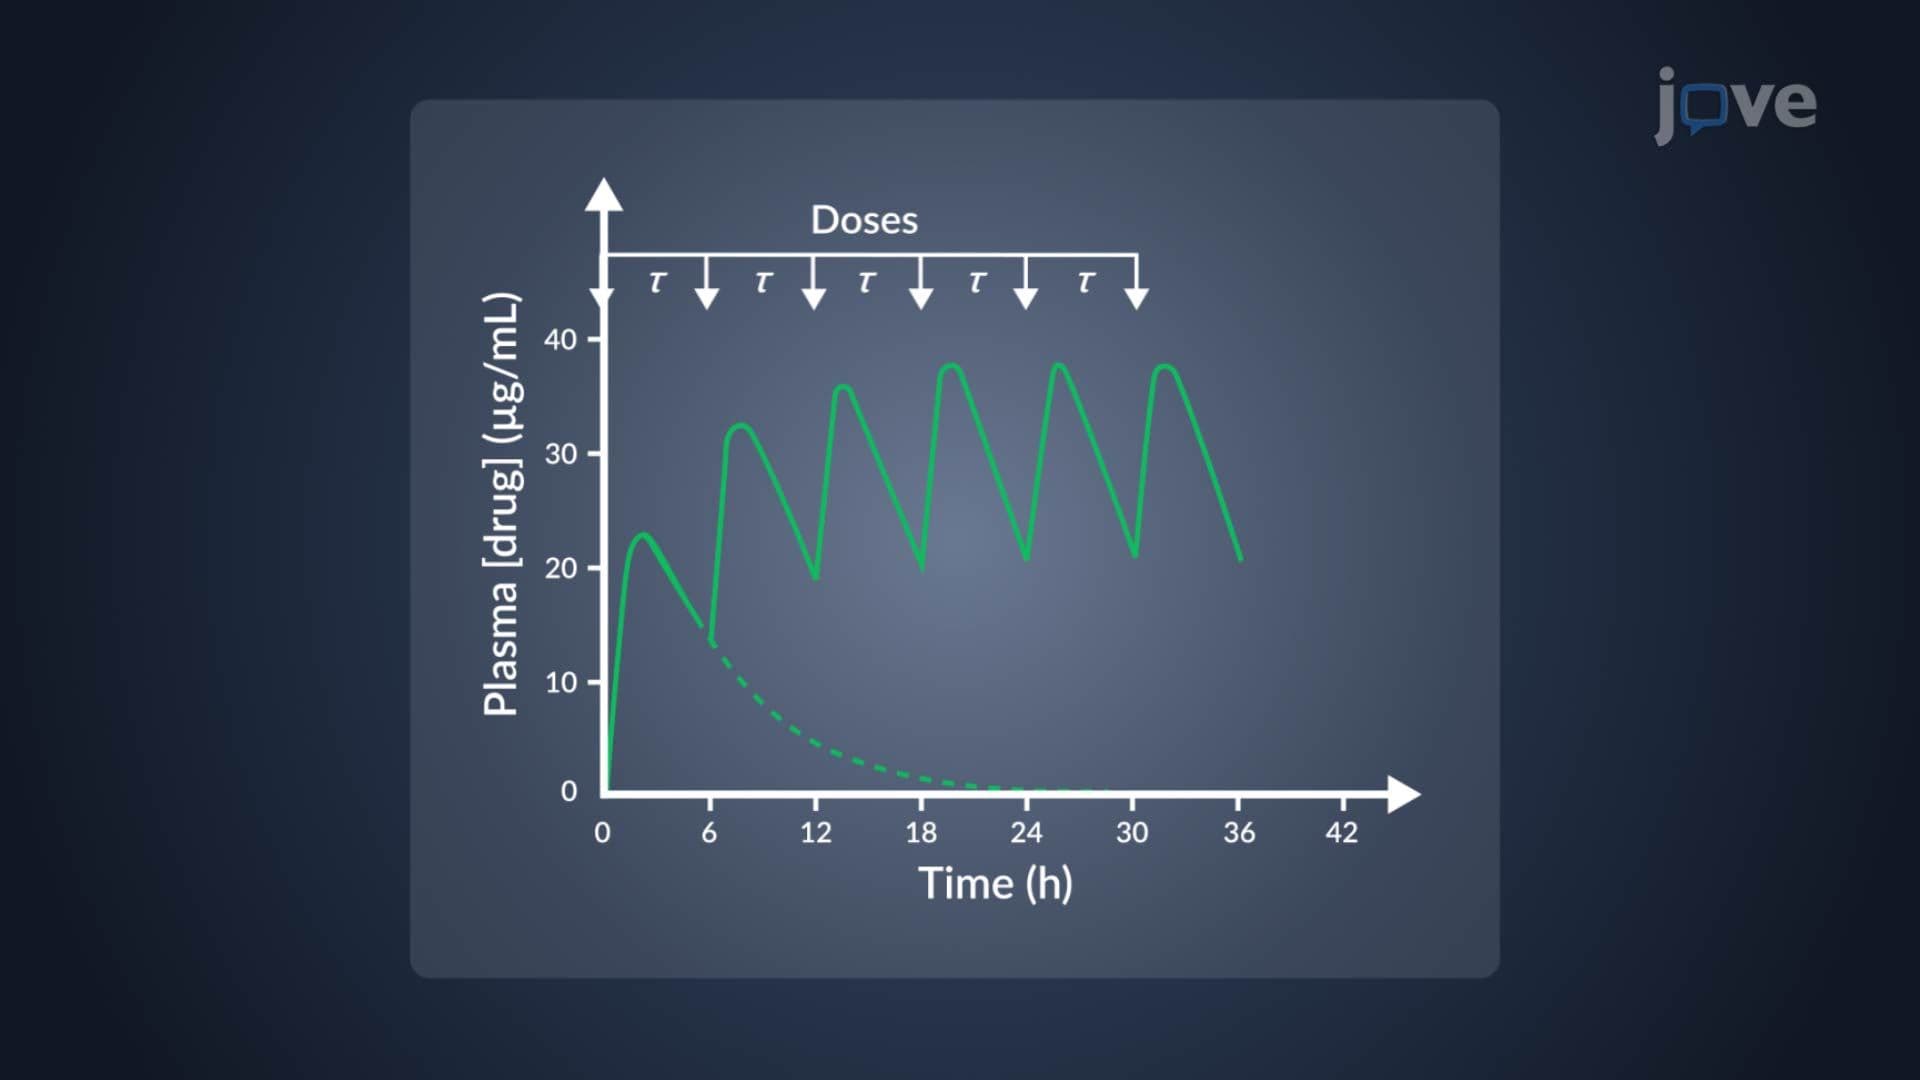
Dosage Regimen: Multiple Oral Dosage