Related Experiment Video
Updated: Jul 20, 2026

Cell-based Assay Protocol for the Prognostic Prediction of Idiopathic Scoliosis Using Cellular Dielectric Spectroscopy
Published on: October 16, 2013
Progression risk of idiopathic juvenile scoliosis during pubertal growth
Yann Philippe Charles1, Jean-Pierre Daures, Vincenzo de Rosa
1Service d'Orthopédie Pédiatrique, Centre Hospitalier Universitaire, Montpellier, France. ypcharles@hotmail.com

Study Design:
A retrospective study investigated the progression risk of juvenile scoliosis until skeletal maturity or spinal fusion.
Objectives:
To define risk factors of curve progression during pubertal growth and analyze the timing of arthrodesis.
Summary Of Background Data:
Juvenile scoliosis is characterized by a major, extremely variable progression risk. Peak growth velocity is the most critical period. Curve progression related to growth needs to be analyzed critically for an adequate treatment.
Methods:
A total of 205 patients, including 163 girls and 42 boys, with juvenile scoliosis were reviewed at skeletal maturity. The scoliosis was divided into juvenile I with an onset of 4-7 years (52 patients) and juvenile II with an onset of 8-10 years (153). Standing and sitting height, weight, Tanner signs, skeletal age, and menarche were regularly assessed. Topographies and Cobb angles of primary and secondary curves were referred to the pubertal growth diagram.
Results:
Of 205 patients, 99 (48.3%) were operated on. Of 109 curves < or = 20 degrees at onset of puberty, 15.6% progressed > 45 degrees and were fused. Of 56 curves of 21 degrees to 30 degrees, the surgical rate increased to 75.0%. It was 100% for curves > 30 degrees . Curves > 20 degrees, which increased and were operated on, progressed significantly during peak growth velocity (P = 0.0014). Curves that progressed by 6 degrees to 10 degrees/y were fused in 70.9%, curves which increased > 10 degrees/y in 100% of cases (P = 0.0001). This risk was highest for primary thoracic curves: King V, III, and II (P = 0.0001). There was no difference between males and females or juvenile I and II.
Conclusions:
Curve pattern, Cobb angle at onset of puberty, and curve progression velocity are strong predictive factors of curve progression. Juvenile scoliosis > 30 degrees increases rapidly and presents a 100% prognosis for surgery (curve > 40 degrees to 45 degrees ). Anticipation is necessary if the scoliosis progresses during the first year of puberty. The prediction is difficult for curves of 21 degrees to 30 degrees during the first 2 years of puberty. Curve pattern and curve progression velocity are useful to detect which curves are likely to progress. From this retrospective analysis, spinal fusion could have been indicated earlier sometimes. An earlier intervention is probably preferable to obtain better curve reduction on a supple spine, even if a perivertebral fusion is necessary. We use the 3 parameters for operative indications. If an early spinal fusion leads to better curve correction needs to be verified on prospective data.
More Related Videos

Related Concept Videos
 01:27
Signs of Puberty
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:27
Growth of Cartilage and Bone Tissue
 02:07
Tumor Progression
Colon cancer is one of the best-documented examples of tumor progression. Early mutation in the APC gene in colon cells causes a small growth on the colon wall called a polyp. With time, this polyp grows into a benign, pre-cancerous tumor. Further...
02:07Tumor Progression
Colon cancer is one of the best-documented examples of tumor progression. Early mutation in the APC gene in colon cells causes a small growth on the colon wall called a polyp. With time, this polyp grows into a benign, pre-cancerous tumor. Further...
 01:16
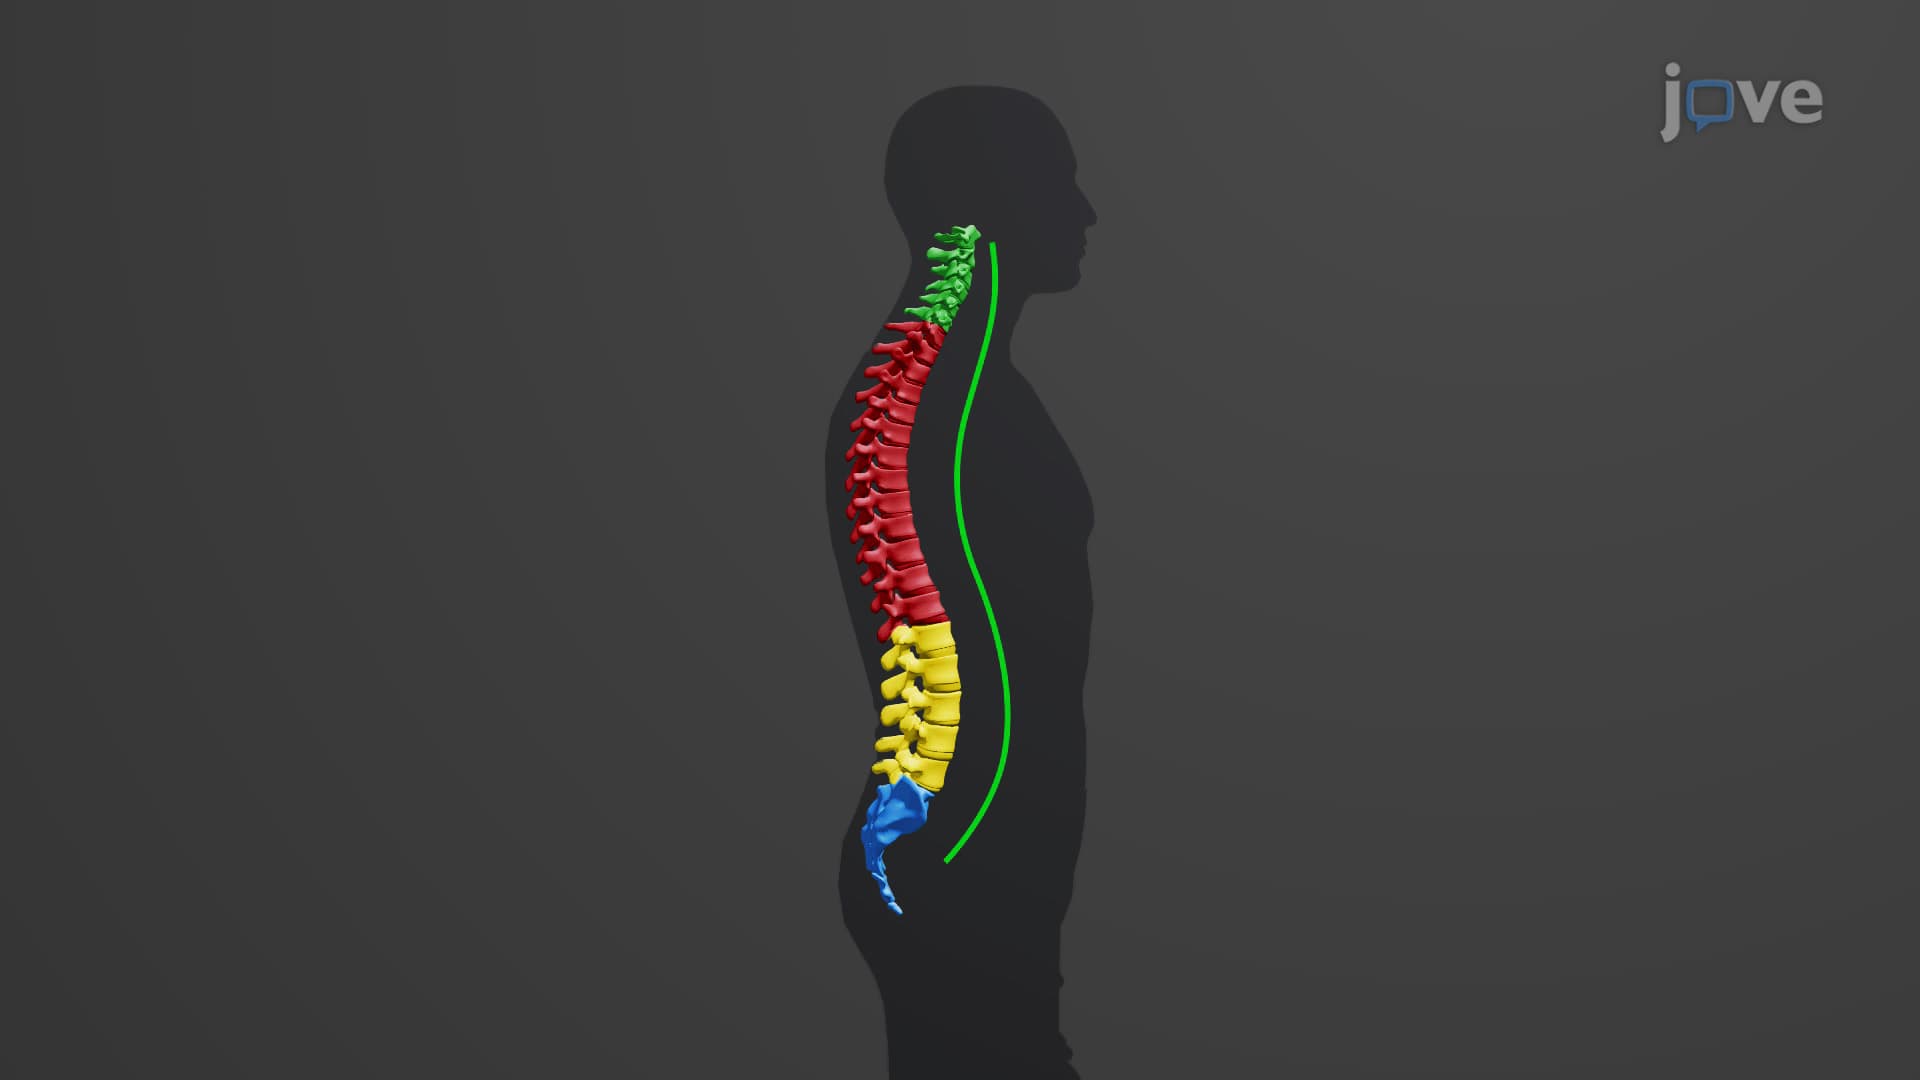
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...