Related Experiment Video
Updated: Jul 20, 2026


Tension-Free Weight-Bearing Model of Steroid-Induced Osteonecrosis of Femoral Head in Rats
Published on: September 27, 2024
Pathophysiology and natural history of avascular necrosis of bone
1Service de Rhumatologie, CHU la Conception, 147, boulevard Baille, 13385 Marseille cedex 5, France. plafforgue@ap-hm.fr

Abstract:
Avascular necrosis of bone (AVN) occurs as two main variants, local and systemic. Local AVN is usually caused by trauma or microtrauma; examples include primary osteonecrosis of the medial condyle, vertebral osteonecrosis, necrosis after meniscectomy, and osteonecrosis of the mandible or small bones. Systemic AVN manifests as epiphyseal necrosis or bone infarction, which is often multifocal. Little is known about the factors that trigger AVN. One possible mechanism is intraluminal obliteration of blood vessels by microscopic fat emboli, sickle cells, nitrogen bubbles (caisson disease), or focal clotting due to procoagulant abnormalities. Extraluminal obliteration may result from elevated marrow pressure or increased marrow fat. Cytotoxicity and genetic factors may be involved also. Many factors are probably capable of inducing AVN, and combinations of factors may be required, although the final mechanism is always critical ischemia. The natural history of AVN is better understood than the early triggering factors. AVN becomes detectable 1-6 months after exposure to an easily identifiable risk factor such as high-dose glucocorticoid therapy or femoral neck fracture. Later on, AVN is uncommon even when the patient remains exposed to the risk factor. The turning point in the natural history of AVN is subchondral plate fracture, which leads to collapse of the necrotic segment of the epiphysis, usually within the first 2 years. The risk of collapse depends chiefly on the initial size and location of the necrotic segment, which can be determined accurately by magnetic resonance imaging (MRI). This natural history has obvious clinical implications.
Related Concept Videos
 01:23
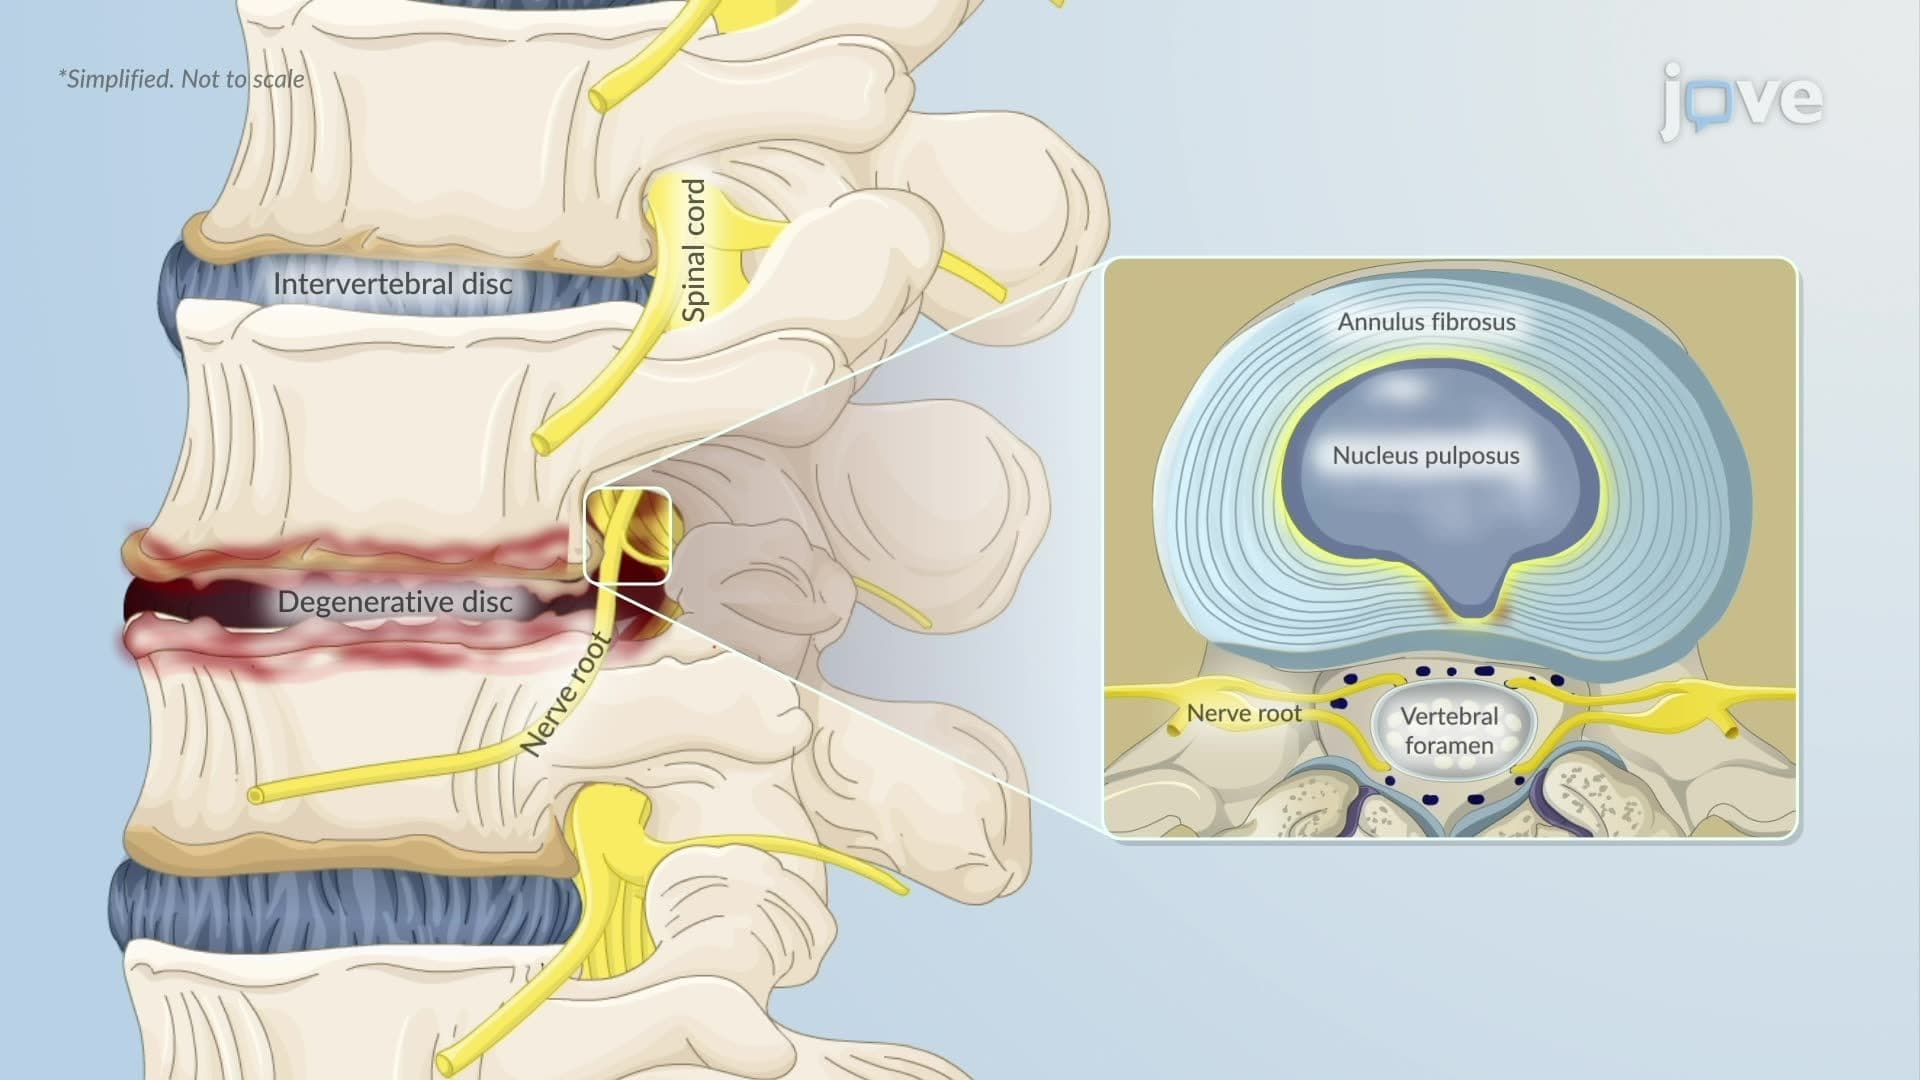
Degenerative Disc Disease ll: Pathophysiology
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
Degenerative Disc Disease I: Introduction
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:29
Blood and Nerve Supply to the Bones
Nutrient Artery
The nutrient artery is the main blood vessel that enters the diaphysis via the nutrient foramen. While most long bones have only one nutrient foramen, large bones, such as the femur, may have two. This...
 01:31
Osteoclasts in Bone Remodeling