Related Experiment Video
Updated: Jul 20, 2026

Surgical Placement of Catheters for Long-term Cardiovascular Exercise Testing in Swine
Published on: February 9, 2016
Influence of cardiac output level on oxygen exchange in chronic obstructive pulmonary disease patients
Gérard Manier1, Odile Pillet, Yves Castaing
1Service des Explorations Fonctionnelles Respiratoires, Hopital Pellegrin, Bordeaux Cedex, France. @chu-bordeaux.fr

Study Objectives:
In the course of chronic obstructive pulmonary disease (COPD), pulmonary gas exchange deteriorates as a result of ventilation/perfusion inequalities and hypoxaemia. The aim of the present study was to evaluate the influence of cardiac output (CO) level observed at rest in COPD patients on interaction between central and peripheral O(2) exchange.
Methods:
One hundred and nine patients with advanced but stable COPD were analysed in a retrospective study by the multiple inert gas elimination technique. As a function of CO, simulations were conducted to evaluate the respective part of PvO(2) and VA/Q inequalities on the degree of hypoxaemia.
Measurements And Results:
PaO(2) was linked (i) to cardiac index (CI), (ii) to mean VA/Q ratio of blood flow distribution and (iii) to PvO(2), but PvO(2) was not correlated with CO. By comparing two groups with CI above and below the mean value of the series respectively, a significant difference was identified in PaO(2) (57 +/- 9 mmHg in the high CI group versus 63 +/- 10 mmHg in the low CI group, P<0.05) because of higher VA/Q inequalities in the high CI group. Comparing two other groups with values of PvO(2) above and below the mean value of the series respectively, a significant difference was identified in PaO(2): (mean +/- SD was 65 +/- 8 in high PvO(2) group versus 56 +/- 9 mmHg, P<0.001) but with no difference in either CI or perfusion distribution. Analysis of the cumulated effects of PvO(2) and CI values, indicated that high CI and low PvO(2) gave rise to the lowest PaO(2) (53 +/- 8 mmHg), with the highest PaO(2) (68 +/- 8 mmHg) being found in the low CI and normal PvO(2) group.
Conclusions:
We concluded that in COPD patients, PaO(2) appeared to be maintained better when peripheral gas exchange coped with tissue demand without an increase in CO. Conversely, when the physiological increase in CO could not maintain adequate tissue gas exchange, PaO(2) continued to fall due to the cumulative effects of increasing CO on VA/Q inequalities and low PvO(2).
More Related Videos

Related Concept Videos
 01:19
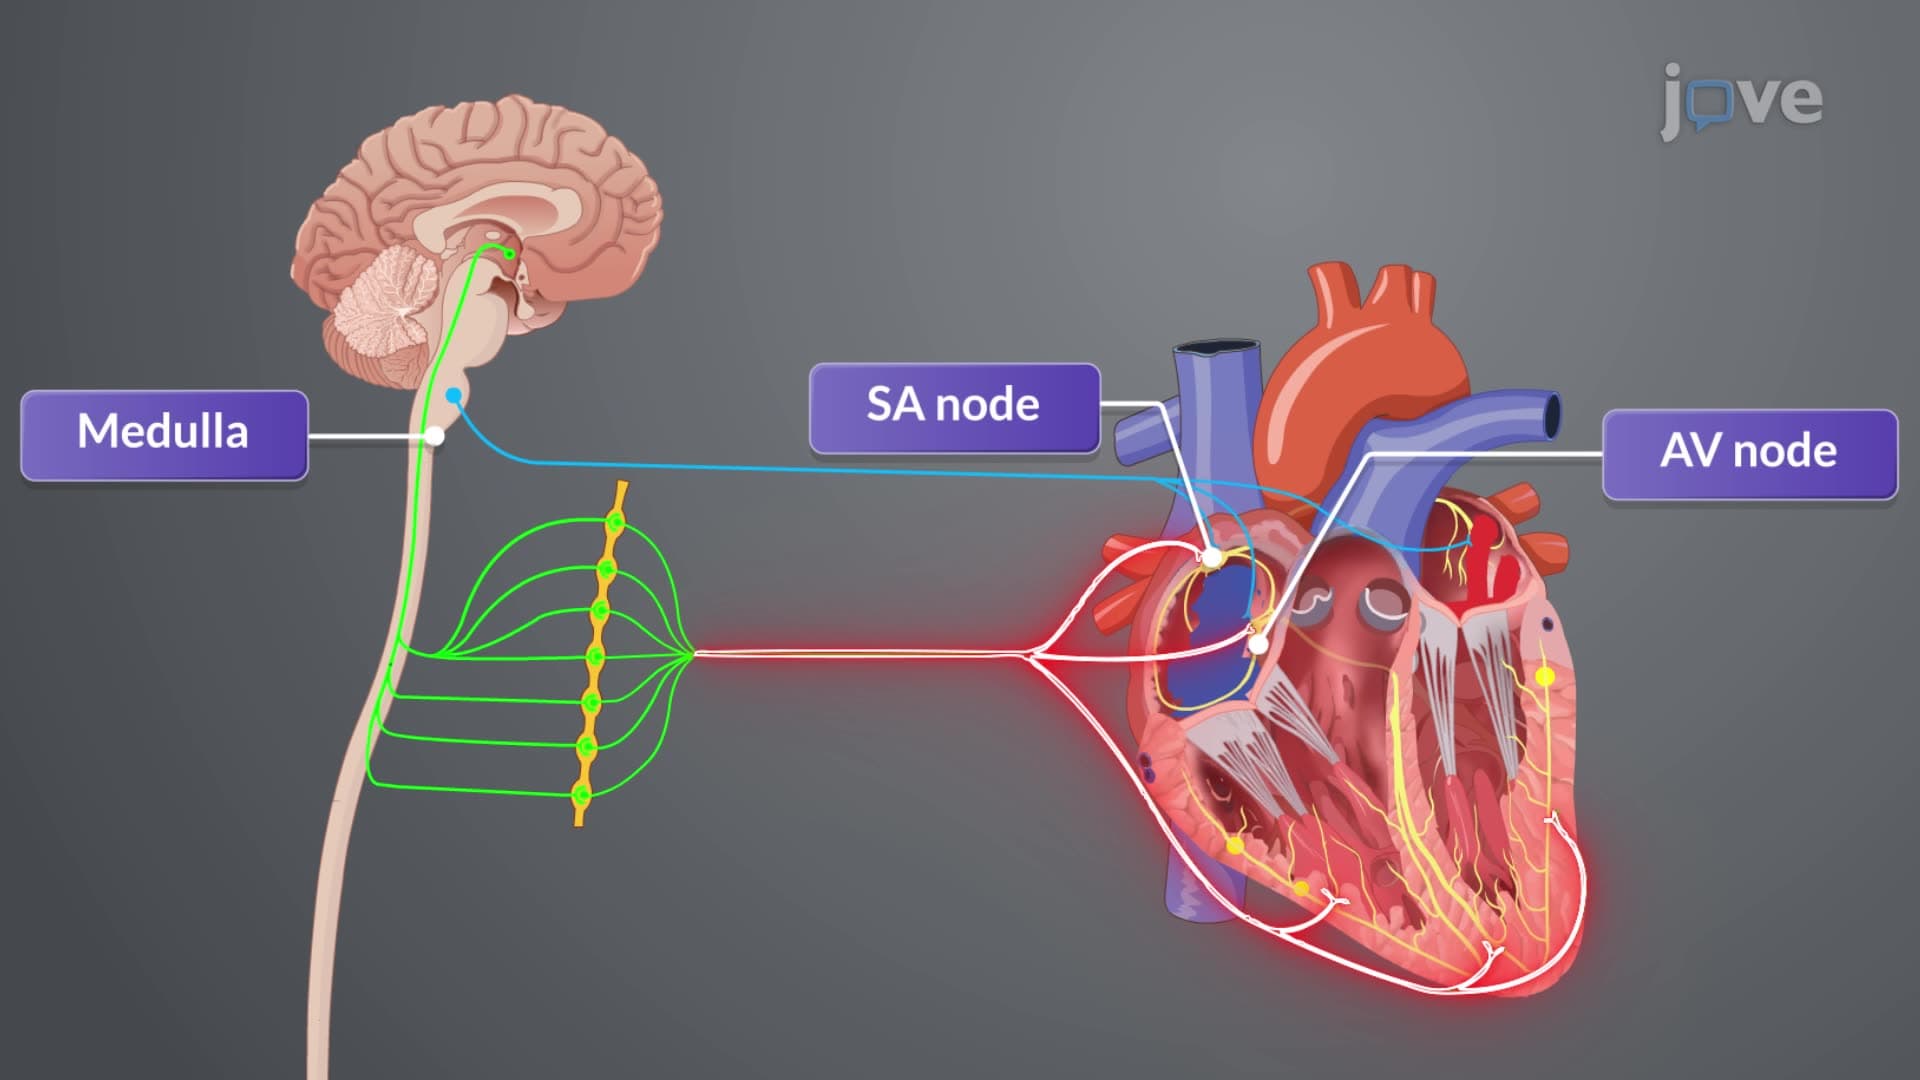
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be met...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac output averages...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...