Related Experiment Video
Updated: Jul 20, 2026
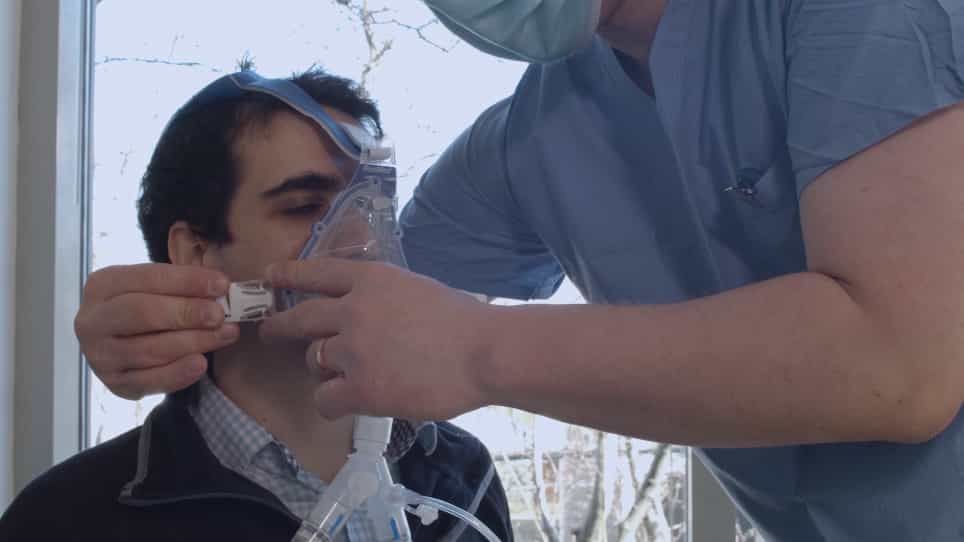

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Exhaled nitric oxide differentiates airway diseases in the first two years of life
Carmelo Gabriele1, Eveline M Nieuwhof, Els C Van Der Wiel
1Department of Pediatric Respiratory Medicine, Erasmus Medical Centre/Sophia Children's Hospital, Rotterdam, 3000 CB, the Netherlands.

Insights
Fractional exhaled nitric oxide (FE(NO)) can help distinguish airway diseases in infants. This study found distinct FE(NO) levels in infants with recurrent wheezing, bronchopulmonary dysplasia, and cystic fibrosis, aiding early diagnosis.
Area of Science:
- Pediatric Pulmonology
- Respiratory Medicine
- Biomarker Research
Background:
- Fractional exhaled nitric oxide (FE(NO)) is elevated in asthma but reduced in cystic fibrosis (CF) and primary ciliary dyskinesia.
- Distinguishing between infant airway diseases can be challenging due to overlapping symptoms.
- FE(NO) as a non-invasive biomarker for early detection of pediatric respiratory conditions requires further investigation.
Purpose of the Study:
- To evaluate the utility of FE(NO) measurements in differentiating airway diseases in infants under two years old.
- To compare FE(NO) levels across different infant respiratory conditions including recurrent wheezing (RW), bronchopulmonary dysplasia (BPD), and CF.
- To assess FE(NO) levels in healthy infants as a control group for comparison.
Main Methods:
- FE(NO) was measured in 118 infants (4.6-25.2 months) with RW (n=74), BPD (n=24), and CF (n=20).
- FE(NO) was also measured in 100 healthy control infants (1.1-7.7 months).
- Statistical analysis was performed to compare FE(NO) values between groups.
Main Results:
- FE(NO) levels were significantly higher in infants with RW (18.6 ppb) compared to healthy controls (10.4 ppb), BPD (11.7 ppb), and CF (5.9 ppb).
- Infants with CF showed significantly lower FE(NO) than healthy controls and BPD infants.
- FE(NO) levels in BPD infants were not significantly different from healthy controls. Atopic wheezers had higher FE(NO) than nonatopic wheezers.
Conclusions:
- FE(NO) measurements are valuable in differentiating between various airway diseases in infants younger than two years.
- Distinct FE(NO) profiles observed can aid in the early diagnosis and management of pediatric respiratory conditions.
- FE(NO) serves as a useful, non-invasive tool for distinguishing RW, BPD, and CF in early childhood.
Abstract:
Fractional exhaled nitric oxide (FE(NO)) levels are increased in children and adults with asthma, whereas low levels have been found in cystic fibrosis and primary ciliary dyskinesia. The aim of this study was to investigate whether FE(NO) measurements could distinguish between children below the age of 2 with different airway diseases. FE(NO) measurements were performed in 118 infants aged between 4.6 and 25.2 mo: 74 infants with recurrent wheezing (RW), 24 with bronchopulmonary dysplasia (BPD), and 20 with cystic fibrosis (CF). FE(NO) was measured also in 100 healthy controls aged between 1.1 and 7.7 mo. Geometric mean (95% confidence interval) FE(NO) values were 10.4 (9.1-12.0) parts per billion (ppb) in healthy infants, 18.6 (15.6-22.2) ppb in wheezy infants, 11.7 (8.2-16.8) ppb in BPD infants and 5.9 (3.4-10.1) ppb in CF infants. FE(NO) in wheezers was higher than in controls, BPD, and CF (p = 0.009, p = 0.038, and p < 0.001, respectively). Atopic wheezers showed higher FE(NO) than nonatopic wheezers (p = 0.04). CF infants had lower FE(NO) than healthy controls and BPD infants (p = 0.003 and p = 0.043, respectively). FE(NO) values in BPD and control infants were not different. We conclude that FE(NO) is helpful to differentiate various airway diseases already in the first 2 y of life.
Related Concept Videos
 01:05
Breathing
 01:28
Asthma I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:17
Pulmonary Cycle: Exhalation
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction