Acute management and secondary prophylaxis of esophageal variceal bleeding: a western Canadian survey
Related Experiment Video
Updated: Jul 20, 2026
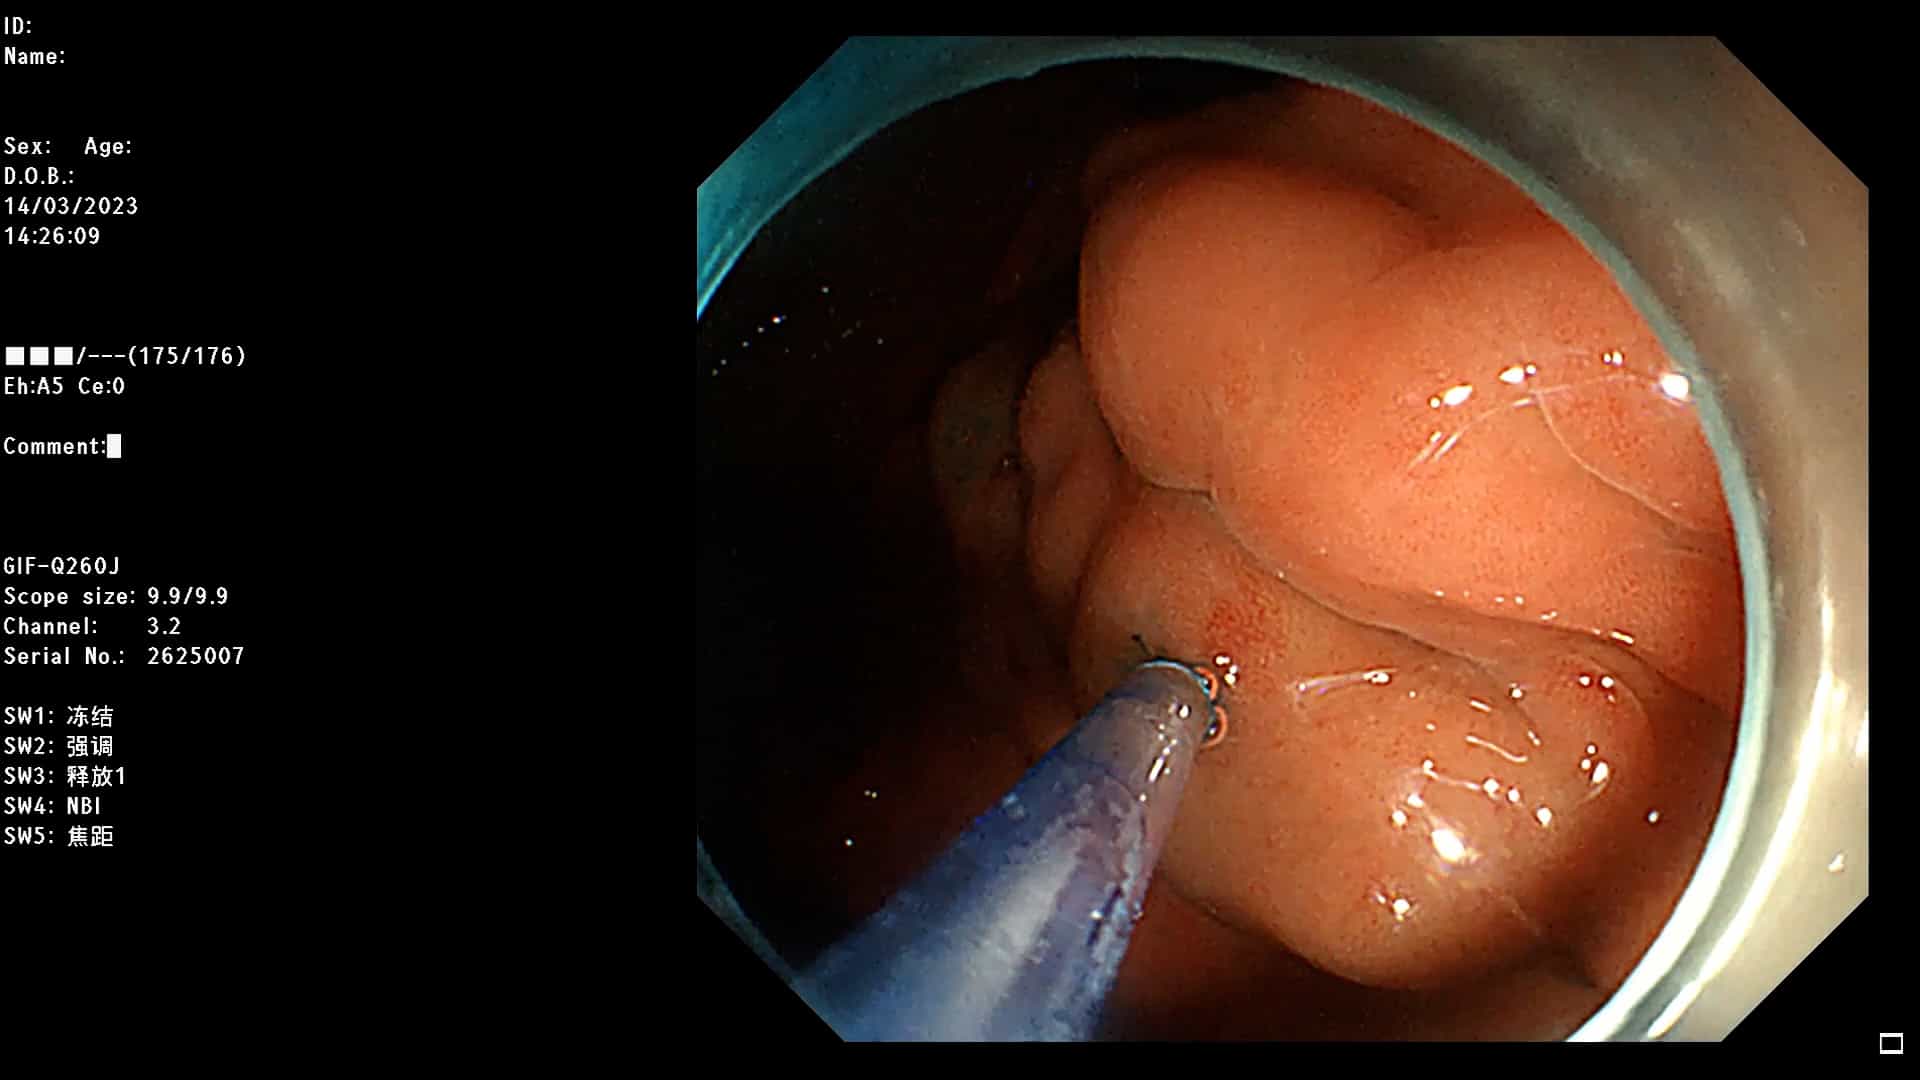
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Justin Cheung1, Winnie Wong, Iman Zandieh
1Department of Medicine, University of Alberta, Edmonton.

Background:
Acute esophageal variceal bleeding (EVB) is a major cause of morbidity and mortality in patients with liver cirrhosis. Guidelines have been published in 1997; however, variability in the acute management and prevention of EVB rebleeding may occur.
Methods:
Gastroenterologists in the provinces of British Columbia, Alberta, Manitoba and Saskatchewan were sent a self-reporting questionnaire.
Results:
The response rate was 70.4% (86 of 122). Intravenous octreotide was recommended by 93% for EVB patients but the duration was variable. The preferred timing for endoscopy in suspected acute EVB was within 12 h in 75.6% of respondents and within 24 h in 24.6% of respondents. Most (52.3%) gastroenterologists do not routinely use antibiotic prophylaxis in acute EVB patients. The preferred duration of antibiotic therapy was less than three days (35.7%), three to seven days (44.6%), seven to 10 days (10.7%) and throughout hospitalization (8.9%). Methods of secondary prophylaxis included repeat endoscopic therapy (93%) and beta-blocker therapy (84.9%). Most gastroenterologists (80.2%) routinely attempted to titrate beta-blockers to a heart rate of 55 beats/min or a 25% reduction from baseline. The most common form of secondary prophylaxis was a combination of endoscopic and pharmacological therapy (70.9%).
Conclusions:
Variability exists in some areas of EVB treatment, especially in areas for which evidence was lacking at the time of the last guideline publication. Gastroenterologists varied in the use of prophylactic antibiotics for acute EVB. More gastroenterologists used combination secondary prophylaxis in the form of band ligation eradication and beta-blocker therapy rather than either treatment alone. Future guidelines may be needed to address these practice differences.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...