Related Experiment Video
Updated: Jul 20, 2026

Intracoronary Acetylcholine Provocation Testing for Assessment of Coronary Vasomotor Disorders
Published on: August 18, 2016
Veralipride-induced acute coronary syndrome unmasking a non-secreting pheochromocytoma
1DMCS-Internal Medicine 4, University of Padua, Padua, Italy.

Abstract:
The administration of veralipride, a centrally acting dopaminergic type 2 (DA2) receptor antagonist, can decrease hot flushes and improve bone density in post-menopausal women (1). Therefore, it entails an alternative to hormone replacement therapy (HRT) in women who have contraindications to estrogen (1). We herein describe the case of a 52-yr-old lady who presented with an acute coronary syndrome shortly after taking veralipride. Based on knowledge that DA2 receptor antagonists trigger catecholamine release (2), a pheochromocytoma was suspected and thereafter diagnosed and excised. Therefore, this is the first case reporting on veralipride unmasking a silent pheochromocytoma.
Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:22
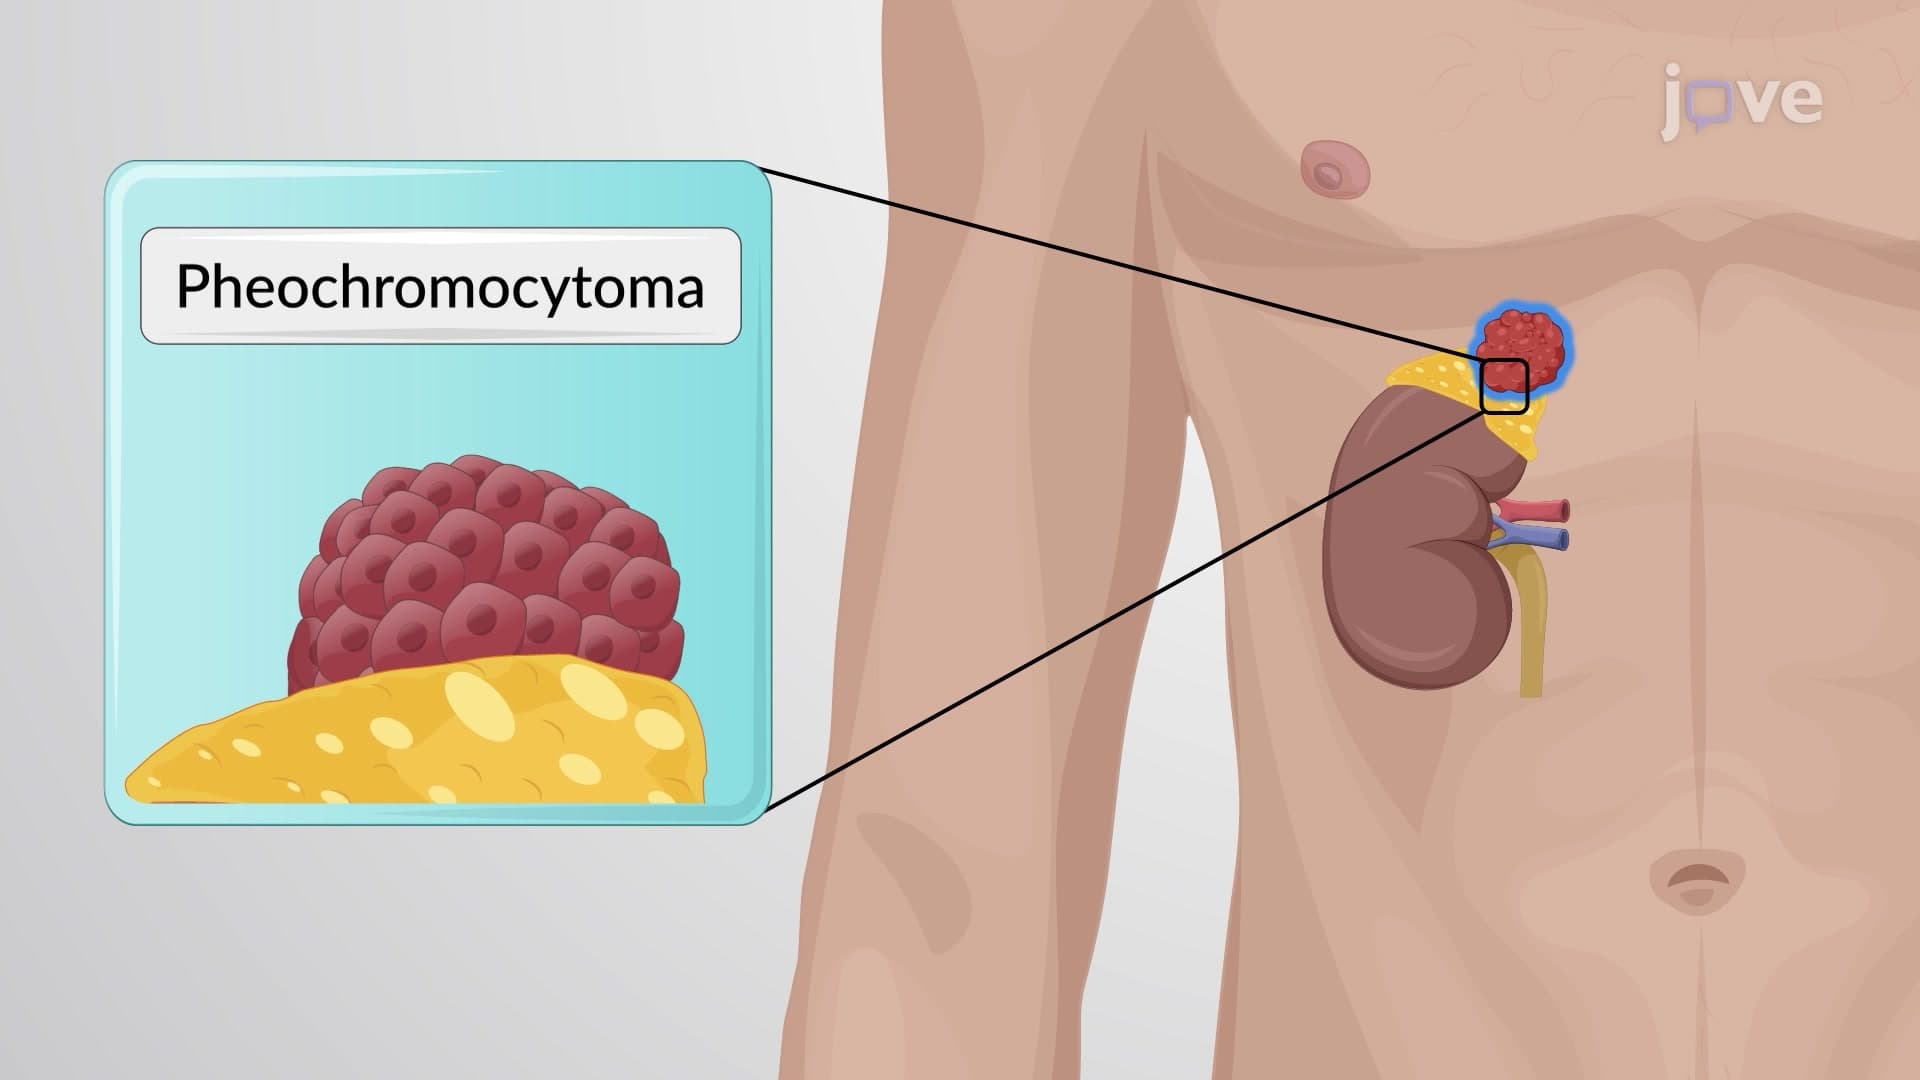
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:25
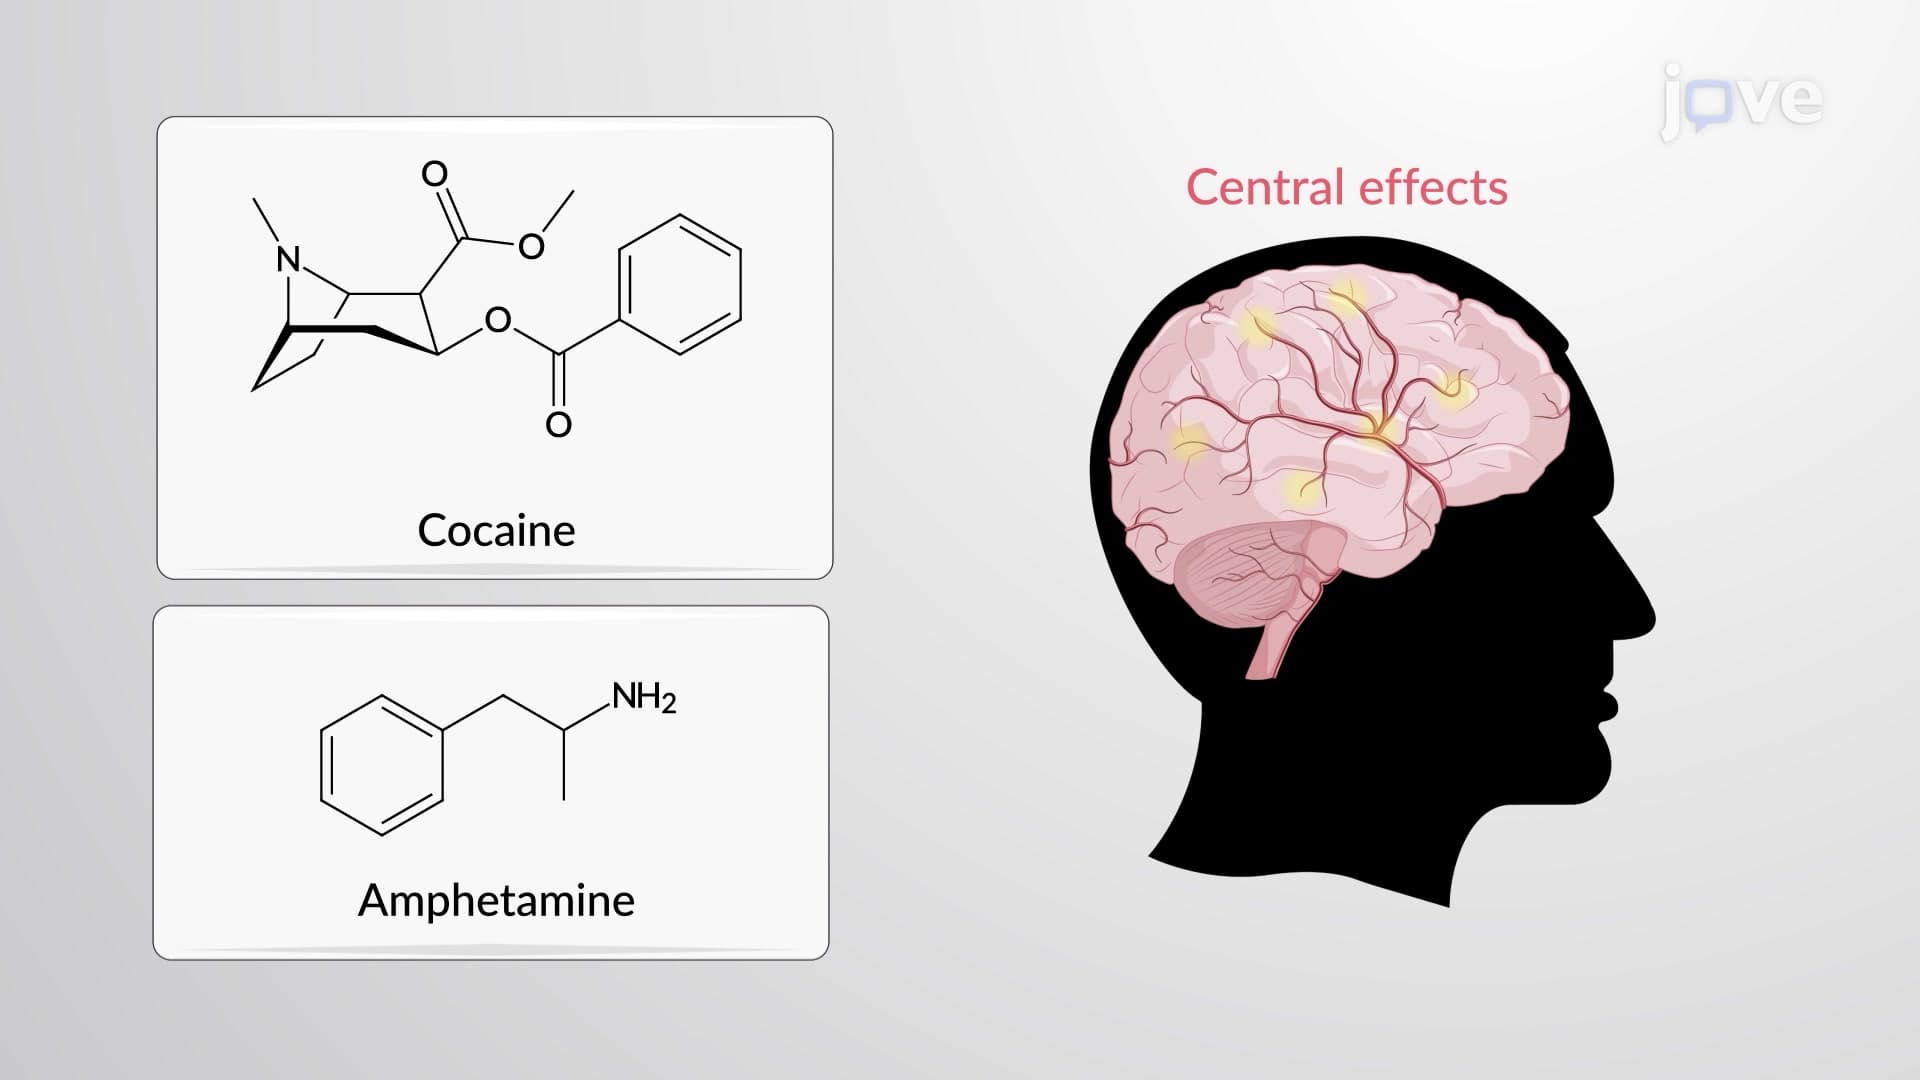
Adrenergic Agonists: Indirect-Acting Agents
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral bioavailability, and...
 01:21
Drugs Affecting Neurotransmitter Release or Uptake